- Ihr Warenkorb ist leer
- Weiter Einkaufen


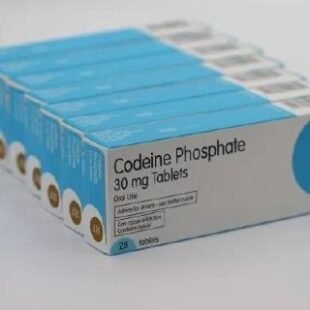


Preisklasse: £ 51.80 durch £ 518.00
Toseina 2 mg/ml Solución Oral is a licensed European branded liquid pharmaceutical preparation manufactured primarily in Spain (by Laboratorios Italfarmaco S.A.). The active pharmaceutical ingredient (API) is codeine phosphate hemihydrate (chemically designated as $(5R,6S,9R,13S,14R)\text{-3-methoxy-17-methyl-4,5-epoxymorphin-6-ol phosphate hemihydrate}$). Codeine is a naturally occurring phenanthrene alkaloid obtained from the opium poppy (Schlafender Mohn) or synthesized via the $O\text{-methylation}$ of morphine. Its empirical molecular formula as the phosphate salt is $\text{C}_{18}\text{H}_{21}\text{NO}_3\cdot\text{H}_3\text{PO}_4\cdot\frac{1}{2}\text{H}_2\text{O}$, with a molecular mass of approximately $406.4\text{ g/mol}$.
Standard commercial presentations of Toseina consist of a clear, bright red/pink, viscous oral solution containing $2\text{ mg}$ of codeine phosphate per millilitre (supplied in amber glass or polyethylene bottles, most commonly $250\text{ mL}$, containing a total of $500\text{ mg}$ of codeine phosphate). The formulation contains notable excipients, including high concentrations of liquid sorbitol (which exerts an osmotic laxative effect in supratherapeutic quantities), sodium saccharin, methyl and propyl parahydroxybenzoates (parabens), raspberry flavoring agents, and artificial coloring (such as Ponceau 4R / E124 or carmoisine).
Within the United Kingdom and European regulatory frameworks:
UK Classification: In the UK, liquid codeine preparations containing higher concentrations or intended for non-over-the-counter use are governed under the Human Medicines Regulations 2012 as Prescription Only Medicines (POM). Under the Misuse of Drugs Act 1971 and Misuse of Drugs Regulations 2001, codeine is scheduled as a Class B controlled drug (Schedule 5 when formulated as low-strength multi-ingredient oral preparations below specific concentration thresholds, but Class B / Schedule 2 in pure or concentrated forms).
European Status (AEMPS – Spain): Licensed by the Spanish Agency of Medicines and Medical Devices (AEMPS) as a prescription-only medicinal product (medicamento sujeto a prescripción médica).
In recent years, Toseina has gained extensive notoriety across European and UK illicit drug markets as a premium imported pharmaceutical syrup utilized in recreational polydrug consumption, specifically as the opioid base for concoctions colloquially termed “lean,” “purple drank,” or “dirty sprite” (where the syrup is mixed with carbonated sodas, hard candy, and frequently co-ingested with sedating first-generation antihistamines such as promethazine). Illicitly diverted or counterfeit bottles circulating online carry critical clinical hazards of adulteration with synthetic opioids (such as fentanyl analogues or ultra-potent nitazenes), variable dosing, and counterfeit industrial dyes.
Codeine acts as a centrally acting, weak-to-moderate opioid analgesic and antitussive whose primary clinical efficacy depends fundamentally on its metabolic bioactivation into morphine:
Bioactivation to Morphine (The Prodrug Mechanism): Intact codeine ($3\text{-O-methylmorphine}$) possesses very low intrinsic affinity for opioid receptors—exhibiting approximately 200-fold lower affinity for human $\mu\text{-opioid}$ (MOP) receptors than morphine. Its therapeutic antitussive and analgesic efficacy is largely mediated by hepatic biotransformation via the cytochrome P450 2D6 (CYP2D6) enzyme, which cleaves the 3-methoxy group to liberate free Morphium.
$\mu$-Opioid Receptor Activation: Metabolically generated morphine acts as a full agonist at the $\mu\text{-opioid}$ receptor, a Class A G-protein-coupled receptor coupled to inhibitory $G_{\alpha i/o}$ proteins. Receptor activation suppresses adenylyl cyclase activity (decreasing intracellular cAMP), closes presynaptic voltage-gated N-type calcium channels, and opens postsynaptic G-protein-coupled inwardly rectifying potassium (GIRK) channels. This hyperpolarizes ascending nociceptive pathways in the spinal cord dorsal horn and periaqueductal gray, blunting pain transmission.
Medullary Antitussive Reflex Suppression: Codeine suppresses the cough reflex through direct depressant action on the cough center located within the nucleus tractus solitarii of the medulla oblongata. This antitussive action is partly mediated by direct codeine binding to distinct opioid-like cough receptors and $\sigma\text{-receptors}$, independent of its systemic conversion to morphine.
Central and Autonomic Depressant Cascades: Agonism of $\mu\text{-opioid}$ receptors located in the pontine and medullary respiratory control centers (pre-Bötzinger complex) dulls the chemoreceptor response to arterial hypercapnia ($\text{CO}_2$ retention) and hypoxia, driving concentration-dependent respiratory depression. Peripheral $\mu\text{-receptor}$ activation on the myenteric plexus inhibits bowel peristalsis and secretomotor reflexes, driving profound gastrointestinal stasis (constipation).
Toseina holds specific, licensed indications within European prescribing literature:
Symptomatic Relief of Dry, Non-Productive Cough: Indicated in adults and adolescents aged 12 years and over for the short-term symptomatic treatment of irritating, dry, non-productive cough refractory to non-opioid antitussives.
Standard clinical adult dose: $10\text{ to }20\text{ mg}$ ($5\text{ to }10\text{ mL}$) administered every 6 to 8 hours as clinically indicated (maximum licensed daily ceiling: $120\text{ mg}$ oder $60\text{ mL}$ within 24 hours).
Strict Contraindication in Paediatrics (<12 Years): The European Medicines Agency (EMA) and UK MHRA issued definitive safety mandates restricting codeine for cough and cold exclusively to patients aged 12 years and older, strictly contraindicating its use in children under 12, as well as adolescents (12 to 18 years) with compromised respiratory function or those undergoing tonsillectomy/adenoidectomy for obstructive sleep apnoea.
The National Institute for Health and Care Excellence (NICE) Clinical Knowledge Summaries (CKS: Cough) explicitly does not recommend opioid antitussives (including codeine and dextromethorphan) for routine acute cough management, emphasizing that evidence for clinical efficacy is limited, whereas risks of tolerance, dependency, and sedation are significant.
In non-clinical, illicit settings, Toseina is heavily abused:
Recreational “Lean” / “Sizzurp” Formulations: Users consume supratherapeutic volumes ($100\text{ to }250\text{ mL}$, equivalent to $200\text{ to }500\text{ mg}$ of codeine) mixed into sugary beverages. It is routinely combined with OTC or prescription promethazine tablets/syrups to augment central sedation, suppress opioid-induced emesis, and reduce codeine-induced peripheral histamine release.
Self-Directed Opioid Maintenance / Euphoric Misuse: Exploited by individuals with opioid use disorder (OUD) to stave off acute withdrawal or achieve a calm, euphoric state of mental detachment.
Toseina holds no listing on the NHS Drug Tariff (as an imported Spanish branded product), cannot be prescribed on standard NHS FP10 forms, and must be monitored as an illicitly imported diverted pharmaceutical when encountered in UK clinical contexts.
Because Toseina is formulated as a pre-dissolved liquid solution, its pharmacokinetic disposition is defined by rapid gastrointestinal absorption, high first-pass hepatic biotransformation, and critical CYP2D6 genetic polymorphism dependencies:
Absorption: Following oral administration, liquid codeine phosphate is absorbed rapidly across the gastrointestinal mucosa. Peak plasma concentrations ($C_{max}$) are achieved rapidly, with a median $T_{max}$ of 30 to 60 minutes. Oral bioavailability is moderate, averaging $40\text{ to }70\%$, attenuated by first-pass hepatic extraction.
Distribution: Codeine distributes rapidly into systemic tissues, crossing the blood-brain barrier via both passive lipophilic diffusion and carrier-mediated transport. It exhibits an apparent volume of distribution ($V_d$) of approximately $3.5\text{ L/kg}$. In circulating human plasma, codeine displays low plasma protein binding (approximately $7\text{ to }25\%$), binding non-specifically to human serum albumin. It crosses the placental boundary and concentrates in maternal breast milk.
Biotransformation (The CYP2D6 / Glucuronidation Cascade): Codeine undergoes complex, multi-pathway hepatic biotransformation:
Glucuronidation (UGT2B7, $\sim 70\text{ to }80\%$): The predominant metabolic pathway is conversion to codeine-6-glucuronide (C6G), an active polar metabolite that contributes to analgesia and sedation.
N-Demethylation (CYP3A4, $\sim 10\text{ to }15\%$): Inactive pathway converting codeine into norcodeine.
$O\text{-Demethylation}$ (CYP2D6, $\sim 5\text{ to }10\%$): The bioactivation pathway. Cytochrome P450 2D6 converts codeine directly into active Morphium. Converted morphine is subsequently conjugated into morphine-3-glucuronide (M3G, neurotoxic) and morphine-6-glucuronide (M6G, highly active opioid agonist).
The CYP2D6 Genetic Polymorphism Trap:
Poor Metabolisers (PMs; $\sim 7\text{ to }10\%$ of Caucasians): Lack functional CYP2D6 alleles; unable to metabolize codeine into morphine. These individuals experience virtually zero analgesic or euphoric response, though they remain vulnerable to codeine-induced adverse reactions (e.g., nausea, constipation, histamine release).
Ultra-Rapid Metabolisers (UMs; up to $10\%$ of Caucasians, up to $29\%$ of specific North African/Middle Eastern cohorts): Possess CYP2D6 gene duplications, conferring accelerated conversion. In UMs, standard or mildly elevated doses of Toseina generate sudden, massive circulating levels of free morphine, precipitating unexpected, life-threatening fatal respiratory depression and coma.
Elimination: Clearance occurs predominantly via renal excretion. Approximately $90\%$ of an administered dose is excreted in the urine within 48 hours, largely as glucuronide conjugates (C6G, M3G, M6G), with less than $10\%$ eliminated as unchanged codeine. The terminal plasma elimination half-life ($t_{1/2}$) of codeine in adults is short, averaging 2.5 to 3.5 hours (morphine $t_{1/2} \approx 2\text{ to }3\text{ hours}$).
The primary physiological action in therapeutic use is suppression of the medullary cough reflex and mild elevation of pain thresholds. However, supratherapeutic dosing or combination with sedating antihistamines generates severe multi-system adverse effects:
Common and Gastrointestinal Effects (Very Common to Common, $\ge 1/100$ to $\ge 1/10$):
Nausea, vomiting, and epigastric distress (provoked by stimulation of the chemoreceptor trigger zone [CTZ] in the area postrema).
Severe constipation: delayed gastric emptying and blunted colonic motility.
Drowsiness, sedation, dizziness, and cognitive blunting.
Biliary colic / Sphincter of Oddi spasm: marked constriction of biliary smooth muscle causing acute, severe epigastric or right upper quadrant pain.
Systemic Histaminergic Release (Very Common):
Codeine is a direct non-immunological secretagogue of mast cell degranulation. Ingestion of high doses drives massive, uninhibited peripheral histamine release, manifesting as intense generalized pruritus (itching), facial flushing, urticaria, conjunctival injection, and bronchospasm (particularly hazardous in asthmatic patients).
Sorbitol-Induced Osmotic Toxicity (Specific to Liquid Formulations):
Because Toseina contains high concentrations of sorbitol base, recreational consumption of whole bottles ($100\text{ to }250\text{ mL}$) delivers massive osmotic loads to the bowel, triggering explosive osmotic diarrhea, severe abdominal cramping, and rapid fluid/electrolyte dehydration.
Severe, Emergent and Life-Threatening Hazards (Rare to Overdose):
Catastrophic Central Respiratory Depression and Apnea: Profound suppression of brainstem respiratory drive. Intoxicated individuals display shallow bradypnea ($<4\text{ to }8\text{ breaths/min}$), severe cyanosis, stupor progressing to deep unarousable coma, and fatal hypoxic brain injury or death.
Synergistic “Lean” Toxicity: Co-ingestion with promethazine significantly amplifies respiratory arrest through dual CNS depression, while concurrently precipitating anticholinergic delirium (mydriasis, hyperthermia, urinary retention, bowel ileus) and extrapyramidal movement disorders (acute dystonias).
Physical Dependence and Rapid Escalation: Chronic administration drives rapid down-regulation of $\mu\text{-opioid}$ receptor pathways. Abrupt cessation in dependent individuals precipitates a severe opioid withdrawal syndrome: intense rhinorrhea, lacrimation, piloerection (“cold turkey”), pupil dilation, severe gastrointestinal cramps, vomiting, diarrhea, tachycardia, and unremitting restlessness.
Risks of Illicit Counterfeit Bottles: Street-level Toseina is heavily counterfeited; chemical analyses often identify synthetic nitazene analogues (e.g., metonitazene, protonitazene, isotonitazene), which possess potencies tens to hundreds of times greater than morphine, causing rapid, refractory respiratory arrest that requires massive, repeated doses of naloxone.
The clinical assessment and emergency stabilization of individuals consuming Toseina require strict adherence to opioid safety guidelines, pharmacogenetic screening principles, and harm-minimisation standards:
Contraindications:
Known CYP2D6 Ultra-Rapid Metabolisers: Absolute contraindication due to high risk of fatal morphine toxicity even at standard therapeutic doses.
Severe Respiratory Disease: Absolute contraindication in acute respiratory depression, severe chronic obstructive pulmonary disease (COPD), acute bronchial asthma, or compromised ventilatory drive.
Paediatric Age (<12 Years): Absolute contraindication in all children under 12 years of age; contraindicated in patients aged 12 to 18 years who have compromised respiratory function or following tonsillectomy/adenoidectomy.
Pregnancy and Breastfeeding: Absolute contraindication during breastfeeding (morphine passes into breast milk and has caused fatal respiratory arrest in nursing neonates of ultra-rapid metabolizer mothers); risks neonatal withdrawal syndrome if consumed long-term in pregnancy.
Paralytic Ileus and Toxic Megacolon: Contraindicated in acute bowel obstruction or severe inflammatory bowel conditions.
Head Injury and Raised Intracranial Pressure (ICP): Contraindicated; opioid-induced $\text{CO}_2$ retention promotes cerebral vasodilation, further accelerating dangerous intracranial pressure spikes.
Drug Interactions:
Central Nervous System Depressants (e.g., Alcohol, Benzodiazepines, Barbiturates, GHB/GBL): Synergistic, lethal suppression of medullary respiratory centers; co-ingestion is the leading driver of fatal recreational opioid poisoning.
First-Generation Antihistamines (e.g., Promethazine, Diphenhydramine): Frequently combined in “lean” concoctions; produces synergistic respiratory depression, profound sedation, and severe anticholinergic toxicity.
CYP2D6 Inhibitors (e.g., Fluoxetine, Paroxetine, Bupropion, Quinidine): Blocks the conversion of codeine to active morphine, nullifying therapeutic analgesia while leaving histaminergic and anticholinergic adverse effects intact.
CYP3A4 Inducers (e.g., Rifampicin, Carbamazepine, St John’s Wort): Accelerates conversion to inactive norcodeine, diminishing clinical response.
Monoamine Oxidase Inhibitors (MAOIs): Concurrent use or use within 14 days carries documented risks of hyperpyrexic reactions, central excitation, or severe respiratory depression.
Clinical Precautions and Emergency Management (“Red Flags”):
Acute Opioid Overdose Management (The Opioid Toxidrome): Individuals presenting to NHS emergency departments (999/A&E) with the classic triad of respiratory depression ($<8\text{ breaths/min}$), pinpoint pupils (miosis), and coma/stupor require immediate resuscitation:
Airway and Oxygenation: Prioritize airway patency, position in the recovery position, provide high-flow oxygen, and provide bag-valve-mask ventilatory support.
Naloxone Administration: The specific opioid antagonist naloxone must be administered immediately ($400\text{ mcg}$ IV initially, repeating or escalating to $800\text{ mcg}$ to $2\text{ mg}$ every 2 to 3 minutes if no response is observed, up to $10\text{ mg}$).
Prolonged Monitoring: Converted morphine possesses an active half-life that can outlast the brief duration of action of intravenous naloxone ($30\text{ to }60\text{ minutes}$). Patients who regain consciousness following naloxone must be monitored under continuous cardiac and pulse oximetry for a minimum of 4 to 6 hours to detect “re-narcotization” (recurrent respiratory depression).
Nitazene Suspicion: If counterfeit Toseina adulterated with nitazenes is suspected, massive cumulative doses of naloxone ($>4\text{ to }10\text{ mg}$ IV or continuous IV infusion) may be required to restore and sustain adequate spontaneous ventilation.
Detoxification Protocols: Dependent individuals attempting to cease codeine syrup consumption must not be abruptly stopped without clinical monitoring. Management involves stabilization and tapering regimens utilizing licensed oral opioid substitutes (e.g., buprenorphine or methadone) under structured NHS community drug and alcohol recovery services, coupled with symptomatic management of autonomic withdrawal symptoms (e.g., lofexidine, antiemetics, and loperamide).
Sourcing and Legal Counseling: Clinicians encountering young people presenting with “lean” misuse should deliver frank, non-stigmatizing education detailing the extreme risks of rapid CYP2D6-driven fatal overdose, the high prevalence of lethal synthetic nitazene counterfeits in European syrups, and the severe physical dependence potential associated with codeine-promethazine misuse.
| Menge | 1, 3, 5, 10 |
|---|


 English English
 German
 Italian
 Dutch
 Spanish


Thom J –
anyone looking for top quality pills should come here. very safe website