- Ihr Warenkorb ist leer
- Weiter Einkaufen


Preisklasse: £ 107.30 durch £ 1,184.00
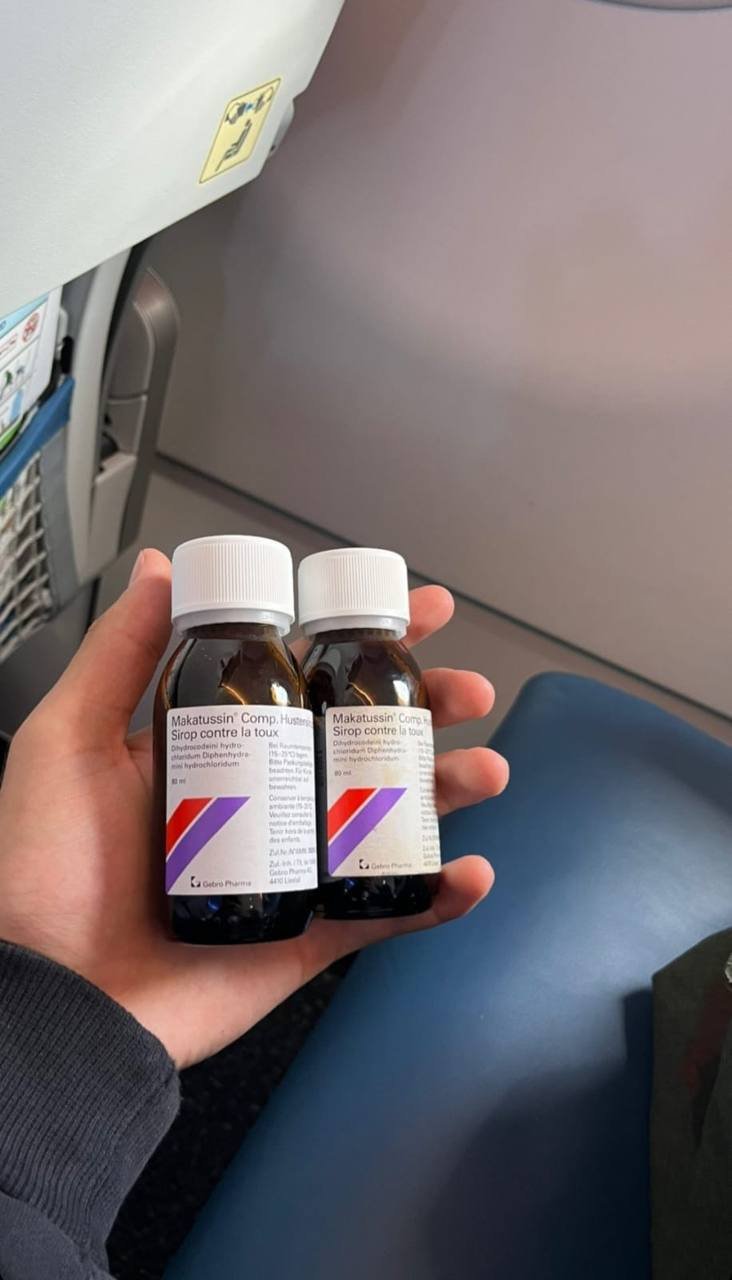
Makatussin Tropfen (Drops) is a proprietary, dual-constituent oral liquid pharmaceutical preparation manufactured by Gebro Pharma AG in Switzerland. The formulation pairs a semi-synthetic morphinan opioid antitussive with a first-generation sedating ethanolamine antihistamine:
Dihydrocodeine Thiocyanate (Dihydrocodeini thiocyanas): Chemically designated as $(4R,4aR,7S,7aR,12bS)\text{-9-methoxy-3-methyl-2,4,4a,5,6,7,7a,12b-octahydro-1H-4,12-methanobenzofuro[3,2-e]isoquinoline-7-ol thiocyanate}$. It is a saturated semi-synthetic derivative of codeine featuring a hydrogenated 7,8-double bond. The thiocyanate salt form yields an average molecular weight of approximately $360.47\text{ g/mol}$ (dihydrocodeine base: $301.38\text{ g/mol}$).
Diphenhydramine Hydrochloride: Chemically designated as $2\text{-(diphenylmethoxy)-N,N-dimethylethanamine hydrochloride}$. It is a classical first-generation antihistamine possessing significant antimuscarinic (anticholinergic) and central sedative properties, with a molecular weight of $291.82\text{ g/mol}$.
Standard pharmaceutical specifications for Makatussin Tropfen provide:
Dihydrocodeine thiocyanate: $10\text{ mg/g}$ ($\approx 10\text{ mg/mL}$)
Diphenhydramine hydrochloride: $15\text{ mg/g}$ ($\approx 15\text{ mg/mL}$)
An individual $80\text{ mL}$ ($80\text{ g}$) amber glass dropper bottle delivers a cumulative active payload of $800\text{ mg}$ of dihydrocodeine thiocyanate und $1,200\text{ mg}$ of diphenhydramine hydrochloride. Inverted drops typically deliver approximately $0.5\text{ mg}$ of dihydrocodeine and $0.75\text{ mg}$ of diphenhydramine per drop ($20\text{ drops} \approx 1\text{ g} / 1\text{ mL}$). The vehicle is an aqueous-alcoholic solution (containing ethanol $\approx 5.1\%\text{ v/v}$), sorbitol, saccharin sodium, sodium cyclamate, and aromatic excipients.
Within regulatory frameworks:
Swiss Regulatory Status (Swissmedic): Categorized under Abgabekategorie B (Supply Category B / Prescription Only Medicine). Due to substantial recreational diversion, Swiss authorities enforce strict distribution controls, preventing automatic repeat dispensing without renewed medical authorization.
United Kingdom Regulatory Framework: Makatussin is not an MHRA-licensed medicine and is absent from the NHS Drug Tariff. Under equivalent domestic statutes:
Single-entity or concentrated dihydrocodeine liquid preparations fall under Class B, Schedule 2 Controlled Drugs (CD POM) of the Misuse of Drugs Act 1971 / Misuse of Drugs Regulations 2001.
Diphenhydramine is a Pharmacy (P) / Prescription Only Medicine (POM) depending on indication and strength.
Illicit Diversion and “Lean” Culture: Makatussin 80ml bottles are heavily trafficked across European and UK illicit secondary markets. Because the formulation already combines an opioid with a sedating antihistamine in a single dropper bottle, it is heavily sought after as a ready-made base for recreational “lean” / “purple drank” concoctions (typically mixed with sweet sodas and confectionery). Counterfeit bottles circulating on darknet and messaging platforms frequently substitute the active ingredients with novel synthetic nitazene opioids (e.g., protonitazene, metonitazene) or designer benzodiazepines, introducing critical poisoning risks.
The pharmacodynamic profile of Makatussin is driven by the synergistic interaction of direct $\mu$-opioid receptor agonism, central histamine $H_1$ receptor antagonism, and muscarinic blockade:
Dihydrocodeine Pharmacodynamics:
$\mu$-Opioid (MOP) Receptor Agonism: Dihydrocodeine binds directly as an agonist to human $\mu$-opioid receptors located within the dorsal horn of the spinal cord, periaqueductal gray, and the medulla oblongata. Coupling to inhibitory $G_{\alpha i/o}$ proteins inhibits adenylyl cyclase, lowers cyclic adenosine monophosphate (cAMP), closes presynaptic voltage-gated N-type $Ca^{2+}$ channels, and opens postsynaptic inwardly rectifying potassium (GIRK) channels, suppressing excitatory neurotransmission.
Direct Intrinsic Efficacy: Unlike codeine (which acts almost entirely as a prodrug requiring CYP2D6 bioactivation into morphine), dihydrocodeine possesses meaningful direct intrinsic receptor affinity ($\sim 10$-fold higher affinity for $\mu$-receptors than parent codeine). A portion is also metabolized via CYP2D6 to dihydromorphine, but baseline pharmacodynamic efficacy persists regardless of CYP2D6 metabolizer status.
Central Cough Suppression: Dihydrocodeine directly suppresses the medullary cough reflex center located in the nucleus tractus solitarii, dampening autonomic and somatic coughing triggers.
Diphenhydramine Pharmacodynamics:
Histamine $H_1$ Receptor Inverse Agonism: Diphenhydramine competitively occupies postsynaptic $H_1$ receptors across the tuberomammillary nucleus and cerebral cortex, preventing endogenous histamine from promoting wakefulness, driving profound sedation.
Central Muscarinic Anticholinergic Blockade: It acts as an antagonist at muscarinic acetylcholine receptors ($M_1\text{ to }M_5$), suppressing bronchial secretions, reducing rhinorrhea, and inducing peripheral antimuscarinic effects (dry mouth, urinary retention, mydriasis).
Synergistic Central Nervous System Depression: The concurrent stimulation of $\mu$-opioid pathways and blockade of histaminergic wake-promoting centers produces powerful, multiplicative CNS and respiratory depression:
Pontomedullary respiratory pacemakers (pre-Bötzinger complex) suffer blunted sensitivity to arterial hypercapnia ($\text{PaCO}_2$) and hypoxia.
Diphenhydramine also suppresses opioid-induced nausea and vomiting (via CTZ vestibular inhibition) and counters opioid-mediated histamine release (pruritus), which inadvertently allows recreational users to consume massive, otherwise intolerable opioid doses.
Where formally authorized under Swissmedic guidelines, Makatussin Tropfen holds a strictly limited therapeutic indication:
Severe, Unproductive Cough (Symptomatic Treatment):
Indicated for the short-term relief of severe, painful, non-productive dry cough in adults and adolescents aged 18 years and older when non-opioid cough suppressants are ineffective.
Standard Adult Therapeutic Dosing: $15\text{ to }20\text{ drops}$ taken three to four times daily (delivering $\approx 7.5\text{ to }10\text{ mg}$ dihydrocodeine thiocyanate and $\approx 11.25\text{ to }15\text{ mg}$ diphenhydramine hydrochloride per dose).
Maximum Daily Ceiling: Doses must not exceed $30\text{ drops}$ four times daily (maximum $\approx 60\text{ mg}$ dihydrocodeine / $90\text{ mg}$ diphenhydramine daily).
Duration Limit: Use must be limited to a maximum of 3 to 5 days. Persistent cough warrants immediate diagnostic reassessment to rule out underlying infections or malignancy.
Contraindication in Paediatrics (<18 Years):
Strictly contraindicated in children and adolescents under 18 years of age due to the risk of fatal central respiratory depression and unpredictable opioid toxicity.
In UK clinical practice, NICE guidelines (CKS: Cough) advise against opioid antitussives for routine acute cough, favoring simple non-medicated demulcents (e.g., honey, glycerol).
In non-medical, recreational contexts, Makatussin 80ml is misused for:
“Lean” Concoctions: Recreational users ingest large volumes (e.g., $20\text{ to }40\text{ mL}$, delivering $200\text{ to }400\text{ mg}$ of dihydrocodeine alongside $300\text{ to }600\text{ mg}$ of diphenhydramine) diluted into sweet carbonated beverages. This produces euphoric dissociation, heavy somatic warmth, profound sedation, and auditory/visual sensory alterations.
Opioid Withdrawal Self-Management: Ingested in non-prescribed amounts to alleviate autonomic storms and restlessness during abstinence from other opioids.
The pharmacokinetics of Makatussin involve rapid oral liquid absorption, extensive hepatic metabolism, and divergent elimination kinetics between its two active constituents:
| Pharmacokinetic Parameter | Dihydrocodeine Thiocyanate | Diphenhydraminhydrochlorid |
| Oral Bioavailability | $\sim 20\%$ (first-pass hepatic extraction) | $\sim 40\text{ to }60\%$ (variable first-pass) |
| Peak Concentration ($T_{max}$) | $1.0\text{ to }2.0\text{ hours}$ | $1.5\text{ to }3.0\text{ hours}$ |
| Volume of Distribution ($V_d$) | $\sim 1.0\text{ to }1.5\text{ L/kg}$ | $\sim 3.0\text{ to }4.5\text{ L/kg}$ |
| Plasma Protein Binding | $\sim 10\text{ to }20\%$ (Low) | $\sim 70\text{ to }85\%$ (Moderate) |
| Primary Hepatic Enzymes | UGT2B7 (major), CYP2D6, CYP3A4 | CYP2D6 (major), CYP1A2, CYP2C9, CYP2C19 |
| Active Metabolites | Dihydromorphine, DH6G | Nordiphenhydramine (weak) |
| Elimination Route | Renal ($>90\%$, primarily glucuronides) | Renal ($>80\%$, polar metabolites) |
| Elimination Half-Life ($t_{1/2}$) | $3.5\text{ to }5.0\text{ hours}$ | $4.0\text{ to }9.0\text{ hours}$ (prolonged in elderly) |
Dihydrocodeine Clearance:
The primary pathway is Phase II glucuronidation via UGT2B7 to dihydrocodeine-6-glucuronide (DH6G) ($\sim 60\%$).
A secondary oxidative pathway via CYP2D6 ($\sim 5\text{ to }10\%$) yields dihydromorphine, an active $\mu$-opioid agonist with affinity comparable to morphine.
Diphenhydramine Clearance and Metabolic Collision:
Diphenhydramine is metabolized predominantly by CYP2D6 into nordiphenhydramine.
Pharmacokinetic Interaction: Diphenhydramine is both a substrate and a moderate-to-strong competitive inhibitor of CYP2D6. In high-dose recreational ingestion, diphenhydramine partially autoinhibits its own clearance and blocks the conversion of dihydrocodeine to dihydromorphine. However, because parent dihydrocodeine has intrinsic activity, overall opioid analgesia and sedation remain potent, while diphenhydramine plasma levels accumulate, prolonging anticholinergic delirium and sedation.
Therapeutic dosing suppresses non-productive coughing and induces light drowsiness. In supratherapeutic, recreational, or chronic exposure, multi-system toxicities emerge from combined opioid and anticholinergic mechanisms:
Central Nervous System & Psychiatric Manifestations:
Somnolence, lethargy, cognitive clouding, slurred speech, and psychomotor impairment.
Anticholinergic Delirium (Diphenhydramine Toxicity): In high-dose recreational consumption ($>300\text{ to }600\text{ mg}$ of diphenhydramine), anticholinergic toxicity manifests as visual and auditory hallucinations, restlessness, memory loss, paranoia, and fragmented speech.
Paradoxical central excitation, tremors, or seizures (especially in pediatric poisoning).
Autonomic and Gastrointestinal Effects:
Severe Constipation: Enteric $\mu$-opioid agonism combined with muscarinic receptor blockade halts gut motility, presenting significant risks of fecal impaction or paralytic ileus.
Xerostomia (extreme dry mouth), blurred vision (cycloplegia), pupillary changes (competing miosis from dihydrocodeine and mydriasis from diphenhydramine), and cutaneous flushing.
Urinary Retention: Detrusor muscle relaxation and internal sphincter constriction can cause acute, painful bladder distension.
Cardiovascular Dysregulation:
Sinus tachycardia (anticholinergic vagal block), arterial hypotension, or orthostatic collapse.
Cardiac Conduction Delay: High-dose diphenhydramine blocks cardiac sodium channels and potassium rectifying channels ($I_{Kr}$), which can widen the QRS complex and prolong the QTc interval, conferring pro-arrhythmic liabilities (Torsades de Pointes).
Severe, Emergent and Life-Threatening Hazards:
Fatal Respiratory Arrest: The primary cause of death. Synergistic medullary depression blunts autonomic ventilatory drive, progressing from bradypnea ($<8\text{ breaths/min}$) and cyanosis to deep coma, hypoxemic brain injury, and fatal asystole.
Aspiration Pneumonitis: Profound sedation coupled with blunted laryngeal and pharyngeal protective airway reflexes carries high risks of pulmonary aspiration of gastric contents.
Physical Dependence and Polysubstance Withdrawal: Chronic use induces rapid neuroadaptation. Abrupt discontinuation precipitates a mixed withdrawal syndrome:
Opioid withdrawal: Rhinorrhea, lacrimation, piloerection (“cold turkey”), abdominal cramps, severe diarrhea, and myalgias.
Anticholinergic rebound: Profuse diaphoresis, severe nausea, vomiting, insomnia, and intense anxiety.
Counterfeit Nitazene Adulteration: Illicit bottles labeled as Makatussin frequently contain synthetic nitazene opioids (e.g., protonitazene, metonitazene), triggering rapid, refractory respiratory collapse that requires massive, escalated doses of naloxone.
Safe management and emergency evaluation of individuals exposed to Makatussin require adherence to opioid safety guidelines, anticholinergic screening, and respiratory risk stratification:
Contraindications:
Paediatric Age (<18 Years): Absolute contraindication.
Acute Respiratory Compromise: Severe asthma, acute respiratory failure, severe chronic obstructive pulmonary disease (COPD), or compromised ventilatory drive.
Closed-Angle Glaucoma: Absolute contraindication due to diphenhydramine-induced pupillary dilation and increased intraocular pressure.
Prostatic Hyperplasia and Urinary Retention: Contraindicated due to risk of precipitating acute, total urinary obstruction.
Gastrointestinal Obstruction: Paralytic ileus, stenosing peptic ulcer, or pyloroduodenal obstruction.
Concurrent Monoamine Oxidase Inhibitors (MAOIs): Absolute contraindication during or within 14 days of MAOI therapy (risks hyperpyrexic crisis, severe anticholinergic storm, or cardiovascular collapse).
Pregnancy and Breastfeeding: Contraindicated during pregnancy (risks neonatal respiratory depression and neonatal opioid withdrawal syndrome [NOWS]); contraindicated in breastfeeding (both dihydrocodeine and diphenhydramine distribute into maternal milk, posing risks of infant apnea).
Drug Interactions:
Central Nervous System Depressants (Alcohol, Benzodiazepines, Antipsychotics, Sedating Antihistamines): Synergistic medullary respiratory depression, profound sedation, coma, and fatal poisoning.
Gabapentinoids (Pregabalin, Gabapentin): Marked amplification of central hypoventilation and fatal overdose risk.
CYP2D6 Inhibitors (e.g., Fluoxetine, Paroxetine, Bupropion): Blocks metabolic clearance of diphenhydramine and conversion of dihydrocodeine, elevating systemic diphenhydramine exposure and anticholinergic toxicity.
Other Anticholinergic Agents (Tricyclic Antidepressants, Atropine, Antimuscarinics): Additive antimuscarinic burden, sharply elevating the risk of anticholinergic delirium, hyperthermia, and paralytic ileus.
Clinical Precautions and Emergency Overdose Management (“Red Flags”):
Acute Mixed Overdose Presentation: Patients presenting to emergency departments (999/A&E) with Makatussin overdose present with a complex “hybrid toxidrome” combining opioid depression (bradypnea, coma) with anticholinergic signs (tachycardia, dry skin/mucosae, dilated or mid-position pupils, QTc prolongation, urinary retention):
Airway and Oxygenation: Clear the airway, position in the recovery position, deliver high-flow oxygen, and provide bag-valve-mask or mechanical ventilation immediately.
Naloxone Administration: Administer intravenous naloxone ($400\text{ mcg}$ IV initially, repeating or titrating up to $800\text{ mcg}$ to $2\text{ mg}$ every 2 to 3 minutes, up to $10\text{ mg}$ as needed to restore spontaneous respiration).
Caution: Naloxone reverses opioid-mediated respiratory depression, but does not reverse diphenhydramine-induced sedation, seizures, or anticholinergic delirium. Reversing the opioid component may unmask acute anticholinergic agitation.
Cardiac and ECG Surveillance: Perform continuous 12-lead ECG monitoring. If wide-complex dysrhythmias occur secondary to sodium channel blockade, administer intravenous sodium bicarbonate ($8.4\%$, $1\text{ to }2\text{ mmol/kg}$).
Extended Monitoring Window: Because dihydrocodeine and diphenhydramine have elimination half-lives of $3.5\text{ to }9\text{ hours}$ (outlasting naloxone’s $30\text{ to }60\text{ minute}$ duration of action), patients must be monitored under continuous pulse oximetry and telemetry for a minimum of 12 to 24 hours to prevent fatal “re-narcotization.”
Detoxification Protocols: Chronic dependent users must not be stopped abruptly without clinical support. Structured detoxification utilizes cross-tapering to oral opioid maintenance therapy (e.g., buprenorphine or methadone) alongside symptomatic management for cholinergic rebound under community addiction recovery services.
Driving Regulations: Makatussin severely impairs cognitive processing and motor coordination. Operating vehicles or heavy machinery is strictly prohibited during use.
| Flaschen | 1, 3, 5, 10, 20 |
|---|
 English English
 German
 Italian
 Dutch
 Spanish