- Ihr Warenkorb ist leer
- Weiter Einkaufen


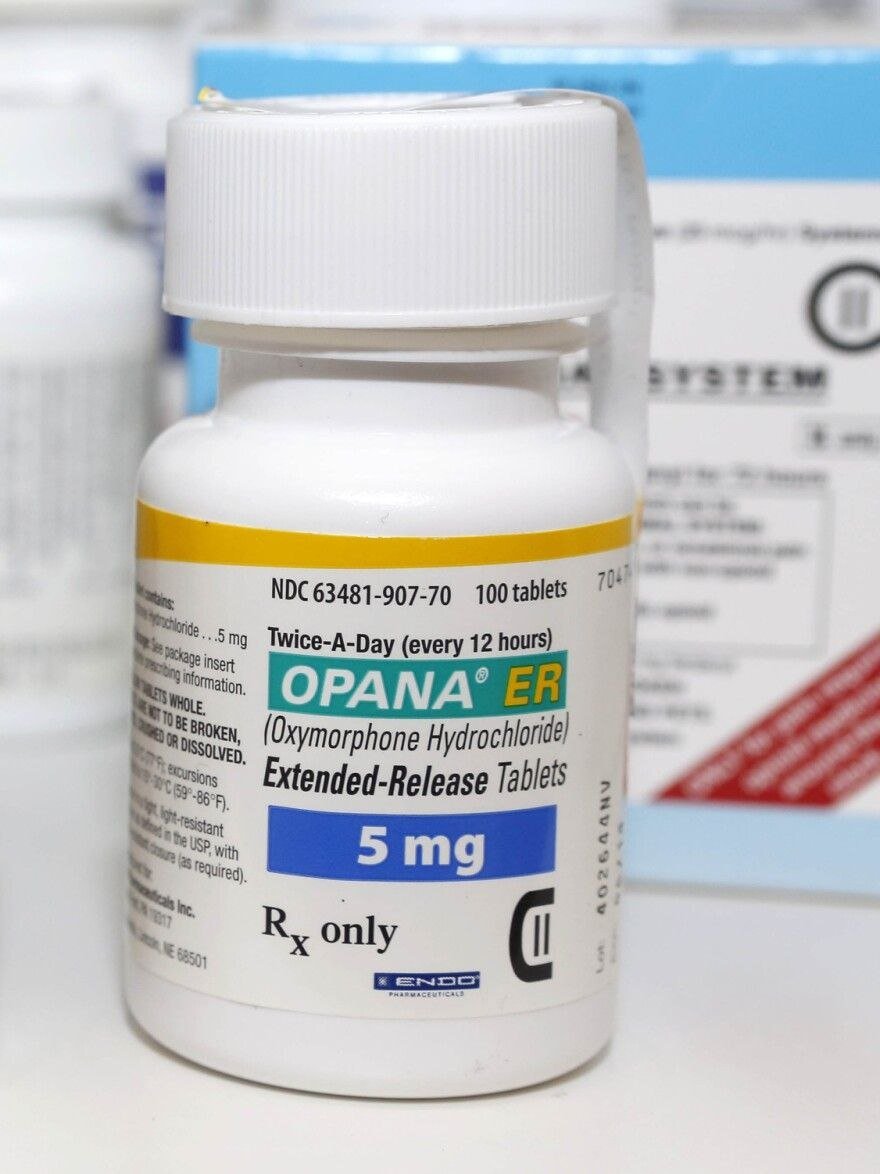
£ 96.20
Oxymorphone is a potent, semi-synthetic pure opioid agonist derived from morphine. It is indicated for the management of moderate to severe acute and chronic pain requiring continuous, round-the-clock opioid analgesia.
Oxymorphone is a phenanthrene-derivative opioid alkaloid. Chemically designated as 4,5$\alpha$-epoxy-3,14-dihydroxy-17-methylmorphinan-6-one hydrochloride, it is a primary active metabolite of oxycodone as well as a standalone pharmaceutical entity. Under the Anatomical Therapeutic Chemical (ATC) system, oxymorphone is indexed under N02AA05.
Oxymorphone is classified internationally as a highly strictly Controlled Substance (e.g., Schedule II under the US Controlled Substances Act; Schedule 2 / Class A Controlled Drug in the UK) due to its high potency, profound abuse liability, and physical dependence risk. It is regulated strictly as a Prescription Only Medicine (POM).
Oxymorphone functions as a full, high-affinity agonist at central nervous system opioid receptors:
-Opioid Receptor Agonism: Binds with high selectivity and affinity to central -opioid receptors (-OR), inhibiting adenylyl cyclase, hyperpolarizing neurons, and suppressing the transmission of ascending nociceptive signals in the spinal cord dorsal horn and brainstem.
Analgesic Potency: Possesses a significantly higher intrinsic analgesic potency compared to morphine (roughly 3 times more potent orally and up to 10 times more potent parenterally).
Licensing for oxymorphone includes:
Moderate to Severe Acute and Chronic Pain: Management of moderate to severe pain where alternative treatment options (such as non-opioid analgesics or lower-potency opioids) are inadequate, and where around-the-clock continuous opioid therapy is required.
Dosing & Administration Regimen:
Formulation Variances: Available as immediate-release (IR) oral tablets and extended-release (ER) tablets designed for prolonged 12-hour coverage.
Titration Protocol: Dosage must be individualized based on pain severity, prior opioid exposure, and patient risk factors. Initiation in opioid-naive patients carries severe risks of fatal overdose.
Administration Integrity (Extended-Release): ER tablets must be swallowed whole with water on an empty stomach (food significantly increases peak plasma concentrations). Do not cut, crush, chew, or dissolve ER tablets, as destruction of the polymer delivery matrix causes immediate drug dumping and lethal overdose.
Absorption: Oral bioavailability of immediate-release oxymorphone is low (~10%) due to extensive first-pass hepatic metabolism. Food intake increases systemic absorption significantly (up to 50% for IR and over 100% for certain ER formulations). Peak plasma concentrations occur within 0.5 to 1.5 hours for IR and 2 to 3 hours for ER.
Distribution: Rapidly distributes across tissue compartments. Plasma protein binding is low to moderate (~10% to 12%).
Biotransformation: Extensively metabolized in the liver primarily via non-CYP pathways:
Glucuronidation (Major): Metabolized via UGT2B7 to oxymorphone-3-glucuronide (inactive metabolite).
Reduction (Minor): Converted to 6--oxymorphol. Oxymorphone does not undergo significant Cytochrome P450-mediated metabolism, reducing certain drug-drug interaction liabilities.
Elimination: Excreted predominantly via the kidneys in urine as conjugated metabolites and unchanged drug (< 1%). The terminal elimination half-life () averages 7 to 10 hours for extended-release formulations.
Oxymorphone depresses central nervous system functions, blunts respiratory drive, slows gastrointestinal motility, and alters vascular tone.
Very Common (): Constipation, nausea, somnolence, dizziness, vomiting, pruritus, headache.
Common ( to ): Dry mouth, insomnia, anxiety, confusion, fatigue, excessive sweating, hyperhidrosis, dyspepsia, abdominal pain, diarrhea, urinary retention.
Uncommon ( to ): Orthostatic hypotension, palpitations, flushing, syncope, paresthesia, visual disturbances, urticaria, rash.
Rare / Severe (<1/1,000): Life-threatening respiratory depression, apnea, circulatory depression, anaphylactoid reactions, bronchospasm, paralytic ileus, physical dependence, and severe withdrawal syndrome.
Known hypersensitivity to oxymorphone or formulation excipients.
Significant respiratory depression or acute severe bronchial asthma in an unmonitored setting.
Known or suspected gastrointestinal obstruction, including paralytic ileus.
Moderate-to-severe hepatic impairment (due to markedly increased systemic exposure and reduced clearance).
Concomitant use with Monoamine Oxidase Inhibitors (MAOIs) or within 14 days of their discontinuation.
CNS Depressants, Benzodiazepines, Alcohol, & Other Opioids: Co-administration produces profound, synergistic central nervous system and respiratory depression, dramatically increasing the risk of fatal overdose, coma, and respiratory arrest.
Alcohol Interaction with Extended-Release: Co-ingestion of alcohol with extended-release oxymorphone formulations can cause rapid dissolution and dose dumping of the active drug, leading to fatal plasma concentrations.
Boxed Warning (Addiction, Abuse, and Misuse): Oxymorphone exposes patients to risks of addiction, abuse, and misuse, which can lead to overdose and death. Assess each patient’s risk prior to prescribing and monitor regularly.
Boxed Warning (Life-Threatening Respiratory Depression): Serious, life-threatening, or fatal respiratory depression may occur. Monitor patients closely, especially during initiation or following dose titration.
Dependence & Withdrawal: Prolonged continuous administration establishes physical and psychological dependence. Abrupt cessation triggers a severe withdrawal syndrome. Gradual medical tapering is mandatory.


 English English
 German
 Italian
 Dutch
 Spanish

