- Tu carrito está vacío
- Continuar comprando


£ 38.48
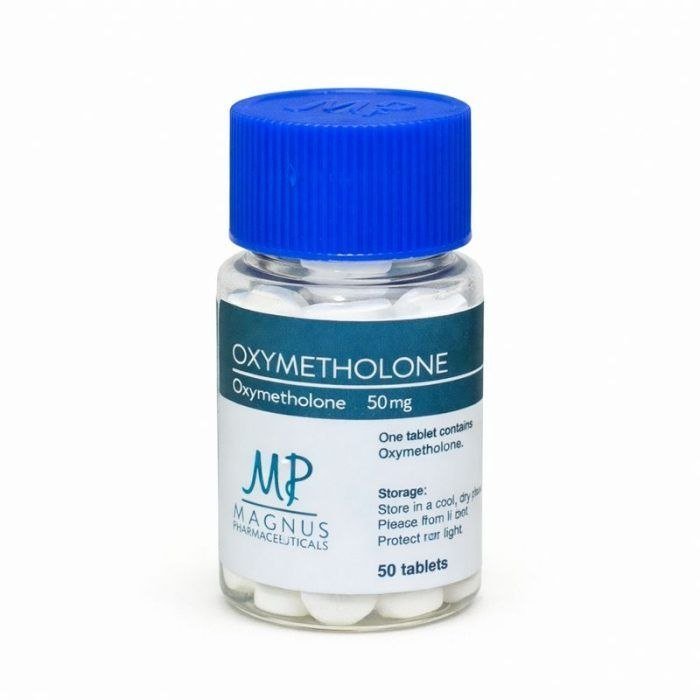
Unlicensed, Class C synthetic oral $17\alpha\text{-alkylated}$ anabolic-androgenic steroid, investigated for potent erythropoietic stimulation, severe hepatotoxicity, and non-aromatising oestrogenic activity.
Meta Description:
UK clinical monograph on oxymetholone (Anadrol) detailing $17\alpha$-alkylation, unique non-aromatising oestrogenic activity, severe hepatotoxicity, and Class C regulatory status.
Oxymetholone (chemically designated as $17\beta\text{-hydroxy-2-(hydroxymethylene)-17}\alpha\text{-methyl-5}\alpha\text{-androstan-3-one}$) is a potent synthetic oral anabolic-androgenic steroid (AAS) derived from dihydrotestosterone (DHT). Structurally, the molecule features two critical modifications to the saturated $5\alpha\text{-androstane}$ core: the substitution of a 2-hydroxymethylene group at the carbon-2 position of the A-ring, and the introduction of an alpha-oriented methyl group at the carbon-17 position ($17\alpha\text{-alkylation}$). The 2-hydroxymethylene moiety stabilizes the 3-keto group, significantly enhancing anabolic potency while preventing enzymatic reduction by skeletal muscle $3\alpha\text{-hydroxysteroid dehydrogenase}$ ($3\alpha\text{-HSD}$). The $17\alpha\text{-methyl}$ substitution confers steric hindrance against presystemic hepatic $17\beta\text{-hydroxy}$ oxidation, rendering the compound orally bioavailable. In clinical and underground manufacturing, oxymetholone is formulated as oral tablets (historically standardized at $50\text{ mg}$ per unit under proprietary names such as Anadrol-50 or Anapolon) alongside excipients including lactose, povidone, magnesium stearate, and starch.
Within the United Kingdom regulatory framework, oxymetholone currently holds no active marketing authorisation (MA) from the Medicines and Healthcare products Regulatory Agency (MHRA). While historically licensed under trade names such as Anapolon for the treatment of refractory aplastic anaemias, myelofibrosis, and severe catabolic states, all human medicinal product licenses within the UK have been discontinued or formally withdrawn. Under the Misuse of Drugs Act 1971 and the Misuse of Drugs Regulations 2001, oxymetholone is scheduled as a Class C, Schedule 4 (Part II) controlled drug. It is not catalogued as an active formulary agent in the British National Formulary (BNF) and is absent from NHS prescribing pathways. Modern formulations circulating domestically originate predominantly from illicit underground laboratories (UGLs) or unverified foreign grey-market imports, presenting significant clinical hazards regarding active pharmaceutical ingredient (API) dosing errors, heavy metal contamination, and microbiological non-sterility.
The pharmacodynamic profile of oxymetholone involves direct androgen receptor interaction, high-affinity stimulation of erythropoiesis, unconventional oestrogenic signalling, and pronounced neuroendocrine feedback suppression:
Androgen Receptor (AR) Agonism and Myofibrillar Anabolism: Following gastrointestinal absorption, intact oxandrolone binds directly to intracellular androgen receptors in skeletal muscle, bone, and bone marrow stromal cells. Despite exhibiting a relatively low binding affinity for the isolated AR compared to testosterone or DHT, oxymetholone exerts profound transcriptional activity once bound to androgen response elements (AREs) on genomic DNA. This drives RNA polymerase II-directed transcription, stimulating intense cellular nitrogen retention, amino acid incorporation, and myofibrillar contractile protein synthesis. It possesses a high therapeutic ratio in preclinical models, with an anabolic-to-androgenic dissociation index estimated at approximately $320:45$ (relative to methyltestosterone at $100:100$).
Stimulation of Erythropoiesis: Oxymetholone is exceptionally potent in augmenting circulating red blood cell mass. It acts directly on renal erythropoietin-producing peritubular cells to upregulate erythropoietin (EPO) gene transcription, while simultaneously exerting a direct, marrow-stimulating effect on erythroid progenitor cells (erythroblasts), accelerating reticulocytosis and haemoglobin synthesis.
Non-Aromatase-Dependent Oestrogenic Activity: Because the steroid nucleus is fully $5\alpha\text{-reduced}$, oxymetholone cannot serve as a substrate for the cytochrome P450 aromatase enzyme complex ($CYP19A1$). It undergoes zero metabolic conversion into $17\beta\text{-oestradiol}$. However, oxymetholone paradoxically induces profound clinical oestrogenic effects, including severe extracellular water retention and gynaecomastia. Pharmacological evidence suggests this occurs via direct intrinsic agonism at the oestrogen receptor alpha ($ER\alpha$) or via complex interactions with intracellular progestogenic and oestrogenic response pathways, which are not mitigated by aromatase inhibitors.
Absence of $5\alpha\text{-Reductase}$ Amplification: Because the A/B ring junction is already saturated in the $5\alpha\text{-configuration}$, oxymetholone does not undergo metabolic amplification by $5\alpha\text{-reductase}$ isoenzymes into a more potent androgenic species in peripheral target tissues (prostate, scalp, sebaceous units). Its biological effects are mediated directly by the parent molecule and its primary metabolites.
Profound Hypothalamic-Pituitary-Gonadal (HPG) Axis Suppression: Oxymetholone exerts severe negative feedback inhibition at the hypothalamic arcuate nucleus and anterior pituitary gonadotrophs. Supraphysiological titers suppress gonadotropin-releasing hormone (GnRH), luteinising hormone (LH), and follicle-stimulating hormone (FSH) secretion, resulting in rapid shutdown of endogenous testicular testosterone production.
Oxymetholone possesses no approved clinical indications in the United Kingdom. No active pharmaceutical preparations containing oxymetholone are currently licensed or available for human prescription within the NHS.
The National Institute for Health and Care Excellence (NICE) does not endorse, recommend, or integrate oxymetholone into any contemporary clinical pathway. It is absent from modern guidelines governing aplastic anaemia, myelodysplastic syndromes, or chronic kidney disease-associated anaemia. In modern haematological practice, legacy androgen therapies have been entirely superseded by recombinant human erythropoietins (epoetin alfa/beta, darbepoetin alfa), immunosuppressive therapy (anti-thymocyte globulin, ciclosporin), thrombopoietin receptor agonists (eltrombopag), and allogeneic haematopoietic stem cell transplantation. In authorized overseas jurisdictions (e.g., US FDA), oxymetholone has historically maintained orphan indications for:
Treatment of anaemias caused by deficient red cell production (acquired aplastic anaemia, congenital aplastic anaemia [Fanconi anaemia], myelofibrosis, and hypoplastic anaemias).
Reversal of profound cachexia and muscle wasting secondary to advanced human immunodeficiency virus (HIV) infection.
The practical application of oxymetholone is confined entirely to illicit athletic performance enhancement, competitive bodybuilding, and forensic doping toxicology. In these unapproved settings, it is sought for:
Rapid, massive accrual of gross body mass and skeletal muscle volume during off-season phases (“bulking”).
Acute augmentation of maximal isometric and dynamic muscular strength.
Intense connective tissue hydration and perceived joint lubrication secondary to intracellular and extracellular fluid retention.
Oxymetholone holds no status within the NHS drug tariff, cannot be prescribed on NHS prescription forms (FP10), and must never be substituted for licensed testosterone replacement therapy (TRT).
Because oxymetholone is formulated as an oral solid tablet, its pharmacokinetic disposition is determined by rapid intestinal uptake, extensive hepatic resistance, and mixed renal-biliary elimination:
Absorption: Oxymetholone exhibits high oral bioavailability ($>80\%$) owing to its lipophilicity and structural $17\alpha\text{-alkylation}$, which protects the molecule from complete first-pass hepatic oxidation. Following oral ingestion of a standard $50\text{ mg}$ tablet in a fasted state, peak plasma concentrations ($C_{max}$) are achieved rapidly, typically between 1.5 and 3 hours.
Distribution: Following absorption, oxymetholone circulates in systemic blood bound to serum proteins. It exhibits low affinity for sex hormone-binding globulin (SHBG), circulating predominantly bound to human serum albumin or in an unbound, biologically active fraction. It possesses an apparent volume of distribution ($V_d$) ranging from $0.4\text{ to }0.7\text{ L/kg}$, readily distributing into skeletal muscle, hepatic parenchyma, renal tissues, and traversing the blood-brain barrier.
Biotransformation: Oxymetholone undergoes extensive, complex hepatic clearance mediated by Phase I oxidative/reductive pathways and Phase II conjugation. The primary metabolic route involves the enzymatic loss or cleavage of the 2-hydroxymethylene group, generating $17\alpha\text{-methyl-5}\alpha\text{-androstan-17}\beta\text{-ol}$ y $17\alpha\text{-methyl-5}\alpha\text{-androstane-3}\alpha,17\beta\text{-diol}$ (mestanolone derivatives), followed by epimerisation, hydroxylation, and glucuronidation via UDP-glucuronosyltransferases (UGTs).
Elimination: Systemic elimination is multi-phasic. Approximately $50\text{ to }60\%$ of administered dose metabolites are cleared in the urine as glucuronide and sulfate conjugates, with the remaining fraction excreted via the biliary system into faeces. The terminal elimination half-life ($t_{1/2}$) in humans is estimated between 8 and 16 hours, typically requiring split-dose oral administration in illicit protocols to maintain stable serum concentrations. Retrospective urinary metabolites remain detectable via gas chromatography-mass spectrometry (GC-MS) or LC-MS/MS anti-doping assays for up to 8 to 12 weeks post-cessation.
The primary physiological effect reported in non-medical contexts is an exceptionally rapid accrual of body mass, extreme muscular fullness, and significant strength gains, accompanied by marked extracellular water retention. However, because oxymetholone is a potent oral $17\alpha\text{-alkylated}$ compound with non-aromatising oestrogenic actions, it carries one of the most severe multi-system adverse event spectra among all synthetic androgens:
Hepatic Toxicity (Hepatotoxicity):
As an oral $17\alpha\text{-alkylated}$ steroid, oxymetholone places severe metabolic and excretory strain on hepatocytes and biliary canaliculi. Significant elevations in serum transaminases (ALT, AST), alkaline phosphatase (ALP), and gamma-glutamyl transferase (GGT) occur consistently with supraphysiological dosing.
Prolonged administration carries a high risk of chronic intrahepatic cholestasis (manifesting with pruritus and jaundice), peliosis hepatis (formation of blood-filled parenchymal cysts that can rupture and cause fatal intra-abdominal haemorrhage), benign hepatic adenomas, and, rarely, malignant hepatocellular carcinoma.
Cardiovascular and Lipid Toxicity:
Severe atherogenic dyslipidaemia: oral $17\alpha\text{-alkylated}$ steroids exert potent, direct stimulatory effects on hepatic triglyceride lipase. Oxymetholone induces catastrophic suppression of high-density lipoprotein cholesterol (HDL-C; routinely falling below $0.2\text{ to }0.3\text{ mmol/L}$) and marked elevations in low-density lipoprotein cholesterol (LDL-C), accelerating systemic arterial atherogenesis.
Volume-overload systemic hypertension: profound sodium and water retention induced via renal and non-aromatising oestrogenic pathways causes significant blood pressure spikes, straining cerebrovascular and coronary vessels.
Polycythaemia: intense stimulation of erythropoietin drives haematocrit ($>54\%$) and hemoglobin to pathological levels, drastically increasing whole-blood viscosity and the risk of thromboembolic events (myocardial infarction, ischaemic stroke, pulmonary embolism).
Concentric left ventricular hypertrophy (LVH): sustained exposure promotes pathological myocardial remodeling and impaired diastolic filling.
Endocrine and Oestrogenic Disturbances:
Severe suppression of the HPG axis: negative feedback causes rapid testicular atrophy, azoospermia, and prolonged secondary hypogonadotrophic hypogonadism following drug withdrawal.
Severe Gynaecomastia: proliferation of glandular mammary tissue occurs readily; because this is driven by direct receptor agonism rather than aromatisation, it is refractory to aromatase inhibitors (e.g., anastrozole, letrozole) and requires selective oestrogen receptor modulators (SERMs, such as tamoxifen) or surgical excision.
Androgenic and Dermatological Effects:
Severe cystic acne (especially across the back, shoulders, and chest), oily skin, and accelerated androgenetic alopecia in genetically predisposed individuals.
Virilisation in Females: Profound, irreversible virilising signs, including deepening of the vocal cords, clitoromegaly, severe hirsutism, facial hair growth, and chronic amenorrhoea.
Given its non-approved clinical status, oral hepatotoxic structure, and marked cardiovascular toxicity, oxymetholone requires strict adherence to pharmacological contraindications and harm-minimisation standards:
Contraindications:
Absolute Contraindication in All Humans: The preparation is an illicit, unregulated chemical tablet lacking medicinal safety clearance.
Known or Suspected Malignancy: Absolute contraindication in prostate adenocarcinoma, male breast carcinoma, or any hormone-sensitive neoplasm; absolute contraindication in known or suspected active hepatic neoplasms.
Severe Hepatic Impairment: Absolute contraindication in patients with baseline liver cirrhosis, active viral or autoimmune hepatitis, cholestatic liver disease, or baseline transaminases exceeding three times the upper limit of normal (ULN).
Pre-existing Cardiovascular Disease: Absolute contraindication in severe coronary artery disease, history of myocardial infarction, cerebrovascular disease (stroke/TIA), uncontrolled hypertension, or chronic heart failure.
Severe Renal Impairment: Contraindicated in nephrotic syndrome or chronic kidney disease (CKD Stages 4–5).
Pregnancy and Lactation: Absolute contraindication; severe teratogenicity, fatal fetal harm, and irreversible masculinisation/virilisation of the female fetus.
Paediatric Population: Absolute contraindication in children and adolescents due to premature epiphyseal plate closure, stunting of adult stature, and precocious sexual development.
Drug Interactions:
Oral Anticoagulants (e.g., Warfarin, DOACs): Oxymetholone significantly enhances patient sensitivity to oral anticoagulants by inhibiting hepatic clotting factor synthesis and downregulating coagulation pathways. Severe, unpredictable elevations in the International Normalised Ratio (INR) and life-threatening haemorrhagic events can occur, requiring extreme clinical vigilance and substantial anticoagulant dose reductions.
Oral Hypoglycaemic Agents and Insulin: Anabolic steroids alter peripheral carbohydrate tolerance and increase insulin sensitivity; co-administration with metformin, sulfonylureas, or exogenous insulin can precipitate severe, unpredictable hypoglycaemic episodes, requiring close blood glucose monitoring.
Hepatotoxic Medications (e.g., Paracetamol, Methotrexate, Statins, Azole Antifungals): Concurrent use with other hepatotoxic substances exerts additive cytotoxic stress on hepatocytes, multiplying risks of severe drug-induced liver injury (DILI).
Other Anabolic-Androgenic Steroids: Stacking with other oral $17\alpha\text{-alkylated}$ steroids compounds hepatic parenchymal damage and accelerates severe lipid dysregulation.
Clinical Precautions and Harm Minimisation:
Cardiovascular Alarm Symptoms (“Red Flags”): Patients presenting with crushing central chest pressure, acute exertional dyspnoea, sudden unilateral focal neurological deficits (facial droop, speech impairment), or acute unilateral lower limb swelling require immediate emergency (999/A&E) transfer.
Hepatic Alarm Signs: Emergence of clinical scleral or cutaneous jaundice, dark brown urine, pale acholic stools, persistent right upper quadrant pain, or intractable pruritus indicates acute cholestasis or severe hepatic injury, necessitating immediate drug cessation and urgent specialist hepatological admission.
Structured Diagnostic Workup for Illicit AAS Users: Clinicians encountering individuals actively using or discontinuing oxymetholone should perform a comprehensive risk assessment: 12-lead ECG, blood pressure evaluation, full blood count (monitoring haematocrit), comprehensive lipid profile (total cholesterol, HDL-C, LDL-C, triglycerides), liver function tests (ALT, AST, ALP, GGT, bilirubin), renal function tests (urea, creatinine, eGFR), and an early-morning endocrine panel (total testosterone, SHBG, LH, FSH, oestradiol).
Clinical Cessation Support: Clinicians should counsel patients directly and objectively on the systemic toxicities of unregulated UGL oral steroids, support structured drug cessation, and coordinate endocrine referral for the diagnosis and management of prolonged post-AAS hypogonadotrophic hypogonadism where clinically indicated.




 English English
 German
 Italian
 Dutch
 Spanish


Reseñas
Todavía no hay reseñas.