- Tu carrito está vacío
- Continuar comprando


£ 133.20
Comprehensive UK clinical and toxicological monograph on oxandrolone detailing synthetic $17\alpha$-alkylated anabolic-androgenic steroid (AAS) pharmacology, androgen receptor signal transduction, severe hepatic and cardiovascular toxicity risks, UK Class C / Schedule 4 controlled drug status, and therapeutic scope.
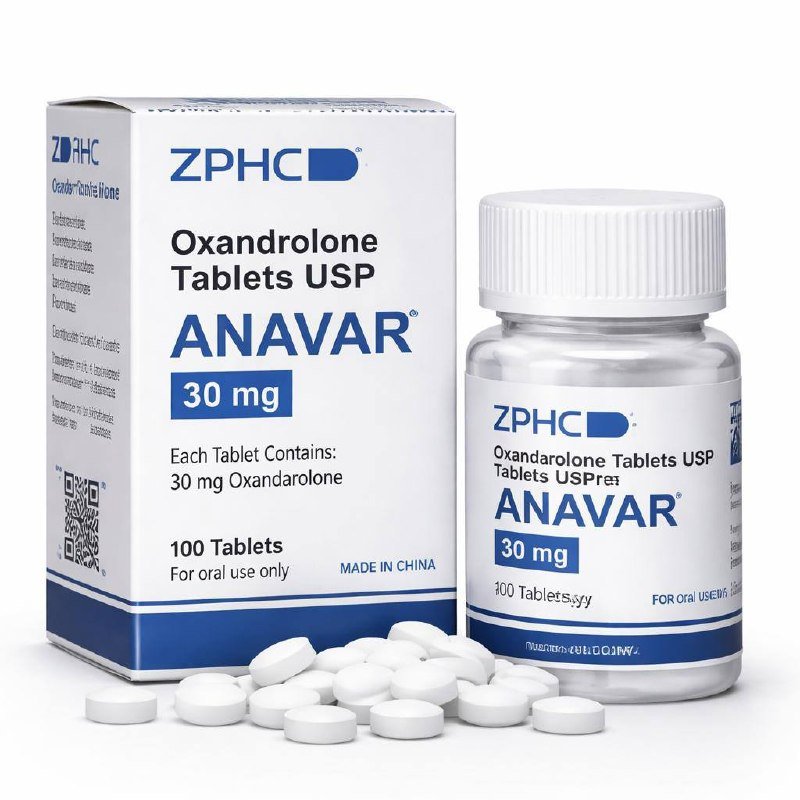
Oxandrolone is an orally active, synthetic anabolic-androgenic steroid (AAS) originally developed by G.D. Searle & Company in the 1960s and marketed internationally under proprietary trade names including Oxandrina y Anavar (alongside extensive multi-source generic and illicit underground laboratory formulations). Chemically designated as $(4aR,4bS,6aS,7S,9aS,9bR,11aS)\text{-7-hydroxy-4a,6a-dimethylhexadecahydro-1H-cyclopenta[7,8]phenanthro[2,3-c]furan-3-one}$ (or $17\beta\text{-hydroxy-17}\alpha\text{-methyl-2-oxa-5}\alpha\text{-androstan-3-one}$), oxandrolone is a structural derivative of dihydrotestosterone (DHT). Structurally, it features two distinct molecular modifications to the core cyclopentanoperhydrophenanthrene steroidal nucleus:
The 2-Oxa Modification: The carbon-2 methylene group within the A-ring is replaced with an oxygen atom (heterocyclic substitution), which significantly amplifies metabolic stability, prevents aromatization into estrogens, and enhances myotrophic (anabolic) potency relative to androgenic potency.
$17\alpha$-Alkylation: A methyl substitution at the carbon-17 position ($17\alpha\text{-methyl}$) creates steric hindrance that protects the $17\beta$-hydroxyl group from rapid Phase I hepatic oxidation into an inactive 17-ketosteroid during first-pass transit, conferring high oral bioavailability.
Its empirical molecular formula is $\text{C}_{19}\text{H}_{30}\text{O}_3$, with an average molecular weight of $306.44\text{ g/mol}$.
Standard solid oral presentations of oxandrolone historically authorized or encountered in specialist settings include:
Immediate-Release Compressed Tablets: Standardized single-agent strengths of $2.5\text{ mg}$ y $10\text{ mg}$ (and up to $20\text{ mg}$ in select foreign commercial or compounding formulations), typically presented as white or pale off-white scored tablets. Common excipients include lactose monohydrate, maize starch, magnesium stearate, and hydroxypropyl methylcellulose (hypromellose).
Within the United Kingdom and international regulatory frameworks:
Medicinal Classification (UK): Oxandrolone is categorized as a Prescription Only Medicine (POM) under the Human Medicines Regulations 2012.
Formulary Availability: It is not routinely marketed in the UK as a primary NHS brand (following discontinuations of commercial authorizations in various European territories), but it remains accessible via authorized hospital specialist prescribing, tertiary endocrine/burns multidisciplinary teams, and licensed MHRA Section 10 “specials” importation frameworks.
Controlled Drug Scheduling: Under the Misuse of Drugs Act 1971, oxandrolone is scheduled as a Class C controlled substance (anabolic steroid). Under the Misuse of Drugs Regulations 2001, it is placed in Schedule 4 (Part 2 / CD Anab POM). Prescriptions are valid for up to 28 days from signing; it is exempt from statutory Safe Custody register-logging requirements in registered retail pharmacies. Under UK law, possession for personal use without a prescription is generally not an offense if transported personally as a medicinal product, but unauthorized supply, production, importation via postal/courier services, and intent to supply are criminal offenses carrying severe custodial penalties.
Anti-Doping Status: Explicitly prohibited at all times (in-competition and out-of-competition) under Category S1 (Anabolic Agents) of the World Anti-Doping Agency (WADA) Prohibited List.
Illicit Diversion and Counterfeits: Due to its reputation in bodybuilding and athletic subcultures as a “mild,” non-aromatizing AAS with low water retention (often referred to as “Var”), oxandrolone is one of the most widely counterfeited oral steroids. Illicit underground laboratory (UGL) preparations frequently contain cheaper, significantly more hepatotoxic alternatives—such as methandienone (Dianabol), stanozolol, or methyltestosterone—or inert fillers, presenting severe toxicological hazards.
The pharmacodynamic profile of oxandrolone is characterized by high-affinity binding to intracellular androgen receptors, promoting potent skeletal muscle anabolism with relatively attenuated androgenic activity:
Androgen Receptor (AR) Binding and Genomic Signalling:
Oxandrolone crosses the plasma membrane of target cells via passive diffusion and binds with high stereospecific affinity to cytoplasmic androgen receptors (AR).
Ligand binding induces a conformational change that triggers the dissociation of heat shock proteins (Hsp90, Hsp70). The ligand-receptor complex homodimerizes and translocates into the nucleus.
Inside the nucleus, the complex binds to specific DNA sequences known as androgen response elements (AREs) located within the promoter regions of target genes.
In concert with tissue-specific co-activators, it upregulates the transcription of messenger RNA (mRNA) encoding structural contractile proteins (actin, myosin) and anabolic enzymes, while downregulating catabolic signaling pathways (inhibiting the ubiquitin-proteasome pathway and antagonizing the catabolic effects of endogenous glucocorticoids/cortisol).
Anabolic vs. Androgenic Dissociation:
Unlike testosterone, which undergoes irreversible $5\alpha$-reduction by $5\alpha\text{-reductase}$ to the more potent androgen dihydrotestosterone (DHT) in target tissues like the prostate, skin, and scalp, oxandrolone is already a $5\alpha\text{-reduced}$ DHT derivative and cannot be further $5\alpha\text{-reduced}$.
Consequently, its potency is not amplified in androgen-sensitive tissues (prostate, hair follicles), giving it a significantly favorable myotrophic-to-androgenic (anabolic:androgenic) ratio—experimentally rated up to $10:1\text{ to }13:1$ relative to methyltestosterone (which is calibrated as $1:1$).
Non-Aromatizability:
The substitution of the carbon-2 atom with an oxygen atom renders the A-ring structurally incompatible with the cytochrome P450 aromatase (CYP19A1) enzyme complex.
Oxandrolona cannot be converted into estradiol or any other estrogen. As a result, it does not induce estrogen-dependent adverse effects such as fluid retention, subcutaneous edema, or true estrogenic gynecomastia.
Nitrogen Retention and Muscle Hypertrophy:
Oxandrolone significantly enhances systemic nitrogen retention, stimulates muscular amino acid uptake, and promotes intracellular creatine phosphate synthesis (enhancing cellular adenosine triphosphate [ATP] regeneration).
It stimulates the local expression of skeletal muscle insulin-like growth factor 1 (IGF-1) and activates myogenic satellite cells, accelerating muscle repair and lean tissue accretion.
Hypothalamic-Pituitary-Gonadal (HPG) Axis Suppression:
Despite its attenuated androgenicity, systemic oxandrolone exerts negative feedback on the hypothalamus and anterior pituitary gland, suppressing the pulsatile secretion of gonadotropin-releasing hormone (GnRH), luteinizing hormone (LH), y follicle-stimulating hormone (FSH). This leads to rapid downregulation of endogenous intratesticular testosterone synthesis and impaired spermatogenesis.
In authorized clinical practice (under international labels like the US FDA and specialized UK/European hospital protocols), oxandrolone is reserved strictly for severe catabolic or developmental states:
Adjunctive Therapy for Pathological Weight Loss and Catabolism:
Indicated as adjunctive therapy to promote weight gain after extensive weight loss following severe trauma, major surgical interventions, chronic serious infections, or unresolving catabolic states.
Counteracting protein catabolism associated with prolonged administration of systemic corticosteroids.
Relief of bone pain accompanying established osteoporosis.
Standard Adult Dosing: $2.5\text{ mg}$ to $20\text{ mg}$ orally daily, administered in 2 to 4 divided doses. A typical therapeutic starting regimen in adults is $5\text{ to }10\text{ mg/day}$, rarely exceeding $20\text{ mg/day}$.
Duration: Recommended for short, interrupted courses of 2 to 4 weeks (rarely up to 3 months under strict hepatic and lipid monitoring).
Severe Burn Injury Recovery (Specialist Tertiary Protocol):
Widely recognized in tertiary burn units for blunting the extreme hypermetabolic and hypercatabolic state in pediatric and adult patients with severe burns ($>30\%\text{ total body surface area}$).
Clinical trials demonstrate that oxandrolone accelerates donor site healing, preserves lean body mass, and shortens hospital stays:
Pediatric Burns Dosing: $0.1\text{ mg/kg}$ orally twice daily.
Turner Syndrome (Adolescent Growth Promotion):
Prescribed off-label under specialized pediatric endocrine supervision in girls with Turner syndrome (karyotype 45,X0) who exhibit severe short stature, often combined with recombinant human growth hormone (rhGH) to optimize final adult height without inducing premature epiphyseal closure or excessive virilization.
Pediatric Dosing: Extremely low doses, typically $0.03\text{ to }0.05\text{ mg/kg/day}$.
Constitutional Delay of Growth and Puberty:
Short-term use in adolescent males with documented constitutional growth delay to stimulate growth velocity without compromising final adult height.
In illicit, non-medical athletic and bodybuilding settings:
Misused at supratherapeutic doses ($40\text{ to }100+\text{ mg/day}$) in “cutting” cycles to maintain lean muscle mass while operating in severe caloric deficits, enhance strength without adding extracellular water, and accelerate athletic recovery.
Heavily abused by female athletes and bodybuilders due to its lower rate of virilizing effects compared to other AAS, although virilization remains a serious risk at non-therapeutic dosages.
The pharmacokinetic behavior of oxandrolone is characterized by high oral bioavailability, modest protein binding, resistance to Phase I hepatic breakdown, and substantial renal excretion:
| Pharmacokinetic Parameter | Value / Metric | Clinical Interpretation |
| Oral Bioavailability | $>95\%$ (High) | Near-complete absorption; $17\alpha$-alkylation resists first-pass hepatic clearance. |
| Time to Peak Concentration ($T_{max}$) | $1.0\text{ to }1.5\text{ hours}$ | Rapid gastrointestinal absorption; quick onset of systemic circulation. |
| Volume of Distribution ($V_d$) | $\sim 0.5\text{ to }0.8\text{ L/kg}$ | Low-to-moderate distribution; largely confined to vascular and muscular compartments. |
| Plasma Protein Binding | $\sim 94\text{ to }97\%$ | Bound primarily to human serum albumin; low affinity for SHBG. |
| Hepatic Metabolism | Moderate (Unique for an AAS) | Unusually resistant to liver biotransformation compared to other $17\alpha$-alkylated steroids. |
| Active Metabolites | 17-epioxandrolone (weak) | Parent oxandrolone drives the vast majority of biological activity. |
| Elimination Route | Renal ($60\%$), Fecal/Biliary ($30\%$) | Uniquely high urinary excretion of unchanged parent compound ($\sim 28\text{–}30\%$). |
| Elimination Half-Life ($t_{1/2}$) | Biphasic: Initial $\sim 0.5\text{ h}$, terminal $9.4\text{ to }10.5\text{ hours}$ (Adults) | Requires twice-daily split dosing to maintain stable plasma concentrations. |
Resistance to Hepatic Degradation: While the $17\alpha\text{-methyl}$ group protects the molecule from conversion to 17-ketosteroids, the 2-oxa modification further reduces the rate of hepatic microsomal oxidation. Consequently, oxandrolone is cleared much more slowly by the liver than testosterone or methyltestosterone.
Metabolite Profile: The small portion that undergoes Phase I metabolism produces 17-epioxandrolone (via epimerization) and oxidized hydroxylated derivatives, which undergo subsequent Phase II glucuronidation.
Renal Excretion: A defining feature of oxandrolone is that approximately $28\text{ to }30\%$ of an oral dose is excreted entirely unchanged in the urine. This high renal clearance rate places significant filtration demands on the kidneys during high-dose exposure.
SHBG Interactions: Oxandrolone exhibits low binding affinity for sex hormone-binding globulin (SHBG). Furthermore, systemic administration suppresses hepatic synthesis of SHBG by up to $80\text{ to }90\%$, markedly increasing the circulating free, unbound fraction of other co-administered steroids or endogenous hormones.
Therapeutic administration preserves nitrogen balance, accelerates wound repair, and builds skeletal muscle. However, non-physiological exposure, prolonged use, or high-dose illicit administration produces multi-system toxicities:
Hepatotoxicity ($17\alpha$-Alkylated Steroid Class Toxicity):
Todos $17\alpha$-alkylated oral steroids place metabolic strain on hepatocytes. Although oxandrolone is clinically considered less hepatotoxic than methyltestosterone, fluoxymesterone, or stanozolol at equivalent milligram doses, it carries substantial hepatotoxic risks:
Asymptomatic elevations in serum aminotransferases (ALT, AST) and alkaline phosphatase (ALP).
Intrahepatic Cholestasis: Direct impairment of canalicular bile export pumps (BSEP) leads to biliary stasis, manifested as pruritus, dark urine, pale stools, and jaundice.
Peliosis Hepatis: A life-threatening condition characterized by the formation of blood-filled, cystic cavities throughout the hepatic parenchyma. These cysts can rupture spontaneously or following minor abdominal trauma, leading to catastrophic hemoperitoneum, intra-abdominal exsanguination, and shock.
Hepatic Neoplasia: Long-term exposure is associated with benign hepatic adenomas and malignant hepatocellular carcinoma (HCC).
Cardiovascular and Atherogenic Dysregulation:
Severe Atherogenic Dyslipidemia: Oxandrolone stimulates hepatic triglyceride lipase (HTGL), driving profound shifts in circulating lipoproteins:
Marked suppression of high-density lipoprotein cholesterol (HDL-C), frequently dropping baseline levels by $50\text{ to }80\%$ (often down to single digits, $<0.3\text{ mmol/L}$ / $<10\text{ mg/dL}$).
Concurrent elevation of low-density lipoprotein cholesterol (LDL-C) and apolipoprotein B.
Arterial hypertension: Driven by vascular endothelial dysfunction, blunted nitric oxide production, and increased vascular tone.
Left Ventricular Hypertrophy (LVH): Direct androgenic stimulation of myocardial ARs leads to concentric left ventricular remodeling, diastolic dysfunction, myocardial fibrosis, and elevated risks of premature myocardial infarction, heart failure, and sudden cardiac death.
Endocrine and Reproductive Dysregulation:
Hypogonadism: Suppression of LH and FSH causes severe primary/secondary testicular atrophy, oligospermia or azoospermia, and secondary erectile dysfunction upon drug cessation. Recovery of the endogenous HPG axis can take months to years, often necessitating medical intervention.
Virilization in Females (Irreversible Class Effect): In women, supra-physiological doses induce permanent masculinizing changes:
Deepening of the vocal pitch (dysphonia, vocal cord thickening).
Irreversible clitoral enlargement (clitoromegaly).
Hirsutism (male-pattern facial and body hair growth) and androgenic alopecia (temporal hairline recession).
Menstrual irregularities, amenorrhea, and anovulatory infertility.
Pediatric Hazards: Premature closure of the epiphyseal growth plates in long bones (via peripheral conversion of residual androgens to estrogens, or direct local actions), permanently arresting linear longitudinal growth and resulting in adult short stature.
Psychiatric and Neurobehavioral Disturbances:
Mood swings, hypomania, irritability, increased aggressive outbursts (“steroid rage”), sleep disturbances, and acute paranoia.
Dependence syndrome: Characterized by muscle dysmorphia (bigorexia), tolerance, and profound depressive withdrawal states following cessation.
Prescribing, monitoring, or clinically managing individuals exposed to oxandrolone requires strict adherence to oncological exclusions, metabolic interaction screening, and multi-organ surveillance:
Contraindications:
Known or Suspected Carcinoma of the Prostate or Male Breast: Absolute Contraindication. Androgen receptor agonism accelerates the proliferation of hormone-dependent malignant cells.
Carcinoma of the Breast in Females with Hypercalcemia: Androgens stimulate osteolytic resorption, dangerously escalating serum calcium.
Severe Hepatic Impairment / Active Liver Disease: Absolute contraindication due to impaired drug clearance, exacerbation of cholestasis, and risk of hepatic failure or peliosis hepatis.
Nephrosis or the Nephrotic Phase of Nephritis: Contraindicated due to fluid retention and protein wasting complications.
Pregnancy and Breastfeeding: Absolute Contraindication. Teratogenic; causes severe virilization and pseudohermaphroditism in female fetuses (labioscrotal fusion, phallic enlargement); unknown whether metabolites pass into breast milk, but contraindicated due to adverse infant effects.
Hypercalcemia: Contraindicated in patients with active hypercalcemia.
Drug Interactions:
Oral Anticoagulants (Warfarin, Phenprocoumon): Highest-Tier Clinical Hazard. Oxandrolone dramatically enhances the anticoagulant sensitivity of vitamin K antagonists, likely by altering the hepatic synthesis of clotting factors and increasing receptor affinity. Co-administration can cause drastic, unexpected spikes in prothrombin time / INR, leading to severe, life-threatening hemorrhages.
Management: The dose of warfarin must be reduced by $50\text{ to }75\%$ upon initiation of oxandrolone, accompanied by daily or every-other-day INR monitoring.
Oral Hypoglycemic Agents and Insulin: Anabolic steroids enhance glucose tolerance and increase peripheral insulin sensitivity. Diabetic patients receiving antidiabetic therapies require close blood glucose monitoring and frequent downward dosage adjustments of insulin or sulfonylureas to prevent severe hypoglycemia.
Hepatotoxic Medications (e.g., Acetaminophen/Paracetamol in high doses, Statins, Azole Antifungals, Methotrexate): Compounded metabolic burden on hepatocytes, significantly escalating the risk of severe drug-induced liver injury (DILI) and cholestasis.
Adrenocorticosteroids (Corticosteroids, ACTH): Concomitant use can exacerbate peripheral edema and increase the incidence of acneiform eruptions.
Clinical Precautions and Surveillance Protocols:
Mandatory Laboratory Surveillance: Patients undergoing authorized therapeutic treatment (or monitored in harm-reduction clinical settings) require comprehensive baseline and periodic laboratory testing every 4 to 8 weeks:
Liver Function Tests (LFTs): Baseline and monthly serum ALT, AST, total bilirubin, and alkaline phosphatase. Sustained elevations $>3\text{-fold}$ above the upper limit of normal mandate immediate drug cessation.
Fasting Lipid Profile: Baseline and periodic monitoring of total cholesterol, HDL-C, LDL-C, and triglycerides.
Full Blood Count (FBC): Monitoring hematocrit and hemoglobin; androgens stimulate erythropoietin secretion, presenting liabilities for secondary polycythemia (hematocrit $>52\text{–}54\%$ significantly elevates thromboembolic and stroke risks).
Renal Function Tests: Serum creatinine, urea, and electrolytes, particularly given high unchanged renal excretion.
Hepatic Imaging: Periodic hepatic ultrasonography should be performed in prolonged therapy ($>3\text{ months}$) to screen for the development of peliosis hepatis or occult adenomas.
Pediatric Monitoring: In children and adolescents, radiological bone age assessments (left wrist/hand radiography) must be performed every 6 months to evaluate the rate of epiphyseal maturation against chronological height velocity to prevent premature growth plate fusion.
Harm-Reduction / Post-Cessation Support: Clinicians encountering individuals discontinuing illicit high-dose oxandrolone should anticipate severe secondary hypogonadotrophic hypogonadism. Clinical support focuses on cardiovascular risk management (lipid normalization), hepatic recovery monitoring, psychological support for depressive crashes, and, where clinically indicated by an endocrinologist, structured protocols to stimulate endogenous pituitary gonadotropin recovery.


 English English
 German
 Italian
 Dutch
 Spanish