- Tu carrito está vacío
- Continuar comprando


£ 59.20
Comprehensive UK clinical and regulatory monograph on Pregabalin 50mg detailing voltage-gated calcium channel $\alpha_2\delta$ ligand neuropharmacology, central excitatory neurotransmitter suppression, renal excretion kinetics, abuse and dependence liabilities, and Class C / Schedule 3 controlled drug status.
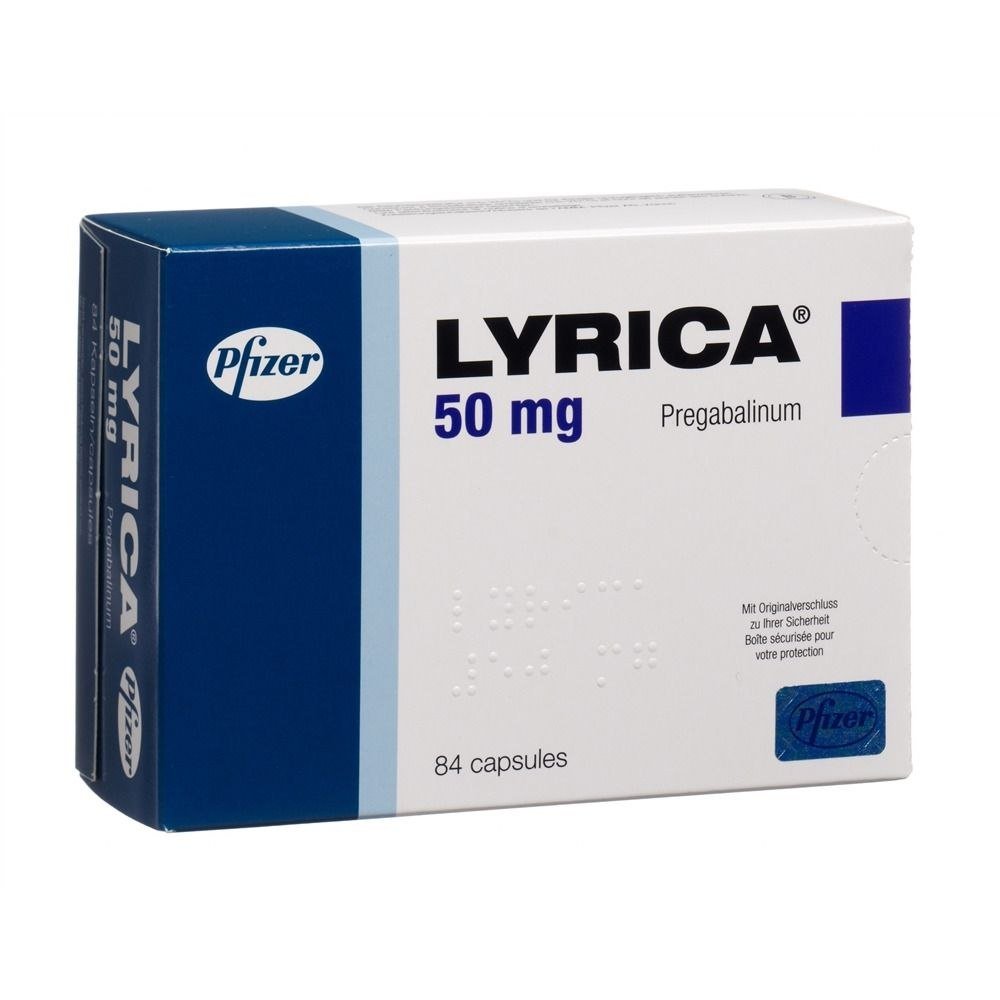
Pregabalin 50mg is a licensed branded and generic oral pharmaceutical preparation (originally developed and commercialized under the innovator trade name Lyrica by Pfizer). Chemically designated as $(3S)\text{-3-(aminomethyl)-5-methylhexanoic acid}$, pregabalin is a synthetic branched-chain aliphatic carboxylic acid belonging to the gabapentinoid chemical class. Structurally, it is an alkylated analogue of the primary inhibitory neurotransmitter $\gamma\text{-aminobutyric acid}$ (GABA), specifically characterized by an isobutyl substitution at the carbon-3 ($\beta$) position. It is synthesized and marketed exclusively as the biologically active single $(S)\text{-enantiomer}$. Its empirical molecular formula is $\text{C}_8\text{H}_{17}\text{NO}_2$, with an average molecular weight of $159.23\text{ g/mol}$.
Standard solid oral presentations of Pregabalin 50mg in the United Kingdom appear as hard gelatin capsules featuring a white body and white cap (imprinted with black ink indicating brand/strength identifiers such as “PG 50” or “Pfizer PGN 50”). Capsules are filled with white to off-white crystalline powder compounded with non-active pharmaceutical excipients, including lactose monohydrate, pregelatinized maize starch, and talc, encapsulated in a shell containing gelatin and titanium dioxide (E171).
Within the United Kingdom regulatory framework:
Medicinal Classification: Pregabalin is categorized as a Prescription Only Medicine (POM) governed by the Human Medicines Regulations 2012. It is catalogued in the British National Formulary (BNF) and listed on the NHS Drug Tariff, reimbursable across NHS primary and secondary care prescription pathways (FP10).
Controlled Drug Rescheduling: Following extensive public health reviews, clinical toxicology reports, and formal advice from the Advisory Council on the Misuse of Drugs (ACMD) highlighting rising mortality, diversion, and recreational abuse, pregabalin was officially reclassified in April 2019 as a Class C controlled substance under the Misuse of Drugs Act 1971 and placed into Schedule 3 (CD No Register POM) under the Misuse of Drugs Regulations 2001.
Statutory Prescription Writing Mandates: As a Schedule 3 Controlled Drug:
Prescriptions are legally valid for only 28 days from the date of signing.
Prescriptions must comply with strict statutory Controlled Drug requirements (exact form, strength, dose, and total quantity written in both words and figures).
Routine repeat dispensing is prohibited. It is exempt from safe custody requirements in registered community pharmacies.
In clinical toxicology and community addiction monitoring, diverted pharmaceutical or counterfeit “Pregabalin 50mg” (often dubbed “Buds”, “Pregabs”, or “Signature” on illicit markets) represents a growing hazard. Counterfeit preparations sourced online or via street diversion frequently exhibit variable API concentrations or carry adulteration with novel designer benzodiazepines (e.g., bromazolam) or potent synthetic opioids (such as nitazenes).
Despite being a structural structural derivative of GABA, pregabalin displays no direct activity at $GABA_A$, $GABA_B$, or benzodiazepine recognition sites. It is neither metabolized into GABA nor does it directly inhibit GABA transaminase or alter physiological GABA uptake:
High-Affinity Binding to Voltage-Gated Calcium Channel $\alpha_2\delta$ Subunits:
Pregabalin exerts its clinical pharmacodynamics by binding with high stereospecific affinity to the auxiliary $\alpha_2\delta\text{-1}$ y $\alpha_2\delta\text{-2}$ protein subunits of presynaptic voltage-gated calcium channels (VGCCs) located throughout the neocortex, amygdala, hippocampus, and the superficial dorsal horn of the spinal cord.
Binding affinity ($K_d \approx 30\text{ to }40\text{ nM}$) is approximately six times higher than that of gabapentin, conferring its higher clinical milligram potency.
Presynaptic Calcium Influx Blunting and Neurotransmitter Modulation:
In hyper-excited or pathologically sensitized neuronal circuits (such as damaged peripheral nociceptors in neuropathic pain or hyper-reactive limbic networks in generalized anxiety), presynaptic VGCC density is significantly upregulated.
Occupancy of the $\alpha_2\delta$ subunit by pregabalin reduces depolarisation-induced calcium ($Ca^{2+}$) influx through the presynaptic terminal.
Decreased intracellular calcium influx suppresses the vesicular exocytosis and synaptic release of key excitatory neurotransmitters, notably L-glutamate, substance P, calcitonin gene-related peptide (CGRP), and noradrenaline.
Normalization of Hyperexcitable Networks:
By dampening excessive excitatory neurotransmission without directly interrupting basal physiological synaptic signaling, pregabalin produces targeted analgesia, anticonvulsant activity, and anxiolysis.
Secondary Modulatory Mechanisms:
Chronic administration modulates the forward trafficking of functional calcium channels from the endoplasmic reticulum to the presynaptic terminal membrane.
Electrophysiological studies suggest secondary enhancement of non-vesicular GABA transport density in specific central pathways over sustained exposure.
Receptor Non-Interactions: Pregabalin exhibits no direct affinity for human opioid ($\mu$, $\kappa$, $\delta$), cannabinoid, dopamine, or serotonin receptors, and does not alter systemic arterial sodium or potassium channel conductances.
Pregabalin 50mg holds licensed multi-system clinical indications within the British National Formulary (BNF) and National Institute for Health and Care Excellence (NICE) clinical guidelines:
Peripheral and Central Neuropathic Pain (Licensed UK Indication):
Indicated for the management of chronic peripheral neuropathic pain (e.g., painful diabetic peripheral neuropathy, post-herpetic neuralgia) and central neuropathic pain (e.g., post-stroke pain, spinal cord injury pain).
Evaluated within NICE Guideline CG173 (Neuropathic pain in adults), which recommends pregabalin as a first-line pharmacological option alongside amitriptyline, duloxetine, and gabapentin.
Standard Neuropathic Pain Dosing: Initiated at $150\text{ mg/day}$ administered in two or three divided doses (e.g., $50\text{ mg}$ TDS or $75\text{ mg}$ BD). Depending on individual clinical efficacy and tolerability, the dose may be titrated after 3 to 7 days to $300\text{ mg/day}$, and up to a maximum ceiling of $600\text{ mg/day}$ after an additional 7-day interval.
Epilepsy (Adjunctive Therapy for Focal Seizures):
Indicated as adjunctive therapy in adults with focal (partial) seizures, with or without secondary generalization.
Evaluated under NICE Guideline NG217 (Epilepsies in children, young people and adults). Dosing aligns with neuropathic schedules, starting at $150\text{ mg/day}$ in divided doses and titrating systematically up to $600\text{ mg/day}$.
Generalized Anxiety Disorder (GAD):
Indicated for the treatment of Generalized Anxiety Disorder in adults.
Evaluated within NICE Guideline CG113 (Anxiety disorders), where pregabalin is positioned as a valuable option for patients refractory to, or intolerant of, first-line selective serotonin reuptake inhibitors (SSRIs) or serotonin-noradrenaline reuptake inhibitors (SNRIs). Initial dose: $150\text{ mg/day}$ divided into two or three administrations, titrating incrementally up to $300\text{ to }600\text{ mg/day}$.
Fibromyalgia (Off-Label UK Practice):
Widely utilized off-label in secondary care rheumatology and chronic pain clinics for widespread musculoskeletal pain, central sensitization, and sleep fragmentation ($150\text{ to }450\text{ mg/day}$).
In non-authorized and illicit settings, Pregabalin 50mg is heavily sought after for:
Recreational Intoxication: Producing an initial dissociative, empathogenic, euphoric, and disinhibited state colloquially described as a hybrid of drunkenness and MDMA-like warmth.
Opioid Withdrawal Self-Management: Ingested in supratherapeutic doses ($600\text{ to }1,500+\text{ mg}$) by individuals with opioid use disorder (OUD) to blunt the noradrenergic autonomic storms, gastrointestinal cramping, and restlessness of opioid abstinence.
Polydrug Stacking: Co-administered alongside illicit opioids (heroin, methadone) or benzodiazepines to potentiate euphoric sedation.
The pharmacokinetic disposition of pregabalin is defined by rapid, extensive oral absorption via active transport, an absence of meaningful hepatic metabolism, and near-exclusive renal clearance:
Absorption: Following oral administration in a fasted state, pregabalin is absorbed rapidly across the upper gastrointestinal tract. Peak plasma concentrations ($C_{max}$) are achieved within 1 hour (median $T_{max} \approx 0.7\text{ to }1.3\text{ hours}$). Absolute oral bioavailability is high and dose-independent, consistently exceeding $\ge 90\%$ across its entire therapeutic range ($75\text{ to }600\text{ mg/day}$).
Transporter Dependency: Gastrointestinal uptake is mediated by the saturable system L-neutral amino acid transporter (LAT1 / SLC7A5). Unlike gabapentin—which displays highly non-linear, saturable absorption that causes bioavailability to drop precipitously at higher doses—pregabalin displays linear, dose-proportional pharmacokinetics across the entire clinical range.
Food Interactions: Co-ingestion with food decreases $C_{max}$ by approximately $25\text{ to }30\%$ and delays $T_{max}$ to approximately 2.5 hours, but does not alter the total extent of absorption ($AUC$). It may be taken with or without food.
Distribution: Pregabalin is a hydrophilic molecule ($\text{LogP} \approx -1.35$) that crosses the blood-brain barrier via LAT1-mediated active transport. It exhibits an apparent volume of distribution ($V_d$) of approximately $0.56\text{ L/kg}$. In circulating human plasma, pregabalin displays zero plasma protein binding ($0\%$ bound). It crosses the placental boundary and is excreted into maternal breast milk.
Biotransformation (Negligible Hepatic Metabolism): Pregabalin undergoes negligible biotransformation in humans:
Approximately $98\%$ of the absorbed dose remains unchanged.
The only minor metabolite identified in human urine is the $N\text{-methylated}$ derivative of pregabalin, which accounts for less than $1\%$ of the total dose.
It does not induce or inhibit cytochrome P450 enzymes (CYP1A2, CYP2A6, CYP2C9, CYP2C19, CYP2D6, CYP2E1, or CYP3A4), conferring a very low profile for CYP-mediated pharmacokinetic drug-drug interactions.
Elimination: Systemic elimination occurs almost exclusively via renal clearance through glomerular filtration and secondary tubular handling:
Approximately $98\%$ of an administered dose is excreted unchanged in the urine.
Renal clearance ($CL_r \approx 67\text{ to }81\text{ mL/min}$) is directly proportional to creatinine clearance ($\text{CrCl}$).
The mean terminal elimination plasma half-life ($t_{1/2}$) in healthy adults with normal renal function is $5.5\text{ to }6.7\text{ hours}$ (mean $\sim 6.3\text{ hours}$).
Renal Impairment Kinetics: In patients with impaired renal function, elimination half-life is substantially prolonged (exceeding $14\text{ to }20+\text{ hours}$ in moderate-to-severe CKD), mandating strict dosage adjustments based on calculated creatinine clearance to prevent neurotoxic accumulation. Pregabalin is cleared effectively by hemodialysis (a standard 4-hour hemodialysis session clears $\sim 50\%$ of circulating drug).
The primary physiological effect in authorized clinical practice is a reduction in neuropathic hypersensitivity, stabilization of seizure activity, and dampening of autonomic anxiety. However, central $\alpha_2\delta$ modulation generates a broad adverse event spectrum:
Central Nervous System and Neuropsychiatric Toxicity (Very Common, $\ge 1/10$):
Dizziness and Somnolence: The most common adverse effects, occurring in over $25\text{ to }35\%$ of patients. Typically dose-dependent, manifesting early during titration and often subsiding over several weeks.
Euphoric Mood: Occurs in $1\text{ to }10\%$ of clinical trial participants, contributing to its intrinsic abuse liability.
Cognitive Clouding: Attention deficits, confusion, psychomotor slowing, memory impairment, and speech disorders (dysarthria).
Incoordination and Balance Disorders: Cerebellar-type ataxia, gait abnormalities, and tremors, substantially elevating the risk of accidental falls and fractures in elderly populations.
Visual and Sensory Disturbances (Common, $1/100$ to $<1/10$):
Blurred vision, diplopia (double vision), and visual field defects (mediated by central visual pathway modulation).
Vertigo and tinnitus.
Metabolic and Fluid Disturbances (Common):
Peripheral Oedema and Fluid Retention: Dose-dependent fluid accumulation presenting as bilateral lower-extremity pitting oedema (incidence $5\text{ to }15\%$). Driven by downstream vascular and renal microvascular tone shifts.
Significant Weight Gain: Driven by increased appetite (hyperphagia) combined with fluid retention; long-term treatment can induce substantial metabolic weight gain ($>7\%$ baseline increase in up to $15\%$ of patients).
Exacerbation of Congestive Heart Failure: Fluid retention can precipitate acute decompensation in patients with baseline NYHA Class III–IV chronic heart failure.
Severe, Emergent and Life-Threatening Hazards (Critical Safety Alerts):
Fatal Synergistic Respiratory Depression (MHRA Drug Safety Alert): While isolated oral pregabalin overdose rarely causes fatal central apnea, co-administration with other central nervous system depressants (principally opioids, benzodiazepines, or alcohol) is lethal. Pregabalin blunts the hypoxic ventilatory response and magnifies opioid-induced medullary respiratory depression, dramatically increasing fatal overdose rates in polysubstance users.
Severe Physical Dependence and Acute Withdrawal Syndrome: Abrupt cessation following as few as 2 to 4 weeks of continuous use triggers a severe withdrawal toxidrome:
Intense rebound insomnia, severe agitation, panic attacks, and profuse diaphoresis.
Gastrointestinal distress: nausea, vomiting, abdominal cramping, and severe diarrhea.
Neuromuscular hyperactivity: fine and coarse tremors, myoclonus, autonomic instability (sinus tachycardia, hypertension).
Withdrawal Seizures: Sudden discontinuation can precipitate status epilepticus, even in patients who were taking pregabalin for anxiety or pain without any prior history of epilepsy.
Suicidal Ideation and Behavior (MHRA / BNF Warning): A recognized class effect of antiepileptic and gabapentinoid drugs; patients and caregivers must be counseled to monitor for treatment-emergent depression, mood alterations, or emergent suicidal ideation.
Severe Cutaneous and Immunological Toxicities: Angioedema involving the tongue, glottis, larynx, and lips, risking acute upper airway obstruction; Stevens-Johnson syndrome (rare).
Myopathy and Rhabdomyolysis: Unexplained muscle pain, tenderness, or weakness accompanied by marked creatine kinase (CK) elevations.
Prescribing, dispensing, and reviewing individuals exposed to Pregabalin 50mg requires adherence to renal dosing protocols, controlled drug surveillance, and respiratory risk stratification:
Contraindications:
Hypersensitivity: Known hypersensitivity to pregabalin base or any formulation excipients (including severe lactose intolerance or history of pregabalin-induced angioedema).
Severe Decompensated Heart Failure: Contraindicated or avoided in NYHA Class III–IV congestive heart failure unless benefits clearly outweigh risks.
Pregnancy and Teratogenicity (MHRA Safety Alert): A substantial epidemiological study showed that pregabalin use during the first trimester of pregnancy is associated with a slightly increased risk of major congenital malformations (specifically structural malformations of the nervous system, eyes, face, and heart). Pregabalin must not be used during pregnancy unless clearly necessary, and women of childbearing potential must use effective contraception.
Breastfeeding: Pregabalin is excreted into human breast milk; breastfeeding is not recommended during therapy.
Paediatric Population: Not licensed for use in children and adolescents under 18 years of age due to lack of established safety and efficacy data.
Drug Interactions:
Opioids (e.g., Morphine, Oxycodone, Methadone, Buprenorphine, Fentanyl): Highest-Tier Clinical Hazard. Co-administration exponentially magnifies the risk of fatal central respiratory arrest, profound sedation, coma, and severe constipation/paralytic ileus. Co-prescribing requires rigorous clinical documentation, minimum effective dosing, and close surveillance.
Benzodiazepines (e.g., Diazepam, Alprazolam, Clonazepam) and Alcohol: Additive central depression; marked synergistic impairment of psychomotor performance, cognitive processing, motor coordination, and respiratory drive.
Angiotensin-Converting Enzyme (ACE) Inhibitors (e.g., Ramipril, Lisinopril): Co-administration is associated with an increased incidence of peripheral oedema and angioedema.
Thiazolidinediones (e.g., Pioglitazone): Additive fluid retention and peripheral oedema, increasing the risk of precipitating heart failure.
Clinical Precautions and Harm Minimisation:
Mandatory Renal Dosing Adjustments: Because clearance is directly linked to creatinine clearance, dosage must be individualized according to calculated renal function:
$\text{CrCl} \ge 60\text{ mL/min}$: Standard starting dose $150\text{ mg/day}$ (max $600\text{ mg/day}$ in 2 or 3 divided doses).
$\text{CrCl } 30\text{ to }<60\text{ mL/min}$: Starting dose $75\text{ mg/day}$ (max $300\text{ mg/day}$ in 2 or 3 divided doses).
$\text{CrCl } 15\text{ to }<30\text{ mL/min}$: Starting dose $25\text{ to }50\text{ mg/day}$ (max $150\text{ mg/day}$ in 1 or 2 divided doses).
$\text{CrCl } <15\text{ mL/min}$: Starting dose $25\text{ mg/day}$ (max $75\text{ mg/day}$ as a single daily dose).
Hemodialysis Patients: Administer an additional supplementary dose ($25\text{ to }100\text{ mg}$) immediately following each 4-hour hemodialysis treatment.
Structured Discontinuation Protocols: Pregabalin must never be abruptly discontinued. In accordance with BNF recommendations, when terminating chronic therapy, the dose should be tapered gradually over a minimum of at least 1 week (or weeks-to-months in long-term high-dose dependent individuals, reducing by $50\text{ to }100\text{ mg}$ per week) to prevent withdrawal seizures, acute autonomic storms, and severe psychological rebound.
Driving and Operating Machinery: In accordance with the Road Traffic Act 1988, patients must be warned that pregabalin causes dizziness, visual disturbances, and somnolence. Patients must be explicitly advised not to drive or operate complex machinery until they are fully aware of how the medication affects them.
Acute Overdose Management (“Red Flags”):
Acute pregabalin overdose presents as somnolence, confusion, agitation, myoclonus, speech impairment, seizures, and respiratory depression (especially if co-ingested with opioids):
Airway and Ventilatory Support: Secure a patent airway, administer supplemental oxygen, and provide bag-valve-mask or mechanical ventilation if hypoventilation is present.
Seizure Control: Terminate acute seizures using intravenous benzodiazepines (e.g., IV diazepam $10\text{ mg}$ or lorazepam $2\text{ to }4\text{ mg}$).
Role of Naloxone: If co-ingestion with opioids is documented or suspected, administer intravenous naloxone ($400\text{ mcg}$ to $2\text{ mg}$) immediately to reverse opioid-induced respiratory depression (though naloxone will not reverse isolated pregabalin toxicity).
Extracorporeal Elimination: Because pregabalin is not bound to plasma proteins and has a modest volume of distribution, emergency hemodialysis is highly effective in clearing pregabalin from circulation and should be considered in severe, life-threatening overdoses complicated by acute renal failure.


 English English
 German
 Italian
 Dutch
 Spanish