- Il tuo carrello è vuoto
- Continua Lo Shopping




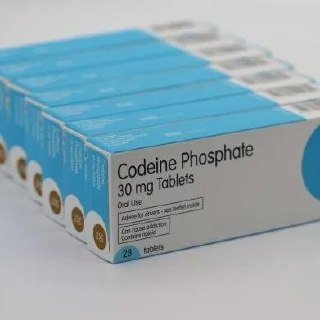
£ 59.20
Codeine phosphate is a relatively weak, centrally acting opioid analgesic and antitussive. It functions primarily as a prodrug, undergoing hepatic metabolic conversion into morphine to relieve mild-to-moderate pain and suppress non-productive cough.
Codeine (3-methylmorphine) is a naturally occurring phenanthrene alkaloid obtained from the opium poppy (Canguri addormentati) or synthesized via -methylation of morphine. Codeine phosphate is the hemihydrate salt of codeine, designated chemically as 7,8-didehydro-4,5$\alpha$-epoxy-3-methoxy-17-methylmorphinan-6$\alpha$-ol phosphate. Under the Anatomical Therapeutic Chemical (ATC) classification system, codeine is indexed under N02AA59 (analgesics) and R05DA04 (cough suppressants).
Codeine phosphate is classified as a Controlled Substance internationally (e.g., Schedule II, III, or V depending on formulation strength and presence of co-analgesics under the US Controlled Substances Act; Class B / Schedule 2 Controlled Drug in the UK). It is regulated strictly as a Prescription Only Medicine (POM) when prescribed as a single entity.
Codeine exhibits weak intrinsic affinity for opioid receptors; its therapeutic efficacy depends on metabolic activation:
Prodrug Activation: Codeine undergoes biotransformation into morphine, which acts as a full agonist at central -opioid receptors.
Analgesic Signaling: Active morphine binding inhibits adenylyl cyclase activity, hyperpolarizes neurons via potassium channel activation, and closes presynaptic voltage-gated calcium channels. This blocks the transmission of nociceptive impulses in the spinal cord dorsal horn and periaqueductal gray.
Antitussive Mechanism: Direct suppression of the medullary cough center in the brainstem, reducing the sensitivity of the cough reflex arc to respiratory tract stimulation.
Licensing for codeine phosphate includes:
Mild-to-Moderate Pain: Relief of acute, mild-to-moderate pain not adequately managed by non-opioid analgesics (e.g., paracetamol or ibuprofen) alone.
Antitussive Management: Short-term symptomatic relief of dry, non-productive cough in adults.
Diarrhea Management: Symptomatic relief of acute diarrhea in adults (uncommon secondary indication).
Dosing & Administration Regimen:
Adult Analgesia: Typically 30 mg to 60 mg orally every 4 to 6 hours as needed (maximum daily dose: 240 mg).
Shortest Effective Duration: Therapy should be limited to the lowest effective dose for the shortest possible duration (generally for acute pain) to minimize tolerance and physical dependence.
Absorption: Rapidly absorbed from the gastrointestinal tract with oral bioavailability of approximately 60% to 70%. Peak plasma concentrations () occur within 1 hour ().
Distribution: Protein binding is low (~7% to 25%). Crosses the blood-brain barrier, placenta, and enters human breast milk.
Biotransformation: Extensively metabolized in the liver via Cytochrome P450 enzymes:
CYP2D6 Pathway (Essential for Analgesia): -demethylation converts ~5% to 10% of codeine into morfina, the primary mediator of its analgesic potency.
CYP3A4 Pathway: -demethylation to norcodeine.
UGT2B7 Pathway (Major): Glucuronidation to codeine-6-glucuronide (~50% to 70%).
Elimination: Excreted almost exclusively by the kidneys in urine as glucuronide conjugates and parent compound. Plasma elimination half-life () is approximately 2.5 to 3.5 hours.
Codeine depresses central nervous system functions, decreases gastrointestinal motility, and dampens the respiratory drive.
Very Common (): Constipation, somnolence, nausea.
Common ( to ): Vomiting, dizziness, lightheadedness, dry mouth, sweating, confusion, headache.
Uncommon ( to ): Miosis, ureteral or biliary spasm, urinary retention, euphoria, dysphoria, pruritus, rash, orthostatic hypotension.
Rare / Severe (<1/1,000): Severe respiratory depression, hallucinations, dependence/withdrawal syndrome, anaphylaxis, paralytic ileus.
Known hypersensitivity to codeine or other opioids.
Ultra-Rapid CYP2D6 Metabolizers: Individuals with CYP2D6 gene duplications convert codeine to morphine rapidly and unpredictably, leading to potentially fatal morphine toxicity.
Children under 12 years of age (contraindicated for all indications due to fatal respiratory risks).
Children aged 12 to 18 years undergoing tonsillectomy or adenoidectomy for obstructive sleep apnea.
Compromised respiratory function, acute severe asthma, or acute respiratory depression.
Lactating women (risk of passing toxic morphine levels to the nursing infant).
CYP2D6 Inhibitors (e.g., Fluoxetine, Paroxetine, Bupropion, Quinidine): Block the conversion of codeine to active morphine, significantly reducing or abolishing analgesic efficacy.
CYP3A4 Inhibitors & Inducers: Alter clearance pathways, modifying circulating levels of active metabolites.
CNS Depressants, Benzodiazepines, & Alcohol: Synergistic central nervous system depression markedly elevates the risk of profound sedation, life-threatening respiratory depression, coma, and death.
Boxed Warning (Ultra-Rapid Metabolism & Death in Children): Respiratory depression and death have occurred in children receiving codeine following surgery. Ultra-rapid metabolizers carry high risk at any age.
Pharmacogenomic Variability: CYP2D6 poor metabolizers experience minimal pain relief, while ultra-rapid metabolizers risk severe toxicity even at normal therapeutic doses.
Dependence and Tolerance: Continuous use leads to physical and psychological dependence. Abrupt discontinuation precipitates an opioid withdrawal syndrome (restlessness, lacrimation, rhinorrhea, abdominal cramps, diaphoresis).


 English English
 German
 Italian
 Dutch
 Spanish