- Il tuo carrello è vuoto
- Continua Lo Shopping


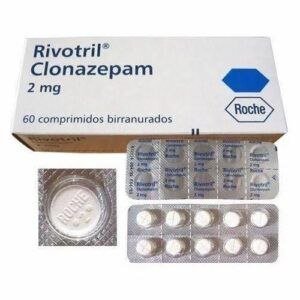
£ 51.80
Clonazepam 2 mg is a high-potency, long-acting nitrobenzodiazepine indicated for the management of seizure disorders, panic disorder, and specific neurological conditions. It functions by enhancing GABAergic transmission, suppressing focal seizure activity, and dampening central nervous system hyperarousal.
Clonazepam is a chlorinated derivative of nitrazepam belonging to the 1,4-benzodiazepine class. Chemically designated as 5-(2-chlorophenyl)-1,3-dihydro-7-nitro-2H-1,4-benzodiazepin-2-one, it exhibits high intrinsic binding affinity for central benzodiazepine receptor sites. Under the Anatomical Therapeutic Chemical (ATC) system, clonazepam is indexed under N03AE01.
The 2 mg dosage strength represents a high unit potency formulation. Internationally, clonazepam is classified as a Controlled Substance (e.g., Schedule IV under the US Controlled Substances Act; Schedule 4 / Prescription Only Medicine in Australia and Europe) due to its risks of physical dependence, tolerance, and misuse.
Clonazepam produces anticonvulsant, anxiolytic, muscle relaxant, and sedative properties via allosteric modulation of ionotropic receptors:
Receptor Potentiation: Binds with high affinity to the benzodiazepine site located between the , , , or subunits and the subunit of the receptor complex.
Chloride Channel Hyperpolarization: Increases the frequency of chloride channel opening induced by , resulting in neuronal membrane hyperpolarization and reduced postsynaptic firing.
Seizure Suppression: Dampens spike-and-wave discharges in absence seizures and limits the spread of paroxysmal neuronal activity in focal and generalized epilepsy.
Licensing for clonazepam includes:
Seizure Disorders: Alone or as an adjunct in the treatment of Lennox-Gastaut syndrome, akinetic and myoclonic seizures, and absence seizures (petit mal). It may also be used in patients with absence seizures who have failed to respond to succinimides.
Panic Disorder: Treatment of panic disorder with or without agoraphobia.
Dosing & Administration Regimen:
High-Potency Caution: The 2 mg tablet is a high single dose primarily reserved for maintenance therapy in seizure disorders. For panic disorder, initial dosing typically starts lower (0.25 mg to 0.5 mg/day) to minimize acute sedation.
Seizure Maintenance: Dosing is individualized, often up to 1.5 mg to 20 mg daily split into 2 or 3 doses, with titration adjusted slowly based on clinical response and tolerance.
Discontinuation: Therapy must never be abruptly stopped; dose reduction must follow a slow step-down protocol to prevent status epilepticus or severe withdrawal symptoms.
Absorption: Well absorbed following oral administration, with absolute bioavailability of ~90%. Peak plasma concentrations () are attained within 1 to 4 hours ().
Distribution: Highly lipid-soluble; plasma protein binding is approximately 85%. Crosses the blood-brain barrier, placental membrane, and distributes into breast milk.
Biotransformation: Extensively metabolized in the liver via nitroreduction by CYP3A4 and CYP2E1 to 7-amino-clonazepam, followed by acetylation to 7-acetamido-clonazepam. These major metabolites are functionally inactive.
Elimination: Excreted predominantly in urine as glucuronide or sulfate conjugates. Clonazepam is a long-acting agent with an elimination half-life () ranging from 30 to 40 hours.
Clonazepam causes pronounced central nervous system depression, leading to psychomotor retardation and decreased alertness.
Very Common (): Somnolence, drowsiness, fatigue, ataxia, dizziness, coordination disturbances.
Common ( to ): Dysarthria, memory impairment, confusion, depression, muscle weakness, upper respiratory tract infection/hypersecretion (especially in pediatric epilepsy).
Uncommon ( to ): Paradoxical agitation, irritability, hallucinations, libido changes, gastrointestinal distress, skin rash.
Rare / Severe (<1/1,000): Respiratory depression, blood dyscrasias (thrombocytopenia, leukopenia), severe withdrawal seizures, hepatic dysfunction.
Known hypersensitivity to clonazepam or other benzodiazepines.
Significant chronic or acute respiratory insufficiency or sleep apnea syndrome.
Severe hepatic impairment.
Acute narrow-angle glaucoma.
CNS Depressants, Opioids, & Alcohol: Synergistic central nervous system depression significantly escalates the risk of profound sedation, life-threatening respiratory arrest, coma, and death.
CYP3A4 Inducers (e.g., Carbamazepine, Phenytoin, Phenobarbital, Rifampicin): Accelerate clonazepam clearance, reducing systemic exposure and decreasing anticonvulsant efficacy.
CYP3A4 Inhibitors (e.g., Ketoconazole, Clarithromycin): Decrease clonazepam clearance, leading to elevated plasma levels and prolonged sedation.
Boxed Warning (Concomitant Opioid Use & Abuse/Dependence): Combined use with opioids increases risk of respiratory failure. Long-term use carries risk of physical dependence; abrupt withdrawal after continuous use can trigger life-threatening withdrawal seizures and delirium.
Antiepileptic Withdrawal Risk: Sudden discontinuation in patients with seizure disorders can precipitate status epilepticus.
Suicidality Monitoring: Like all antiepileptic drugs, clonazepam increases the risk of suicidal thoughts and behavior; monitor patients closely for emergence or worsening of depression.


 English English
 German
 Italian
 Dutch
 Spanish

