- Il tuo carrello è vuoto
- Continua Lo Shopping


Fascia di prezzo: £ 111.00 £ 421.80
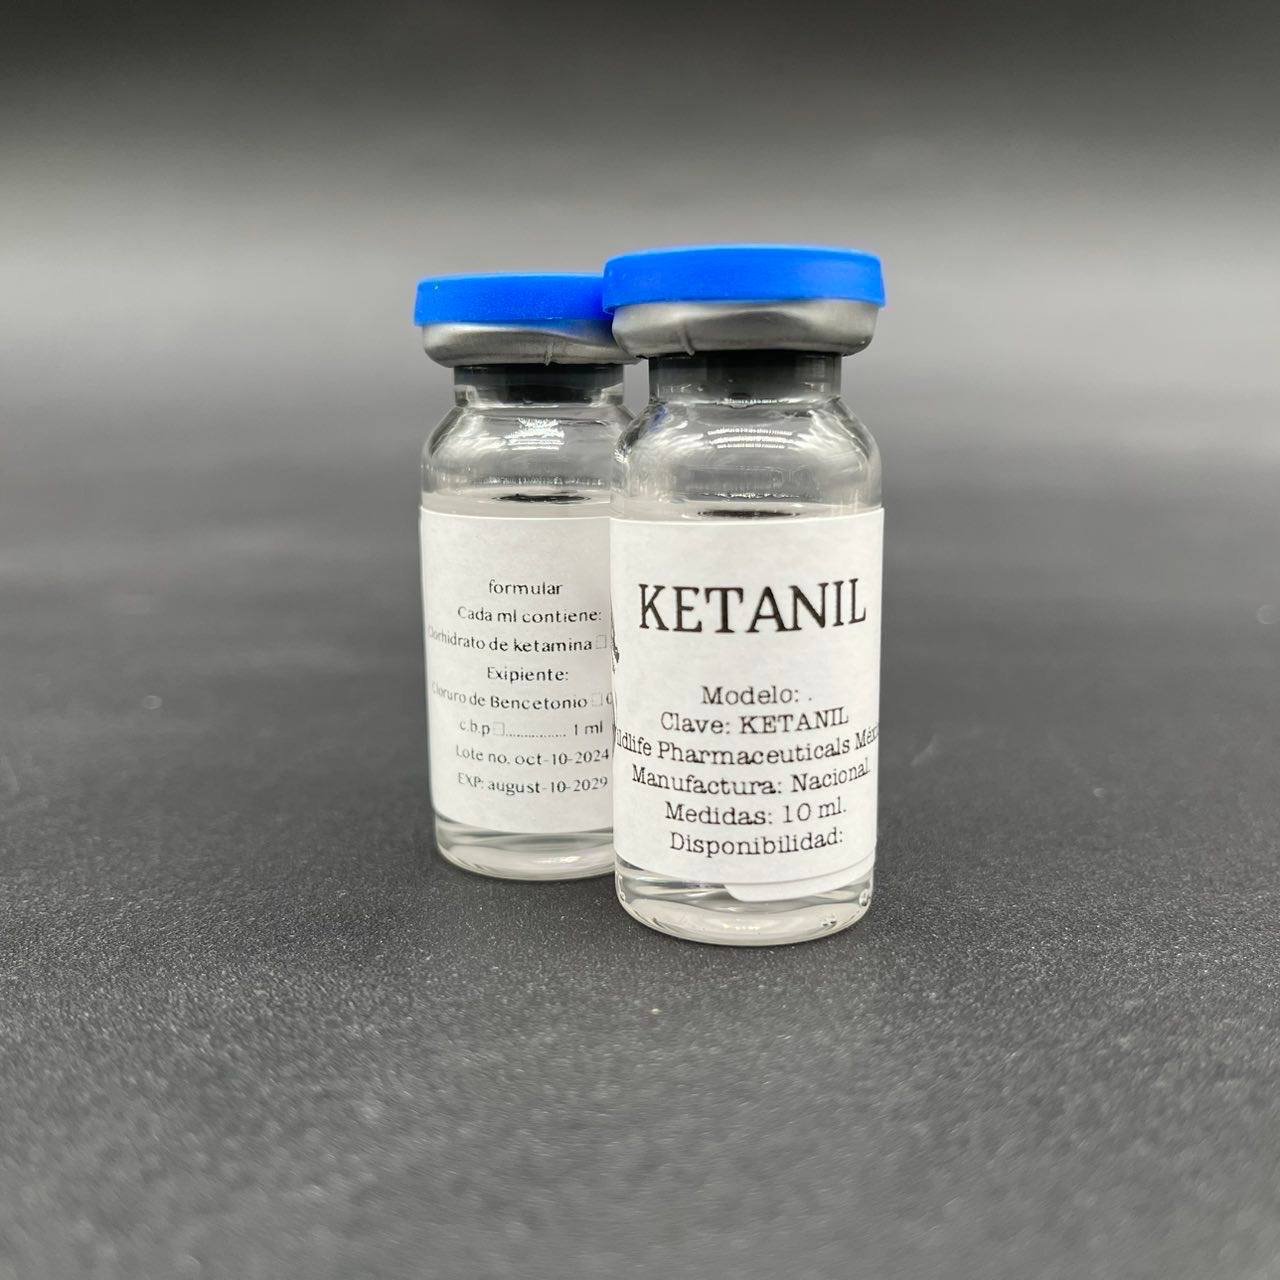
Ketamine hydrochloride is a synthetic, non-barbiturate, dissociative general anesthetic belonging to the arylcyclohexylamine class. Chemically designated as -2-(2-chlorophenyl)-2-(methylamino)cyclohexanone hydrochloride, it is a racemic mixture composed of two optical enantiomers (esketamine e arketamine). Under the Anatomical Therapeutic Chemical (ATC) system, ketamine is indexed under N01AX03.
In most global jurisdictions, ketamine is regulated as a strictly controlled substance (e.g., Schedule III under the US Controlled Substances Act; Schedule 2 Controlled Drug / Class B in the UK) due to its abuse potential and hallucinogenic profile. It is available strictly as a Prescription Only Medicine (POM) or for hospital-restricted administration.
Ketamine produces a unique “dissociative” state characterized by profound analgesia, amnesia, and catalepsy with maintained protective airway reflexes and spontaneous respiration, mediated through several key central nervous system targets:
NMDA Receptor Antagonism: Acts primarily as a non-competitive antagonist at -methyl--aspartate () ionotropic receptors in the central nervous system, blocking glutamate transmission and interrupting ascending pain pathways between the cortex and limbic structures.
Monoaminergic and Opioid Interactions: Interacts with μ-, -, and -opioid receptors (though with low affinity), inhibits neuronal reuptake of dopamine, serotonin, and norepinephrine, and interacts with muscarinic cholinergic and voltage-gated sodium channels.
Cardiovascular Stimulation: Unlike most anesthetics, ketamine stimulates the central sympathetic nervous system, increasing heart rate, mean arterial pressure, and cardiac output via catecholamine release.
Licensing and clinical utilization for liquid ketamine preparations include:
Anesthesia Induction & Maintenance: Induction of general anesthesia prior to surgical procedures, or maintenance of anesthesia using low-dose continuous infusions combined with other agents.
Procedural Sedation: Short-term diagnostic or surgical procedures where skeletal muscle relaxation is not heavily required and airway reflexes need to be preserved.
Refractory Pain Management: Adjunct treatment for severe acute traumatic pain or medically refractory chronic pain syndromes (e.g., complex regional pain syndrome) via low-dose infusions.
Dosing & Administration Regimen:
Parenteral Routes: Administered intravenously (IV) or intramuscularly (IM) by trained medical personnel. IV induction typically ranges from 1 to 2 mg/kg, while IM administration ranges from 4 to 10 mg/kg.
Strict Medical Setting: Due to potential for emergence delirium, hypertension, and transient respiratory depression, administration requires specialized monitoring equipment and airway management readiness.
Absorption: Rapidly absorbed following intramuscular injection, achieving peak plasma levels within 5 to 15 minutes. Intravenous administration provides immediate systemic onset (within 30 to 60 seconds).
Distribution: Highly lipid-soluble. Rapidly distributes across tissue compartments and crosses the blood-brain barrier and placenta. Volume of distribution () is approximately 3 L/kg. Plasma protein binding is low (~12% to 50%).
Biotransformation: Extensively metabolized in the liver via Cytochrome P450 enzymes (primarily CYP3A4 e CYP2B6):
-demethylation yields norketamine (an active metabolite possessing roughly 20% to 30% of the anesthetic potency of parent ketamine).
Subsequent hydroxylation yields dehydronorketamine and other polar metabolites before glucuronide conjugation.
Elimination: Excreted predominantly via the kidneys in urine as conjugated metabolites and unchanged drug (< 4%). The elimination half-life () of parent ketamine is approximately 2 to 3 hours.
Ketamine alters cardiovascular hemodynamics, intracranial pressure, and perceptual awareness.
Very Common (): Emergence reactions (vivid dreams, hallucinations, delirium, psychomotor agitation upon awakening), nystagmus, increased salivation, transient hypertension, tachycardia.
Common ( to ): Diplopia, blurred vision, nausea, vomiting, tonic-clonic movements, increased intracranial and intraocular pressure, injection site pain or rash.
Uncommon ( to ): Laryngospasm, respiratory depression (typically with rapid IV bolus administration), arrhythmias, bradycardia, cystitis / ulcerative cystitis (with chronic heavy use).
Rare (<1/1,000): Anaphylaxis, severe hypersensitivity reactions, hepatobiliary dysfunction.
Known hypersensitivity to ketamine or formulation excipients.
Conditions where significant elevation of blood pressure or intracranial pressure would be hazardous (e.g., severe uncontrolled hypertension, recent stroke, uncorrected aneurysms, severe cardiac decompensation, penetrating eye injuries with increased intraocular pressure).
History of schizophrenia or active psychosis (due to propensity to exacerbate psychotic symptoms).
CNS Depressants & Alcohol: Co-administration with barbiturates, opioids, benzodiazepines, or alcohol significantly prolongs recovery time and increases the risk of profound respiratory depression and apnea.
Sympathomimetics & Thyroid Hormones: Concomitant use with direct/indirect sympathomimetics or thyroid hormones can provoke severe hypertension and tachycardia.
CYP3A4/2B6 Inhibitors & Inducers: Agents that inhibit or induce hepatic cytochrome enzymes can alter ketamine clearance and affect duration of action.
Emergence Delirium Mitigation: Vivid hallucinations and dysphoria during recovery can be attenuated by co-administering short-acting benzodiazepines (e.g., midazolam).
Abuse and Misuse Liability: Ketamine possesses strong reinforcing properties and dissociative abuse potential, leading to psychological dependence, cognitive deficits, and severe urological toxicity (ketamine-induced ulcerative cystitis) with chronic non-medical use.
Airway Readiness: Resuscitative equipment and suction must be immediately available during administration due to risks of hypersalivation, airway obstruction, and transient apnea.
| Quantità | 5 fiale, 10 fiale, 25 fiale |
|---|


 English English
 German
 Italian
 Dutch
 Spanish