- Uw winkelwagen is leeg
- Verder Winkelen


Prijsklasse: £ 133.20 door £ 358.90
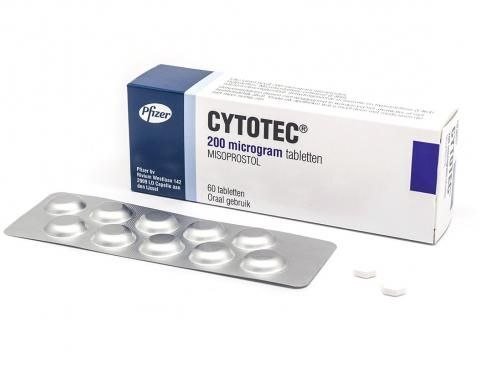
Cytotec 200mcg is an oral solid-dose pharmaceutical preparation containing misoprostol (originally developed by G.D. Searle & Company, now Pfizer, and distributed worldwide as innovator tablets and multi-source generic formulations). Chemically designated as $(\pm)\text{-methyl 7-[(1R,2R,3R)-3-hydroxy-2-[(E)-(4RS)-4-hydroxy-4-methyloct-1-en-1-yl]-5-oxocyclopentyl]heptanoate}$, misoprostol is a synthetic analogue of naturally occurring prostaglandin $E_1$ ($\text{PGE}_1$). Structurally, it consists of a cyclopentanone core with two aliphatic side chains: an $\alpha$-chain bearing a terminal methyl ester group (which confers superior oral bioavailability and metabolic stability compared to native $\text{PGE}_1$) and a modified $\omega$-chain incorporating a tertiary hydroxyl group and a methyl substitution at carbon-16. This synthetic alteration delays rapid metabolic inactivation by 15-hydroxyprostaglandin dehydrogenase, prolonging its pharmacological half-life. Its empirical molecular formula is $\text{C}_{22}\text{H}_{38}\text{O}_5$, with a molecular weight of $382.53\text{ g/mol}$.
Standard oral presentations of Cytotec in the United Kingdom and internationally consist of:
Tablet Morphology: White to off-white, hexagonal-shaped, flat-faced compressed tablets debossed with “SEARLE 1461” on one face and a bisecting score line on the reverse (or equivalent generic identifiers).
Strength & Formulation: Each unit delivers $200\text{ mcg}$ ($0.2\text{ mg}$) of active misoprostol. The bisecting line permits division into two equal $100\text{ mcg}$ halves.
Excipients: Formulated with a protective dispersion matrix to avoid degradation from moisture and temperature, typically utilizing microcrystalline cellulose, hydroxypropyl methylcellulose (hypromellose), sodium starch glycolate, hydrogenated castor oil, and colloidal silicon dioxide.
Within the United Kingdom and international regulatory frameworks:
Medicinal Classification (UK): Cytotec 200mcg is categorized as a Prescription Only Medicine (POM) governed by the Human Medicines Regulations 2012.
Controlled Drug Scheduling: Misoprostol is not a controlled substance under the Misuse of Drugs Act 1971 or the Misuse of Drugs Regulations 2001.
Regulatory Indication Divide:
Licensed MHRA Indication: Cytotec is formally licensed in the UK strictly for the healing and prevention of non-steroidal anti-inflammatory drug (NSAID)-induced gastric and duodenal ulceration in high-risk patients.
Unlicensed / Off-Label Obstetric & Gynaecological Use: In NHS hospital practice, Cytotec 200mcg is widely utilized off-label (supported by extensive clinical guidelines from the National Institute for Health and Care Excellence [NICE], the Royal College of Obstetricians and Gynaecologists [RCOG], and the World Health Organization [WHO]) for medical termination of pregnancy, management of miscarriage, cervical ripening, and induction of labour, alongside dedicated licensed formulations (e.g., Mysodelle vaginal inserts, Topogyne/Mifegyne regimens).
NHS Formulary Positioning: Catalogued in the British National Formulary (BNF) and listed on the NHS Drug Tariff.
Diversion, Counterfeiting, and Illicit Sourcing: Cytotec 200mcg is heavily traded on illicit online marketplaces and international grey-market parcel routes, specifically targeted by individuals seeking unmonitored self-managed abortions in jurisdictions with restrictive reproductive laws or without formal clinical consultation. Counterfeit Cytotec tablets purchased online frequently contain sub-therapeutic active drug, no active ingredient, or hazardous adulterants, while unmonitored administration carries critical risks of catastrophic haemorrhage, incomplete abortion, septic shock, and uterine rupture.
Misoprostol is an in vivo prodrug that undergoes rapid enzymatic de-esterification to its primary biologically active form, misoprostol acid. Misoprostol acid is a selective agonist at specific G-protein-coupled prostanoid EP receptors ($\text{EP}_1$, $\text{EP}_2$, $\text{EP}_3$, En $\text{EP}_4$), producing distinct tissue-specific effects:
Gastric Cytoprotective and Antisecretory Actions:
Acid Secretion Inhibition: Misoprostol acid binds directly to $\text{EP}_3$ receptors on gastric parietal cells. Agonism of $\text{EP}_3$ couples to pertussis toxin-sensitive inhibitory $G_{\alpha i}$ proteins, inhibiting adenylyl cyclase and blunting histamine-, gastrin-, and food-stimulated intracellular cyclic adenosine monophosphate (cAMP) accumulation. This directly downregulates the apical membrane $\text{H}^+/\text{K}^+\text{-ATPase}$ proton pump, suppressing basal and nocturnal gastric acid output.
Mucosal Cytoprotection: Agonism at $\text{EP}_2$ en $\text{EP}_4$ receptors on gastric superficial epithelial cells couples to stimulatory $G_{\alpha s}$ proteins, elevating intracellular cAMP. This stimulates mucosal bicarbonate secretion, increases protective mucus gel layer thickness, maintains submucosal blood flow, and enhances epithelial cell restitution, directly counteracting the ulcerogenic effects of NSAIDs (which deplete endogenous cytoprotective prostaglandins via cyclooxygenase-1 [COX-1] inhibition).
Myometrial and Uterine Pharmacodynamics:
Myometrial Contraction Induction: Binding to $\text{EP}_1$ en $\text{EP}_3$ receptors on uterine smooth muscle cells couples to $G_{\alpha q}$ en $G_{\alpha i}$ signaling cascades:
Activation of phospholipase C (PLC) generates inositol 1,4,5-trisphosphate ($\text{IP}_3$) and diacylglycerol (DAG).
$\text{IP}_3$ triggers rapid calcium ($Ca^{2+}$) release from the sarcoplasmic reticulum into the cytoplasm, while voltage-dependent calcium channels open.
Intracellular calcium binds calmodulin, activating myosin light-chain kinase (MLCK), which phosphorylates myosin regulatory light chains, generating coordinated, rhythmic myometrial contractions.
Gestational Sensitivity Gradient: Myometrial sensitivity to misoprostol is low in early pregnancy but escalates exponentially across gestation due to progressive upregulation of myometrial EP receptor density and gap junction formation. At term, even small doses ($25\text{ to }50\text{ mcg}$) can induce intense uterine hyperactivity.
Cervical Ripening Dynamics:
Misoprostol acid induces profound enzymatic and structural remodelling of the uterine cervix.
By stimulating local collagenase and elastase activity, it triggers the breakdown and disorganization of rigid cervical collagen fibril networks, increases glycosaminoglycan and water content, and promotes local vascular permeability. This softens, thins (effaces), and dilates the cervical os independent of uterine contractions.
Cytotec 200mcg spans two distinct clinical domains in UK practice: formal licensed gastrointestinal cytoprotection, and extensive guideline-backed off-label obstetric/gynaecological use.
Healing and Prevention of NSAID-Induced Ulcers:
Indicated for the treatment of active duodenal or benign gastric ulcers induced by NSAIDs in patients with high ulcer risk (e.g., elderly patients, history of peptic ulcer disease, concomitant corticosteroid or anticoagulant therapy).
Standard Adult Dosing: $200\text{ mcg}$ orally four times daily taken with meals and at bedtime (or $200\text{ mcg}$ twice or three times daily if not tolerated, though efficacy is reduced).
Duration: Typically administered for 4 to 8 weeks for active ulcer healing, or maintained continuously for the duration of essential NSAID therapy.
In NHS secondary care and specialist reproductive healthcare services, Cytotec 200mcg tablets (or licensed misoprostol equivalents) are utilized in standardized, evidence-based regimens:
Medical Termination of Pregnancy (MTP / Induced Abortion):
First Trimester (Up to 10+0 weeks’ gestation): Following oral administration of the antiprogestogen mifepristone ($200\text{ mg}$), misoprostol is administered 24 to 48 hours later:
$800\text{ mcg}$ (four $200\text{ mcg}$ tablets) administered via the buccal, sublingual, or vaginal route as a single dose.
Second Trimester (10+1 to 24+0 weeks’ gestation): Mifepristone $200\text{ mg}$ oral, followed 24–48 hours later by misoprostol $400\text{ mcg}$ orally, sublingually, or vaginally every 3 hours (up to a maximum of 4 to 5 doses) until fetal and placental expulsion.
Management of Early Pregnancy Loss (Miscarriage):
Medical Management of Incomplete or Missed Miscarriage: NICE Guideline NG126 recommends $800\text{ mcg}$ misoprostol as a single dose (vaginal, sublingual, or oral).
Cervical Preparation Prior to Surgical Abortion or Uterine Instrumentation:
$400\text{ mcg}$ sublingually 1 to 2 hours prior, or $400\text{ mcg}$ vaginally 3 hours prior to manual vacuum aspiration (MVA) or dilatation and evacuation (D&E).
Induction of Labour (Third Trimester / Post-Dates):
High-Risk Dosing: Standaard $200\text{ mcg}$ tablets are too high a strength for term induction of labour. In hospital labour wards, low-dose oral solutions ($20\text{ to }25\text{ mcg}$ titrated 2-hourly) or dedicated licensed sustained-release vaginal inserts ($200\text{ mcg}$ over 24 hours) are utilized under continuous cardiotocography (CTG) to prevent uterine tachysystole.
Prevention and Treatment of Postpartum Haemorrhage (PPH):
Treatment (Refractory PPH): $800\text{ mcg}$ sublingually (or $600\text{ to }1,000\text{ mcg}$ rectally) where parenteral uterotonics (oxytocin, ergometrine, carboprost) are unavailable or have failed.
The pharmacokinetic behavior of misoprostol varies significantly depending on whether it is administered orally, sublingually, buccally, or vaginally:
| Pharmacokinetic Parameter | Oral Ingestion | Sublingual Administration | Vaginal Administration |
| Absorption Rate | Extremely rapid | Rapid and extensive | Slow, gradual absorption |
| Peak Concentration ($T_{max}$) | $12\text{ to }15\text{ minutes}$ | $20\text{ to }30\text{ minutes}$ | $60\text{ to }80\text{ minutes}$ |
| Peak Plasma Level ($C_{max}$) | High ($288\text{ pg/mL}$ after $400\text{ mcg}$) | Highest ($575\text{ pg/mL}$) | Lower, plateaued ($125\text{ pg/mL}$) |
| Total Systemic Exposure ($AUC$) | Baseline reference | Highest overall $AUC$ | Comparable or higher than oral |
| Duration of Elevated Levels | Rapid decline by 2 hours | Prolonged systemic levels | Sustained levels for $>4\text{ to }6\text{ hours}$ |
| Plasma Protein Binding | $\sim 80\text{ to }90\%$ (bound primarily to albumin) | Same (active misoprostol acid) | Same (active misoprostol acid) |
| Primary Metabolism | De-esterification (esterases) $\to$ $\beta$-oxidation | Bypasses first-pass hepatic extraction | Bypasses first-pass hepatic extraction |
| Elimination Route | Renal ($70\text{ to }80\%$, polar metabolites) | Renal ($70\text{ to }80\%$) | Renal ($70\text{ to }80\%$) |
| Elimination Half-Life ($t_{1/2}$) | $20\text{ to }40\text{ minutes}$ (misoprostol acid) | $20\text{ to }40\text{ minutes}$ | Apparent $t_{1/2}$ prolonged by absorption |
Oral Route: Rapidly de-esterified during first-pass transit in the gastrointestinal tract to misoprostol acid. Fast $T_{max}$ and rapid clearance make oral ingestion ideal for acute gastric cytoprotection, but it causes higher rates of sudden gastrointestinal side effects (diarrhoea, cramps).
Sublingual Route: Placing tablets under the tongue yields the highest peak plasma concentration ($C_{max}$) and greatest bioavailability ($AUC$), avoiding hepatic first-pass metabolism. It produces rapid onset of uterine contractility and is the preferred route for acute PPH management and second-trimester termination.
Vaginal Route: Placing tablets into the posterior vaginal fornix leads to gradual transmucosal absorption, resulting in a lower initial $C_{max}$ but prolonged, steady plasma concentrations and sustained uterine tonus lasting up to 4 to 6 hours. This makes the vaginal route ideal for first-trimester medical abortion and cervical ripening.
Biotransformation & Clearance: Parent misoprostol is undetectable in peripheral plasma. Misoprostol acid undergoes extensive Phase I fatty acid-like $\beta$-oxidation and $\omega$-chain oxidation to polar, inactive dicarboxylic acid derivatives excreted via the kidneys. Clearance is largely independent of cytochrome P450 enzymes; clinically relevant hepatic CYP drug-drug interactions are minimal.
Therapeutic administration suppresses gastric acid, coats gastric mucosa, softens the cervix, and induces uterine contractions. However, systemic EP-receptor stimulation across the gastrointestinal, vascular, and thermoregulatory systems drives a characteristic adverse event profile:
Gastrointestinal Disturbances (Very Common, $\ge 1/10$):
Diarrhoea: The defining dose-dependent side effect, occurring in $15\text{ to }40\%$ of patients. Mediated by enteric $\text{EP}_2/\text{EP}_4$ receptors stimulating active enterocyte chloride and water secretion into the intestinal lumen, combined with $\text{EP}_1$-mediated propulsive motility. Usually self-limiting within 2 to 7 days, but can cause severe dehydration in prolonged therapy.
Abdominal pain, severe cramping, flatulence, dyspepsia, nausea, and vomiting.
Systemic and Thermoregulatory Effects (Common to Very Common):
Pyrexia and Rigors (Chills): Transient elevations in body temperature ($38.0^\circ\text{C}$ to $>40.0^\circ\text{C}$) accompanied by severe shivering and rigors occur in up to $30\text{ to }50\%$ of women receiving high sublingual or oral doses ($>400\text{ to }800\text{ mcg}$). This is a direct pharmacological effect on hypothalamic EP-mediated thermoregulatory set-points (not true infectious sepsis) and typically resolves spontaneously within 2 to 6 hours.
Headache, dizziness, and peripheral vasodilation (flushing).
Severe Gynaecological, Obstetric, and Life-Threatening Hazards:
Uterine Tachysystole and Uterine Hypertonus: Excessive dosage or hypersensitivity can trigger uterine contractions occurring at a frequency $>5\text{ in 10 minutes}$, or prolonged contractions lasting $>2\text{ minutes}$. In laboring patients, this compromises uteroplacental perfusion, producing acute fetal hypoxia, non-reassuring fetal heart rate patterns (prolonged bradycardia), and intrauterine demise.
Catastrophic Uterine Rupture: The most feared obstetric complication. When administered in the second or third trimester (especially in women with a scarred uterus from a previous Caesarean section, previous hysterotomy, or high parity), intense misoprostol-induced contractions can cause complete transmyometrial rupture. This precipitates massive intra-abdominal haemorrhage, hypovolaemic shock, fetal extrusion into the peritoneal cavity, hysterectomy, and maternal death.
Massive Obstetric Haemorrhage: Severe, unremitting uterine bleeding following medical abortion or incomplete miscarriage requires emergency surgical evacuation (curettage/aspiration) and blood product transfusion.
Infection and Septic Shock: Incomplete abortion with retained products of conception provides a nidus for ascending pelvic infection. Rare, fulminant septic shock from atypical pathogens (e.g., Clostridium sordellii, Clostridium perfringens) has been documented following medical abortion with mifepristone and misoprostol, presenting without fever but with marked leukocytosis, severe hemoconcentration, profound hypotension, and refractory tissue necrosis.
Teratogenicity (Möbius Syndrome Class Warning):
If pregnancy continues following failed or incomplete misoprostol exposure during the first trimester, misoprostol poses a substantial risk of major congenital malformations:
Möbius Syndrome: Congenital bilateral facial paralysis with abducens nerve palsy (inability to smile or move eyes laterally), frequently associated with limb-reduction defects (equinovarus / clubfoot, hypodactyly).
Mechanisme: Misoprostol-induced uterine hypercontractions trigger acute uteroplacental vascular disruption and transient embryo-fetal hypoperfusion during early organogenesis (weeks 5 to 8 post-conception).
Prescribing, dispensing, and administering Cytotec 200mcg mandates strict adherence to pregnancy exclusions, obstetric risk stratification, and emergency resuscitation readiness:
Contraindications:
Pregnancy in Gastrointestinal Prescribing: Absolute Contraindication. When prescribed for NSAID ulcer prophylaxis or peptic disease, misoprostol is absolutely contraindicated in women who are pregnant or planning pregnancy due to its potent abortifacient activity. Women of childbearing potential must have a documented negative serum/urine pregnancy test prior to initiation and use effective, reliable contraception throughout therapy.
Scarred Uterus in Third Trimester Labour Induction: Absolute contraindication for the induction of labour at term in women with a history of prior Caesarean delivery, classical hysterotomy, or extensive myomectomy due to the critical risk of uterine rupture.
Suspected Ectopic Pregnancy: Absolute contraindication in reproductive care; misoprostol is ineffective against tubal or non-uterine ectopic pregnancies. Unmonitored use risks catastrophic tubal rupture, intraperitoneal exsanguination, and maternal death.
Severe Active Pelvic Infection: Contraindicated prior to surgical or medical termination until appropriate antimicrobial cover is established.
Known Hypersensitivity: Hypersensitivity to misoprostol or other synthetic prostaglandins.
Breastfeeding: Misoprostol acid distributes into breast milk in small amounts; while low doses are compatible with nursing under clinical surveillance, it can induce transient diarrhea in the infant.
Drug Interactions:
Magnesium-Containing Antacids: Co-administration of misoprostol with antacids containing magnesium compounds (e.g., magnesium hydroxide, magnesium trisilicate) significantly compounds the frequency and severity of severe, watery diarrhoea. Concurrent antacids should be restricted to aluminum- or calcium-based agents.
Other Uterotonic Agents (e.g., Oxytocin, Ergometrine, Dinoprostone): Concomitant use exponentially magnifies uterine contractile force. If oxytocin is required following misoprostol administration for induction of labour, a mandatory waiting period of at least 4 to 6 hours must elapse after the last misoprostol dose before initiating an oxytocin infusion under continuous CTG monitoring.
NSAIDs: Pharmacodynamically complementary in gastrointestinal therapy; NSAIDs do not impair the anti-ulcer efficacy of misoprostol acid.
Cytochrome P450 Substrates/Inhibitors: Because misoprostol acid is cleared via fatty acid oxidation rather than CYP pathways, systemic CYP-mediated interactions (e.g., azoles, macrolides, rifampicin) are negligible.
Clinical Precautions and Emergency Management (“Red Flags”):
Management of Suspected Overdose / Uterine Tachysystole:
Massive overdose ($>2\text{ to }10\text{ mg}$) manifests as severe abdominal cramping, intractable diarrhoea, severe pyrexia ($>40^\circ\text{C}$), shivering, hypotension, tachycardia, dyspnoea, convulsions, and uterine hypertonus:
Supportive Resuscitation: Secure airway, deliver high-flow oxygen, and administer rapid intravenous crystalloid infusions ($0.9\%$ sodium chloride) to treat hypovolaemia and vasodilation.
Antipyresis: Treat profound drug-induced pyrexia with active external cooling (cooling blankets, iced packs) and parenteral paracetamol.
Tocolysis for Uterine Tachysystole: In pregnant patients exhibiting uterine hypertonus or fetal distress, immediately administer a fast-acting tocolytic agent—specifically subcutaneous terbutaline ($250\text{ mcg}$) or sublingual glyceryl trinitrate (GTN spray $400\text{ mcg}$)—to arrest excessive myometrial contractility and restore placental perfusion.
Emergency Surgical Readiness: If uterine rupture is suspected (manifesting as sudden loss of uterine contractions, sudden maternal hypotension/tachycardia, severe unremitting abdominal pain, or loss of fetal station on vaginal examination), proceed immediately to emergency exploratory laparotomy for hysterorrhaphy or subtotal hysterectomy.
Post-Abortion Monitoring Protocol: Healthcare practitioners must counsel patients undergoing medical termination on the critical difference between expected post-procedure bleeding and life-threatening haemorrhage (“soaking more than two heavy menstrual pads per hour for two consecutive hours” mandates immediate emergency department presentation).
Counterfeit Product Harm Reduction: Clinicians encountering individuals who obtained unprescribed Cytotec online must warn them of widespread black-market counterfeiting, verify gestational age and intrauterine location via ultrasound, exclude ectopic pregnancy, and ensure emergency surgical referral pathways are accessible.
| Hoeveelheid | 100 pillen, 200 pillen, 500 pillen |
|---|


 English English
 German
 Italian
 Dutch
 Spanish