- Uw winkelwagen is leeg
- Verder Winkelen


£ 40.70
Comprehensive UK clinical and toxicological monograph on Xenical 120mg hard capsules (orlistat) detailing reversible gastrointestinal lipase inhibition, triglyceride malabsorption mechanics, fat-soluble vitamin depletion, enteric hyperoxaluria risks, drug-drug interaction liabilities, and POM/NHS prescribing guidelines.
Xenical 120mg is the original innovator oral solid pharmaceutical brand containing orlistat (developed by Hoffmann-La Roche and distributed in the United Kingdom and internationally by entities including Cheplapharm Arzneimittel GmbH, alongside multi-source generic formulations). Chemically designated as $(2S)\text{-1-[(2S,3S)-3-hexyl-4-oxooxetan-2-yl]tridecan-2-yl (2S)-2-formamido-4-methylpentanoate}$, orlistat is a saturated, synthetic derivative of lipstatin, a natural, irreversible lipase inhibitor isolated from the actinobacterium Streptomyces toxytricini. Structurally, it consists of a central, reactive four-membered $\beta\text{-lactone}$ (2-oxetanone) ring substituted with an aliphatic lipophilic hexyl side chain and an esterified tridecyl backbone bearing an $N\text{-formyl-L-leucine}$ moiety. The strained $\beta\text{-lactone}$ ring acts as a mechanism-based suicide inhibitor, covalently acylating the active-site serine residue of gastrointestinal lipases. Its empirical molecular formula is $\text{C}_{29}\text{H}_{53}\text{NO}_5$, with an average molecular weight of $495.73\text{ g/mol}$.
Standard solid oral presentations of Xenical 120mg in the United Kingdom consist of:
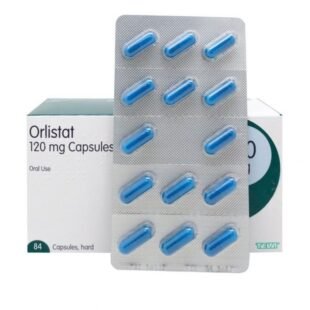
Capsule Presentation: Two-piece hard gelatin capsules featuring a turquoise-blue opaque cap and a turquoise-blue opaque body, debossed with “ROCHE” on the cap and “XENICAL 120” on the body using black pharmaceutical ink.
Core Composition: Each capsule contains a pelletized formulation of $120\text{ mg}$ of orlistat.
Excipients: Formulated with microcrystalline cellulose (E460), sodium starch glycolate (type A), colloidal anhydrous silica, and sodium lauryl sulfate. The capsule shell is composed of gelatin, titanium dioxide (E171), and indigo carmine (E132), sealed to prevent degradation from atmospheric moisture.
Within the United Kingdom and international regulatory frameworks:
Medicinal Classification: Xenical 120mg is categorized as a Prescription Only Medicine (POM) governed by the Human Medicines Regulations 2012.
Over-the-Counter Low-Dose Tier: A lower-strength $60\text{ mg}$ presentation (e.g., Alli) is classified as a Pharmacy (P) medicine, legally available over the counter under pharmacist supervision for adults with a $\text{BMI} \ge 28\text{ kg/m}^2$.
Controlled Drug Scheduling: Orlistat is not a controlled substance under the Misuse of Drugs Act 1971 or the Misuse of Drugs Regulations 2001. It possesses zero central nervous system activity and exhibits no intrinsic abuse liability or physical dependence potential.
NHS Formulary Positioning & NICE Guidelines: Catalogued in the British National Formulary (BNF) and listed on the NHS Drug Tariff. Reimbursed under strict criteria defined by the National Institute for Health and Care Excellence (NICE Clinical Guideline CG189: Obesity), serving as a standard non-systemic oral pharmacological adjunct to dietary intervention.
Counterfeiting and Illicit Sourcing: Because Xenical is a globally recognized weight-loss brand, counterfeit capsules circulate widely on unverified online marketplaces and unauthorized social channels. Illicitly manufactured products sold as “Xenical” frequently contain variable or sub-therapeutic orlistat, inert bulking powders, or dangerous unlisted pharmacological adulterants—such as banned central anorectics (e.g., sibutramine), synthetic cathinones, or industrial diuretics—presenting severe cardiovascular and cerebrovascular toxicological risks.
Unlike centrally acting appetite suppressants that modulate hypothalamic neurotransmission (e.g., phentermine, amfetamines), orlistat acts locally within the gastrointestinal lumen and exerts virtually no direct systemic or central neurochemical effects:
Covalent Inhibition of Gastrointestinal Lipases:
Orlistat operates as a reversible, mechanism-based inhibitor of gastric lipase (secreted by gastric chief cells) and pancreatic lipase (secreted by the acinar cells of the exocrine pancreas).
Within the lumen of the stomach and upper small intestine, orlistat targets the catalytic triad of these enzymes. The strained electrophilic carbonyl carbon of orlistat’s $\beta\text{-lactone}$ ring undergoes nucleophilic attack by the active-site serine residue ($\text{Ser}^{152}$ in pancreatic lipase), forming an inactive, stable covalent hemiacetal ester adduct:
This covalent ester bond acylates the enzyme, completely preventing the active site from interacting with dietary lipids.
Blockade of Triglyceride Hydrolysis:
Under normal physiological conditions, gastrointestinal lipases hydrolyze non-absorbable dietary triglycerides into absorbable free fatty acids and 2-monoacylglycerols.
Inactivation of these lipases leaves approximately $30\%$ of ingested dietary triglycerides unhydrolyzed.
Lipid Malabsorption and Caloric Deficit:
Intact triglycerides cannot cross the brush-border membrane of enterocytes via passive diffusion or fatty acid translocase (CD36) mechanisms.
Unhydrolyzed triglycerides remain within the gastrointestinal lumen, passing unabsorbed through the small intestine and colon to be eliminated in the feces.
At the recommended therapeutic dose of $120\text{ mg}$ three times daily, orlistat produces an approximate $30\%$ reduction in dietary fat absorption, generating a consistent caloric deficit of roughly $200\text{ to }300\text{ kcal/day}$ (dependent on total dietary fat intake), which drives steady weight loss.
Secondary Physiological Consequences:
Fat-Soluble Nutrient Depletion: Dietary triglycerides form the essential micellar vehicle required for the luminal solubilization and passive absorption of fat-soluble vitamins (vitamins A, D, E, and K) and lipophilic carotenoids ($\beta$-carotene). Substantial lipid malabsorption decreases the systemic bioavailability of these micronutrients.
Enteric Calcium and Oxalate Saponification Dynamics: Unabsorbed free fatty acids in the colonic lumen bind (saponify) luminal divalent cations, primarily free calcium ($\text{Ca}^{2+}$). Calcium, which normally binds dietary oxalate in the gut to form an insoluble, non-absorbable calcium oxalate complex excreted in feces, is depleted. Unbound, free soluble oxalate remains available for passive colonic hyperabsorption, driving enteric hyperoxaluria and predisposing patients to nephrolithiasis and oxalate nephropathy.
Xenical 120mg holds recognized clinical indications under the British National Formulary (BNF) and NICE Guideline CG189 (Obesity: identification, assessment and management):
Adjunctive Treatment of Obesity:
Indicated as an adjunct to a mildly hypocaloric, nutritionally balanced, lower-fat diet (where approximately $30\%$ of total calories are derived from fat) for the management of obesity in patients meeting strict baseline criteria:
An initial Body Mass Index (BMI) of $\ge 30\text{ kg/m}^2$, OR
An initial BMI of $\ge 28\text{ kg/m}^2$ in the presence of weight-related risk factors or co-morbidities (e.g., type 2 diabetes mellitus, hypertension, dyslipidemia, metabolic syndrome, obstructive sleep apnea).
Prescribed Adult Dosing Regimen:
$120\text{ mg}$ (one capsule) orally three times daily, taken with water immediately before, during, or up to one hour after each main meal.
Meal Omission Rule: If a meal is missed or contains absolutely no fat, the dose of Xenical should be omitted, as the pharmacological target is absent.
Maximum Dosing Ceiling: Doses above $120\text{ mg}$ three times daily demonstrate no additional therapeutic weight-loss benefit, but significantly escalate the frequency and severity of adverse gastrointestinal events.
NICE Prescribing Rules and Discontinuation Criteria (“12-Week Rule”):
Under NHS prescribing standards, orlistat therapy must be reviewed at 12 weeks following initiation.
Treatment should only be continued beyond 12 weeks if the patient has lost at least $5\%$ of their initial body weight from the start of therapy.
Special Population (Type 2 Diabetes): Patients with type 2 diabetes often exhibit slower rates of weight reduction; NICE guidelines permit continuing therapy if the patient has achieved a weight loss of at least $3\%$ of their initial body weight at 12 weeks, accompanied by documented improvements in glycemic control (e.g., reductions in $\text{HbA}_{1c}$).
Maximum Treatment Duration: The standard licensed and NICE-supported duration of continuous therapy is up to 12 months (rarely extended beyond 24 months, where annual formal clinical re-evaluation of nutritional status and renal parameters is mandatory).
Pediatric and Adolescent Restrictions:
Xenical is not licensed for use in children and adolescents under 18 years of age in the UK, due to insufficient long-term safety, growth, and nutritional data. (Specialist pediatric multidisciplinary obesity services may initiate off-label orlistat under tertiary supervision only in adolescents $\ge 12$ years with severe obesity complicated by life-threatening comorbidities).
In non-medical, eating disorder, or unauthorized settings:
Misused by individuals with body dysmorphic disorder, anorexia nervosa, or bulimia nervosa as a purging or non-absorptive compensation method.
Acquired online without medical supervision by individuals of normal body weight ($\text{BMI} < 25\text{ kg/m}^2$) seeking cosmetic weight reduction, exposing them to acute micronutrient depletion and electrolyte shifts without therapeutic justification.
The pharmacokinetic behavior of Xenical 120mg is defined by minimal systemic absorption, extensive luminal retention, and almost exclusive fecal elimination:
| Pharmacokinetic Parameter | Value / Metric | Clinical Interpretation |
| Systemic Bioavailability | $<1\text{ to }2\%$ (Minimal) | Acts locally within the gut lumen; systemic exposure is negligible. |
| Time to Peak Concentration ($T_{max}$) | $6.0\text{ to }8.0\text{ hours}$ | Represents trace systemic absorption; clinically irrelevant to efficacy. |
| Volume of Distribution ($V_d$) | Not determinable | Systemic distribution is minimal; $>99\%$ remains confined to the gut. |
| Plasma Protein Binding | $>99\%$ (of the absorbed trace fraction) | Circulates bound primarily to albumin and lipoproteins. |
| Metabolic Site | Gastrointestinal wall (predominantly) | Metabolized presystemically within the intestinal mucosa. |
| Major Inactive Metabolites | M1 (hydrolyzed $\beta$-lactone), M3 (cleaved $N$-formylleucine) | Extremely weak lipase inhibitors ($>1,000$-fold less potent); non-toxic. |
| Primary Elimination Route | Feces ($\sim 97\%$, $83\%$ as unchanged parent drug) | Excreted via stool; clears completely within 3 to 5 days. |
| Renal Elimination | $<2\%$ (Cumulative) | Minimal renal clearance; trace polar metabolites only. |
| Elimination Half-Life ($t_{1/2}$) | $1\text{ to }2\text{ hours}$ (absorbed fraction) | Unabsorbed drug transit time mirrors normal fecal transit (24–48 hours). |
Presystemic Inactivation: The minute fraction of orlistat ($<1\%$) that traverses the intestinal brush-border membrane undergoes rapid, presystemic biotransformation within the enterocytes of the gastrointestinal wall.
Metabolite Formation: Hydrolysis of the $\beta\text{-lactone}$ ring generates metabolite M1 (a 4-ring open structure), which subsequently undergoes cleavage of its $N\text{-formyl-L-leucine}$ side chain to yield metabolite M3. Both metabolites possess negligible lipase-inhibitory activity ($<0.1\%$ that of orlistat) and circulate at extremely low concentrations without biological effect.
Cytochrome P450 Non-Involvement: Orlistat does not induce or inhibit major hepatic cytochrome P450 enzymes (CYP1A2, CYP2D6, CYP3A4, CYP2C9, CYP2C19). Its drug interactions are driven almost entirely by luminal absorption interference rather than hepatic metabolic competition.
Fecal Normalization: Following cessation of therapy, fecal fat content and lipase activity return to pre-treatment physiological baselines within 48 to 72 hours.
Therapeutic administration induces progressive weight reduction, improves peripheral insulin sensitivity, reduces fasting plasma glucose, and lowers total and low-density lipoprotein (LDL) cholesterol. However, the presence of substantial quantities of unabsorbed dietary fat within the lower intestinal tract produces a hallmark spectrum of local gastrointestinal adverse effects:
Gastrointestinal Adverse Effects (Very Common, $\ge 1/10$):
Oily Spotting (Steatorrhea): Passage of unabsorbed liquid fat per rectum, frequently staining undergarments without prior sensation of defecation.
Fecal Urgency and Incontinence: Inability to retain oily rectal contents, leading to involuntary fecal soiling.
Flatus with Discharge: Passing gas accompanied by unabsorbed oily liquid droplets.
Fatty / Oily Evacuations: Stools that are pale, bulky, greasy, malodorous, and float in the toilet bowl.
Fecal frequency, flatulence, abdominal pain, and liquid/soft stools.
Dietary Correlation: The frequency and severity of these gastrointestinal effects are directly proportional to dietary fat intake. Ingesting a high-fat meal ($>30\%$ total fat) while taking Xenical causes severe, explosive steatorrhea and abdominal cramping, functioning as a behavioral aversive-conditioning mechanism.
Nutritional and Micronutrient Deficiencies (Common, $1/100$ to $<1/10$):
Fat-Soluble Vitamin Depletion: Subclinical or clinical reductions in circulating serum concentrations of vitamins A, D, E, and K, as well as $\beta$-carotene, occur during long-term therapy:
Vitamin D Deficiency: Can compound bone mineral density loss and precipitate secondary hyperparathyroidism.
Vitamin K Depletion: Disrupts hepatic synthesis of clotting factors (II, VII, IX, X), prolonging prothrombin time (INR) in patients taking oral anticoagulants.
Severe, Emergent and Life-Threatening Hazards:
Enteric Hyperoxaluria and Oxalate Nephropathy:
Unabsorbed luminal fatty acids saponify with dietary calcium, leaving unbound soluble oxalate free to be hyperabsorbed across the colonic mucosa.
Increased urinary oxalate excretion can precipitate calcium oxalate crystals in the renal parenchyma, leading to calcium oxalate nephrolithiasis, acute oxalate nephropathy, interstitial fibrosis, and irreversible end-stage renal disease (ESRD), particularly in patients with baseline chronic kidney disease (CKD) or volume depletion.
Severe Hepatic Injury (Rare Post-Marketing Safety Alert):
Rare cases of acute hepatic injury—including hepatocellular necrosis, acute hepatic failure, and hepatic encephalopathy requiring liver transplantation—have been reported to the MHRA and FDA. While causality remains controversial due to low systemic absorption, any emergence of clinical signs of hepatic injury (jaundice, pruritus, dark urine, pale stools, right upper-quadrant abdominal pain) mandates immediate cessation.
Cholelithiasis and Biliary Colic: Rapid weight reduction induced by orlistat alters biliary cholesterol saturation, accelerating the formation of cholesterol gallstones and precipitating acute cholecystitis or biliary colic.
Prescribing and monitoring Xenical 120mg requires strict adherence to anatomical contraindications, nutritional surveillance, and luminal drug-absorption interaction screening:
Contraindications:
Chronic Malabsorption Syndrome: Absolute Contraindication. Patients with pre-existing gastrointestinal malabsorption (e.g., short-bowel syndrome, untreated celiac disease, cystic fibrosis, extensive Crohn’s disease) risk severe, life-threatening nutritional and micronutrient collapse.
Cholestasis: Absolute contraindication; impaired biliary drainage already limits normal micellar lipid digestion, worsening fat malabsorption.
Pregnancy and Breastfeeding: Absolute Contraindication. Weight loss offers no clinical benefit during pregnancy and can induce maternal-fetal micronutrient starvation; unknown whether trace metabolites distribute into breast milk, but fat malabsorption can disrupt infant nutritional intake.
Known Hypersensitivity: Hypersensitivity to orlistat or any of the capsule excipients.
Drug Interactions (Luminal Absorption Interference):
Ciclosporin (Critical Immunosuppressive Hazard): Orlistat significantly impairs the gastrointestinal absorption of ciclosporin, reducing its plasma $AUC$ by up to $30\text{ to }50\%$. In organ transplant recipients, this precipitates acute graft rejection.
Management: If co-administration cannot be avoided, ciclosporin must be administered at least 3 hours before or 3 hours after Xenical, accompanied by frequent therapeutic drug monitoring (TDM) of trough blood levels.
Levothyroxine (Endocrine Interaction): Co-administration can reduce the absorption of levothyroxine, leading to clinical hypothyroidism and elevated thyroid-stimulating hormone (TSH). Doses must be separated by a minimum interval of at least 4 hours, with regular thyroid function surveillance.
Vitamin K Antagonists (Warfarin, Phenprocoumon): By reducing vitamin K absorption, orlistat can amplify the anticoagulant response, leading to unexplained elevations in prothrombin time / INR and increased hemorrhage risks. Co-prescribing mandates close INR monitoring.
Antiepileptic Drugs (e.g., Sodium Valproate, Lamotrigine, Phenytoin): Orlistat can decrease the absorption of oral antiepileptics, precipitating breakthrough seizures. Prescribers must monitor anticonvulsant plasma concentrations and seizure frequency.
Fat-Soluble Vitamin Supplements: Routine oral multivitamin preparations containing vitamins A, D, E, and K should be separated from orlistat by at least 2 hours (ideally administered at bedtime) to avoid malabsorption of the supplement itself.
Oral Contraceptives: While orlistat does not directly interact pharmacokinetically with synthetic estrogens or progestogens, severe or persistent diarrhea induced by orlistat can impair contraceptive pill absorption. Patients must be advised to employ secondary barrier contraception in the event of severe, continuous diarrhea.
Clinical Precautions and Long-Term Surveillance:
Nutritional and Vitamin Supplementation Mandate:
In patients maintained on long-term Xenical therapy ($>6\text{ months}$), clinicians should consider co-prescribing a daily fat-soluble multivitamin supplement (containing vitamins A, D, E, K, and $\beta$-carotene) taken once daily at bedtime.
Renal Risk Surveillance:
Baseline and periodic renal function testing (serum creatinine, eGFR) and urinalysis for microhematuria/crystalluria should be performed in patients with pre-existing CKD or those at risk of hyperoxaluria and calcium oxalate kidney stones. Patients must be counseled to maintain adequate systemic hydration ($2\text{ to }3\text{ L/day}$ of water) to minimize urinary oxalate crystallization.
Dietary Fat Counseling:
Patients must be educated that Xenical is not a license to consume unrestricted dietary fat. The daily intake of fat must be distributed evenly across the three main meals. Ingestion of an isolated high-fat meal ($>35\text{ to }40\text{ g}$ of fat in a single sitting) will universally provoke severe steatorrhea, cramping, and fecal incontinence.
Acute Overdose Management (“Red Flags”):
Ingestion of massive single doses (up to $800\text{ mg}$ acutely) or chronic cumulative doses up to $400\text{ mg}$ three times daily has been evaluated in clinical trials; systemic toxicity is absent due to negligible absorption.
Massive acute overdose presents primarily as profuse, watery, oily diarrhea, severe abdominal cramping, and secondary volume depletion:
Supportive Fluid Resuscitation: Administer oral or intravenous rehydration solutions to correct dehydration and electrolyte losses.
Observation: Monitor for systemic fluid loss and electrolyte derangements; gastric lavage or activated charcoal is rarely required unless co-ingestants are suspected.
 English English
 German
 Italian
 Dutch
 Spanish