- Uw winkelwagen is leeg
- Verder Winkelen


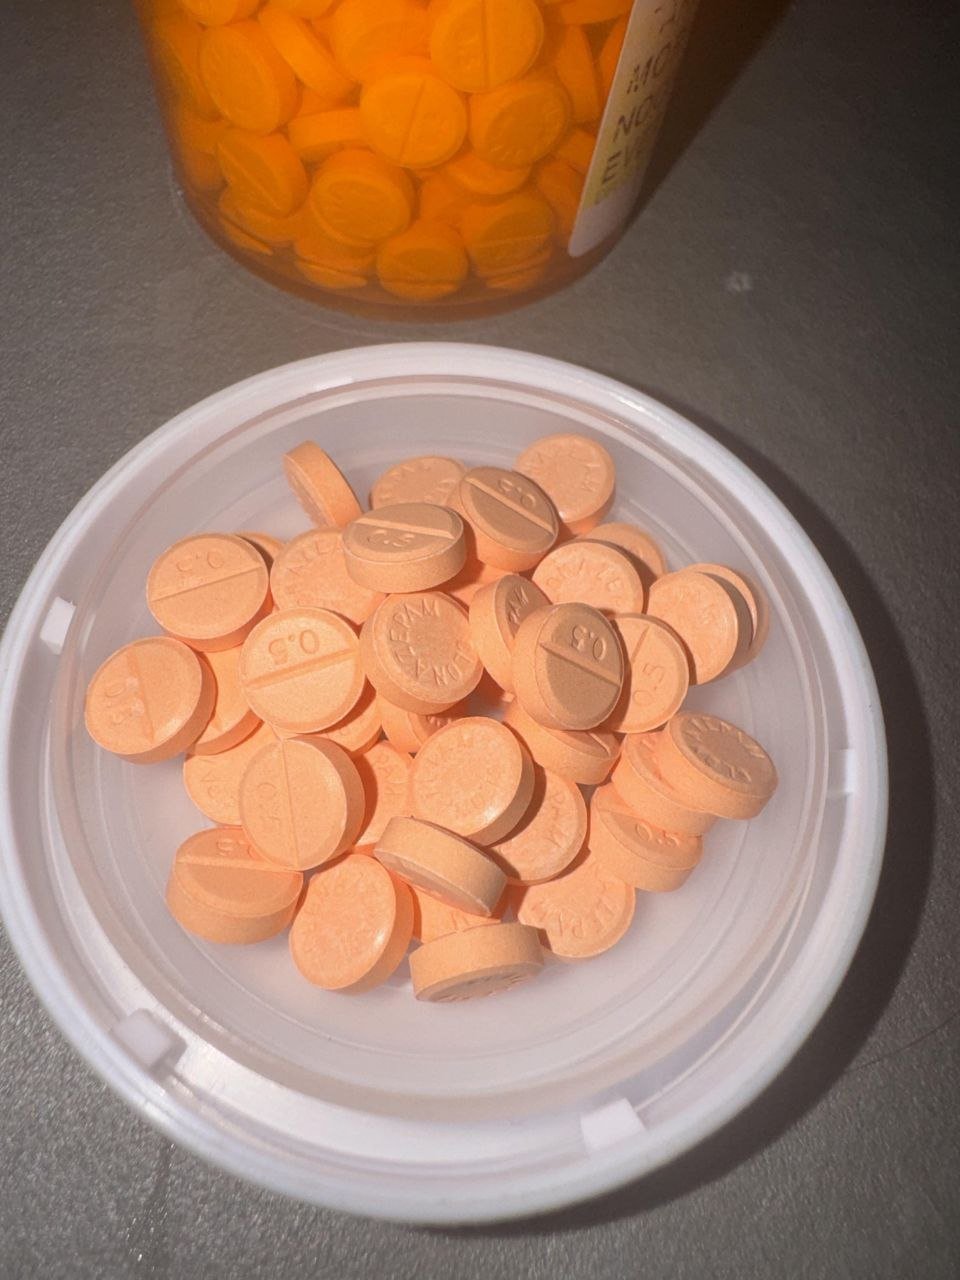
Prijsklasse: £ 103.60 door £ 214.60
Clonazepam 0.5mg is a licensed branded and generic oral solid pharmaceutical preparation (originally developed and commercialized under innovator trade names such as Rivotril). Chemically designated as $5\text{-(2-chlorophenyl)-7-nitro-1,3-dihydro-2H-1,4-benzodiazepin-2-one}$, clonazepam is a synthetic psychoactive compound belonging to the nitrobenzodiazepine subclass. Structurally, it features a core 1,4-benzodiazepine nucleus characterized by an electronegative nitro group ($\text{-NO}_2$) attached at the carbon-7 position and an ortho-chlorophenyl ring substitution at the carbon-5 position. This combination of electron-withdrawing substituents confers high binding affinity at the central benzodiazepine receptor site. Its empirical molecular formula is $\text{C}_{15}\text{H}_{10}\text{ClN}_3\text{O}_3$, with an average molecular weight of $315.71\text{ g/mol}$.
Standard solid oral presentations of Clonazepam 0.5mg in the United Kingdom appear as round, flat or bi-convex, pale orange to peach-colored compressed scored tablets (frequently colored with iron oxide pigments). Tablets characteristically feature a score line or cross-score on one face, permitting accurate division into equal halves ($0.25\text{ mg}$) to facilitate slow titration and gradual discontinuation. Standard non-active pharmaceutical excipients include lactose monohydrate, maize starch, pregelatinized potato starch, microcrystalline cellulose, magnesium stearate, and iron oxide yellow/red (E172).
Within the United Kingdom regulatory framework:
Medicinal Classification: Clonazepam 0.5mg is categorized as a Prescription Only Medicine (POM) governed by the Human Medicines Regulations 2012.
Controlled Drug Status: Under the Misuse of Drugs Act 1971 and the Misuse of Drugs Regulations 2001, clonazepam is scheduled as a Class C, Schedule 4 (Part 1 / CD Benz POM) controlled substance.
Formulary Availability: Clonazepam is authorized by the Medicines and Healthcare products Regulatory Agency (MHRA), catalogued in the British National Formulary (BNF), and listed on the NHS Drug Tariff, making it reimbursable via standard NHS prescription forms (FP10) primarily for specialist neurological and psychiatric indications.
While clonazepam is available through authorized primary and secondary care pathways, diverted or counterfeit “Clonazepam 0.5mg” (or imported foreign-market Rivotril) acquired via grey-market internet portals represents an acute public health hazard. Forensic analyses of illicit supplies frequently reveal active dosage variance or complete substitution with potent novel synthetic designer benzodiazepines (e.g., clonazolam, bromazolam) or synthetic opioids (such as nitazenes).
The pharmacodynamic profile of clonazepam is defined by potent, high-affinity positive allosteric modulation of inhibitory neurotransmission across the central nervous system (CNS):
Positive Allosteric Modulation of the $GABA_A$ Receptor: Clonazepam binds stereospecifically to the high-affinity benzodiazepine recognition pocket situated at the interface between the $\alpha$ ($\alpha_1$, $\alpha_2$, $\alpha_3$, or $\alpha_5$) and $\gamma_2$ subunits of the pentameric $\gamma\text{-aminobutyric acid type A}$ ($GABA_A$) ligand-gated chloride channel complex.
Chloride Conductance and Hyperpolarization: Clonazepam possesses no intrinsic agonist properties in the absence of endogenous $\text{GABA}$. When endogenous $\text{GABA}$ binds to its orthosteric sites, clonazepam induces an allosteric conformational shift that increases the frequency of chloride channel opening bursts. The resulting influx of extracellular chloride ions ($Cl^-$) down an electrochemical gradient hyperpolarizes the postsynaptic neuronal membrane, stabilizing the resting membrane potential below firing threshold and suppressing action potential propagation across subcortical, cortical, and spinal pathways.
Subunit-Mediated Clinical Pharmacodynamics and Anticonvulsant Potency:
$\alpha_1$ Subunit Interactions: Predominant in the cerebral cortex, thalamus, and cerebellum; mediates sedative, hypnotic, and broad anticonvulsant actions. Clonazepam exhibits a pronounced capacity to suppress generalized spike-and-wave paroxysms, cortical epileptic foci, and subcortical seizure spread.
$\alpha_2$ en $\alpha_3$ Subunit Interactions: Concentrated within the limbic networks (amygdala, hippocampus) and spinal motor pathways; responsible for anxiolytic, anti-panic, and central muscle-relaxant actions.
$\alpha_5$ Subunit Interactions: Localized primarily within the hippocampus; mediates spatial memory disruption, cognitive clouding, and temporal memory processing deficits.
Relative Potency and Serotonergic Turnover: Clonazepam is a high-potency benzodiazepine: $0.5\text{ mg}$ of oral clonazepam is clinically bioequivalent to approximately $10\text{ mg}$ of oral diazepam (a 20:1 potency ratio). Electrophysiological and neurochemical investigations indicate that clonazepam enhances central 5-hydroxytryptamine (serotonin) synthesis and turnover, contributing to its secondary clinical utility in movement disorders, panic disorder, and myoclonus.
Clonazepam holds licensed indications in the United Kingdom primarily within clinical neurology, with restricted secondary utilization in psychiatric practice:
Epilepsy in Adults and Children (Licensed UK Indication):
Indicated as monotherapy or adjunctive therapy for the management of most clinical forms of epilepsy, particularly absence seizures (petit mal), Lennox-Gastaut syndrome, infantile spasms (West syndrome), myoclonic seizures, and tonic-clonic seizures refractory to first-line antiepileptic drugs (AEDs).
Standard Dosing: In adults, treatment is typically initiated at $0.5\text{ mg}$ at bedtime, titrating slowly in increments of $0.5\text{ mg}$ every 3 to 4 days until an optimal maintenance dose (usually $4\text{ to }8\text{ mg/day}$ in divided doses) is achieved. In elderly patients, a conservative starting dose of $0.25\text{ mg}$ of $0.5\text{ mg}$ is indicated.
Secondary / Off-Label Psychiatric Indications (Specialist Setting):
Panic Disorder with or without Agoraphobia: Short-term stabilization of acute panic attacks refractory to non-pharmacological interventions or SSRIs ($0.25\text{ to }0.5\text{ mg}$ BD, up to $1\text{ to }2\text{ mg/day}$).
REM Sleep Behaviour Disorder (RBD): First-line therapy for motor disinhibition and violent dream enactment during REM sleep ($0.5\text{ to }2\text{ mg}$ at bedtime).
Severe Akathisia and Acute Mania Adjunct: Short-term management of neuroleptic-induced motor restlessness or acute psychomotor agitation.
Prescribing Duration and NICE Guidance:
In non-epileptic conditions, treatment must be restricted to the lowest effective dose for a maximum duration of 2 to 4 weeks (inclusive of a gradual tapering phase) to prevent physical dependence.
NICE Clinical Guideline CG113 (Anxiety and Panic): Explicitly advises against the long-term use of benzodiazepines for generalized anxiety and panic disorders, citing tolerance, cognitive blunting, withdrawal risks, and rebound anxiety. First-line therapies remain SSRIs, SNRIs, and structured Cognitive Behavioural Therapy (CBT).
In unauthorized and non-medical contexts, Clonazepam 0.5mg is misused for:
Terminating psychostimulant-induced over-arousal (“comedowns” following cocaine, amfetamines, MDMA, or synthetic cathinones).
Recreational intoxication sought for prolonged emotional detachment, chemical anxiolysis, and disinhibition.
Polydrug stacking with alcohol or opioids.
Because Clonazepam 0.5mg is an immediate-release oral solid tablet, its disposition is characterized by high oral bioavailability, intermediate absorption velocity, a broad distribution profile, and extensive hepatic nitro-reduction:
Absorption: Following oral administration, clonazepam is absorbed rapidly and near-completely across the gastrointestinal tract. Peak plasma concentrations ($C_{max}$) are attained within 1 to 4 hours (median $T_{max} \approx 2\text{ hours}$) in a fasting state. Absolute oral bioavailability is high, averaging $82\text{ to }98\%$. Co-administration with food slows the rate of absorption, slightly delaying $T_{max}$, but does not significantly reduce the total area under the curve ($AUC$).
Distribution: Clonazepam displays high lipophilicity ($\text{LogP} \approx 2.4$), allowing it to cross the blood-brain barrier rapidly to occupy central $GABA_A$ receptor sites. It possesses an apparent steady-state volume of distribution ($V_{ss}$) of approximately $1.5\text{ to }4.4\text{ L/kg}$, reflecting broad extravascular tissue distribution. In circulating human plasma, clonazepam is approximately $85\%$ bound to serum proteins, predominantly human serum albumin. It crosses the placental barrier freely and distributes into maternal breast milk.
Biotransformation (The 7-Amino Reduction Pathway): Systemic clearance occurs almost exclusively through hepatic biotransformation:
Nitro-Reduction: The primary metabolic route involves the enzymatic reduction of the 7-nitro group by hepatic nitroreductases and cytochrome P450 enzymes (principally CYP3A4), generating 7-aminoclonazepam.
Acetylation (NAT2): 7-aminoclonazepam is subsequently acetylated via hepatic $N\text{-acetyltransferase 2}$ (NAT2) to yield 7-acetamidoclonazepam.
Hydroxylation: Minor oxidative pathways catalyzed by CYP3A4 produce trace amounts of 3-hydroxyclonazepam.
Metabolite Activity: 7-aminoclonazepam and other circulating metabolites possess negligible biological activity at central $GABA_A$ receptors. Clinical pharmacodynamics are driven almost entirely by the intact parent drug.
Elimination: Systemic elimination is predominantly renal. Less than $0.5\%$ of an administered dose is excreted unchanged as parent clonazepam in the urine, while $50\text{ to }70\%$ is recovered in the urine as polar, inactive metabolites (predominantly 7-aminoclonazepam and its glucuronide conjugates) within 4 to 7 days; approximately $10\text{ to }30\%$ is eliminated via the faeces.
The terminal elimination plasma half-life ($t_{1/2}$) of clonazepam is prolonged, averaging 20 to 50 hours (typically clearing over 30 to 40 hours in healthy adults).
Due to this prolonged half-life, steady-state plasma concentrations require 4 to 10 days of continuous dosing to be established. Unlike short-acting benzodiazepines, clonazepam does not produce sharp inter-dose rebound peaks, but is prone to gradual systemic accumulation during chronic administration.
The primary physiological effect in authorized clinical practice is an elevation of seizure thresholds, reduction in motor hyper-reflexia, and sustained suppression of autonomic anxiety. However, widespread central $GABA_A$ positive modulation generates an extensive adverse event profile:
Neuropsychiatric and Cognitive Impairment (Very Common, $\ge 1/10$):
Drowsiness, excessive daytime somnolence, fatigue, and psychomotor retardation.
Anterograde Amnesia: Acute impairment in encoding short-term declarative memories into long-term storage, contributing to memory lapses and blackouts at elevated doses.
Cognitive clouding, impaired concentration, and prolonged reaction times.
Paradoxical Reactions: Unexpected behavioral disinhibition, irritability, aggression, agitation, rage, sleep disturbances, and hallucinations (disproportionately observed in children, elderly patients, or individuals with structural brain injury).
Neuromuscular and Sensorimotor Disruptions (Common, $1/100$ to $<1/10$):
Cerebellar Ataxia: Loss of motor coordination, unsteady gait, and dysarthria (thick, slurred speech).
Muscular hypotonia and weakness, significantly elevating the risk of mechanical falls and hip fractures in vulnerable elderly cohorts.
Dizziness, lightheadedness, and nystagmus.
Hypersecretion / Sialorrhoea: Increased bronchial and salivary secretions (particularly in infants and young children, predisposing to aspiration and respiratory infections).
Severe, Emergent and Life-Threatening Hazards (Rare to Polysubstance Overdose):
Synergistic Respiratory Depression and Fatal Hypoxia: In isolation, pure oral clonazepam overdose rarely produces fatal central apnea in healthy adults; however, co-administration with other central nervous system depressants (especially opioids, alcohol, or sedating antihistamines) is lethal. Synergistic depression of brainstem medullary respiratory centers induces profound hypoventilation, hypercapnic hypoxia, coma, and fatal asphyxiation.
Tolerance and Loss of Anticonvulsant Efficacy: In epilepsy management, pharmacological tolerance to the anticonvulsant properties of clonazepam can develop within months of therapy, occasionally leading to a gradual loss of seizure control.
Severe Physical Dependence and Acute Withdrawal Crisis: Continuous exposure exceeding 2 to 4 weeks triggers rapid neuroadaptation, marked by uncoupling and down-regulation of $GABA_A$ receptors and compensatory hyper-sensitization of glutamatergic (NMDA/AMPA) pathways. Abrupt discontinuation precipitates a life-threatening withdrawal syndrome:
Severe rebound anxiety, agoraphobia, panic attacks, and intractable insomnia.
Autonomic hyperactivity: sinus tachycardia, malignant hypertension, hyperthermia, and profuse diaphoresis.
Delirium tremens, hallucinations, depersonalization, and unprovoked violent agitation.
Status Epilepticus: Abrupt cessation—particularly in patients being treated for epilepsy—frequently precipitates severe, recurring grand mal seizures or refractory status epilepticus, which carries high risks of permanent hypoxic brain injury, rhabdomyolysis, and death if not emergently aborted.
Pulmonary Aspiration: Profound drug-induced stupor accompanied by emesis carries high risks of chemical pneumonitis and fatal airway obstruction due to blunted protective pharyngeal reflexes.
Prescribing, administering, or clinically reviewing individuals exposed to Clonazepam 0.5mg requires strict adherence to pharmacological contraindications, drug-interaction screening, and harm-minimisation standards:
Contraindications:
Severe Respiratory Insufficiency: Absolute contraindication in acute respiratory failure, severe chronic obstructive pulmonary disease (COPD), or decompensated respiratory depression.
Myasthenia Gravis: Absolute contraindication; intrinsic skeletal muscle-relaxant actions can precipitate fatal respiratory muscle paralysis.
Sleep Apnea Syndrome: Contraindicated due to the risk of exacerbating severe nocturnal hypoxia and prolonging central/obstructive apneas.
Severe Hepatic Impairment: Contraindicated in advanced cirrhosis or acute liver failure due to impaired metabolic clearance, drug accumulation, and the precipitating risk of hepatic encephalopathy.
Acute Narrow-Angle Glaucoma: Contraindicated (anticholinergic-like pupillary fluctuations).
Pregnancy and Lactation: Contraindicated unless clinically essential (e.g., refractory epilepsy where uncontrolled seizures pose a greater risk to maternal and fetal life). Crosses the placenta, risks congenital malformations, causes neonatal “floppy infant syndrome” (hypothermia, hypotonia, respiratory distress), and precipitates neonatal withdrawal; concentrates in maternal breast milk.
Known Hypersensitivity: Hypersensitivity to clonazepam base, other benzodiazepines, or formulation excipients.
Drug Interactions:
Opioids (e.g., Morphine, Oxycodone, Methadone, Buprenorphine, Fentanyl): Major synergistic hazard; profound, potentially fatal depression of the medullary ventilatory drive. Co-prescribing requires rigorous clinical justification, minimum dosing, and close monitoring.
Ethanol (Alcohol): Synergistically amplifies $GABA_A$ receptor chloride conductance, producing rapid loss of consciousness, profound amnesia, fatal respiratory arrest, and elevated trauma risks.
Cytochrome P450 3A4 Inhibitors (e.g., Ketoconazole, Itraconazole, Clarithromycin, Erythromycin, Ritonavir, Grapefruit Juice): Decreases the metabolic clearance of clonazepam, prolonging its elimination half-life and predisposing to progressive accumulation and profound toxicity.
CYP3A4 Inducers (e.g., Phenytoin, Carbamazepine, Phenobarbital, Rifampicin, St John’s Wort): Accelerates hepatic clearance, dropping systemic clonazepam concentrations by up to $30\text{ to }50\%$ and predisposing patients to breakthrough seizures or acute withdrawal.
Centrally Acting Muscle Relaxants, Antipsychotics, and Sedating Antihistamines: Additive central nervous system depression, profound somnolence, and impaired psychomotor capabilities.
Clinical Precautions and Harm Minimisation:
Acute Overdose Management (“Red Flags”): Patients presenting to emergency departments (999/A&E) with profound stupor, central hypoventilation, airway compromise, or unresponsiveness require immediate stabilization:
Airway and Ventilatory Support: Maintain airway patency, position in the lateral recovery position, provide high-flow oxygen, and support ventilation with bag-valve-mask or endotracheal intubation if respiratory depression is present.
Judicious Use of Flumazenil: The specific $GABA_A$ antagonist flumazenil ($0.2\text{ mg}$ IV slowly, titrated up to $1.0\text{ mg}$) is available in hospital settings, but must be used with extreme caution. It is strictly contraindicated in patients with mixed overdoses (especially involving pro-convulsant drugs like tricyclic antidepressants) or in individuals with chronic benzodiazepine tolerance, as acute receptor displacement can precipitate intractable, life-threatening status epilepticus. In patients with epilepsy taking clonazepam, flumazenil is completely contraindicated, as it reliably precipitates life-threatening refractory status epilepticus.
Structured Discontinuation and Detoxification Protocols: Chronic clonazepam use must never be halted abruptly. Tapering schedules should be individualized, reducing doses gradually (e.g., reducing by $0.25\text{ mg}$ every 1 to 2 weeks, or cross-tapering to an equivalent dose of oral diazepam [$0.5\text{ mg}$ clonazepam $\approx 10\text{ mg}$ diazepam]) under structured psychiatric or primary care supervision.
Driving and Legal Regulations: Under Section 5A of the Road Traffic Act 1988, it is a criminal offence to drive with specified controlled drugs in the blood above statutory limits. The UK legal limit for clonazepam is $50\text{ mcg/L}$. While a statutory medical defense exists for patients taking medications strictly as prescribed, patients must be warned that driving while their driving skills are impaired remains an offence under Section 4 of the Act.
Counterfeit Sourcing Warnings: Healthcare professionals encountering individuals taking black-market “clonazepam” or foreign-branded Rivotril acquired online must clearly communicate that illicit supplies routinely contain novel synthetic designer benzodiazepines (e.g., bromazolam) or synthetic nitazene opioids, carrying critical, unpredictable risks of fatal poisoning.
| Hoeveelheid | 30, 50 |
|---|


 English English
 German
 Italian
 Dutch
 Spanish

