- Uw winkelwagen is leeg
- Verder Winkelen


£ 148.00
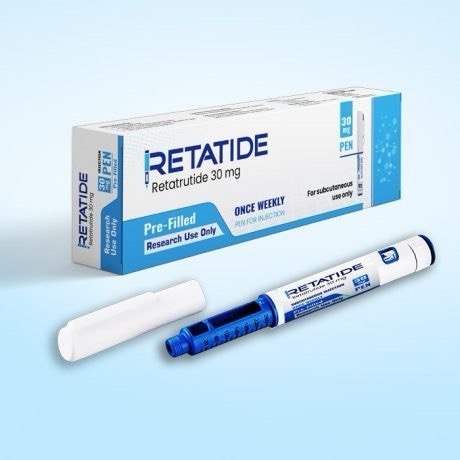
Unlicensed investigational peptide ($30\text{ mg}$ vial), functioning as a unimolecular GLP-1/GIP/glucagon receptor tri-agonist for metabolic stimulation and profound weight loss.
Retatrutide (developmental designation LY3437943) is an unapproved, synthetic, unimolecular 39-amino acid peptide engineered as a triple receptor agonist targeting the glucagon-like peptide-1 (GLP-1), glucose-dependent insulinotropic polypeptide (GIP), and glucagon (GCG) receptors. Chemically, it is an engineered peptide derived from the native mammalian GIP sequence, incorporating non-coded amino acid substitutions (such as $\alpha$-aminoisobutyric acid [Aib] at positions 2 and 13, and $\alpha$-methyl-L-leucine) to confer steric resistance against rapid proteolytic cleavage by dipeptidyl peptidase-4 (DPP-4) and neutral endopeptidases. Systemic circulating duration is prolonged through site-specific conjugation at lysine-17 via a hydrophilic spacer (comprising two 8-amino-3,6-dioxaoctanoic acid units and a $\gamma$-glutamyl moiety) to a $\text{C}_{20}$ diacid fatty acyl chain ($\alpha,\omega$-dicarboxylic fatty acid), which facilitates reversible, high-affinity non-covalent binding to human serum albumin. The molecular formula of the peptide-fatty acid conjugate is approximately $\text{C}_{221}\text{H}_{342}\text{N}_{48}\text{O}_{68}$ with an average molecular mass of approximately $4,731.3\text{ g/mol}$.
Finished preparations labeled as “Retatrutide 30MG” present as single- or multi-dose vials of sterile-filtered, lyophilized white-to-off-white powder intended for reconstitution with bacteriostatic water (0.9% benzyl alcohol preservative) or sterile 0.9% sodium chloride for parenteral (subcutaneous) injection. A single vial mass of $30\text{ mg}$ represents a substantial multi-week quantity compared to active clinical trial regimens, which initiate dosing on conservative upward titration schedules (typically commencing at $2\text{ mg}$ of $4\text{ mg}$ once weekly, escalating across monthly intervals up to target maintenance doses of $8\text{ mg}$ of $12\text{ mg}$).
Within the United Kingdom regulatory framework, Retatrutide 30MG possesses no marketing authorisation (MA) from the Medicines and Healthcare products Regulatory Agency (MHRA). It is not catalogued in the British National Formulary (BNF) and is not scheduled as an authorized Prescription Only Medicine (POM), Pharmacy (P) medicine, or General Sales List (GSL) drug under the Human Medicines Regulations 2012. It remains an investigational medicinal candidate undergoing late-phase clinical evaluation and is not licensed for human medical treatment in any global jurisdiction. Within the UK, preparations branded as “Retatrutide 30MG” originate exclusively from illicit underground laboratories (UGLs), grey-market peptide synthesis operations, and unverified direct-to-consumer research chemical websites exploiting the disingenuous “for research purposes only / not for human consumption” loophole. Procuring and self-administering these preparations circumvents statutory medicine licensing frameworks, posing acute clinical hazards regarding dosing arithmetic errors, non-sterile reconstitution, lack of good manufacturing practice (GMP) oversight, endotoxin contamination, and peptide truncation or isomerization impurities.
The pharmacodynamics of retatrutide are defined by balanced, unimolecular tri-agonist activity across three distinct Class B1 G-protein-coupled receptors (GPCRs), each coupled primarily to the stimulatory $G_{\alpha s}$ subunit:
Glucose-Dependent Insulinotropic Polypeptide (GIP) Receptor Activation: Retatrutide displays its highest relative in vitro potency at the human GIP receptor (exhibiting an $EC_{50}$ in the sub-nanomolar range, exceeding the potency of native human GIP). GIP receptor stimulation on pancreatic beta-cells activates membrane-bound adenylyl cyclase, raising intracellular cyclic adenosine monophosphate (cAMP) and augmenting glucose-dependent insulin secretion while mitigating GLP-1-induced nausea. In subcutaneous white adipose tissue, GIP receptor engagement improves insulin sensitivity, increases lipid buffering capacity, enhances blood flow, and acts synergistically with GLP-1 to suppress central hypothalamic appetite drive.
Glucagon-Like Peptide-1 (GLP-1) Receptor Activation: Retatrutide binds and activates GLP-1 receptors across pancreatic beta-cells, brainstem pro-opiomelanocortin (POMC) neurons, the area postrema, the hypothalamic arcuate nucleus, and vagal afferents. Receptor stimulation slows gastric emptying rates, suppresses postprandial glucagon secretion during periods of hyperglycaemia, and stimulates anorexigenic signaling within the central nervous system, driving significant reductions in hunger, hedonic food drive, and voluntary caloric intake.
Glucagon (GCG) Receptor Activation: In contrast to mono-incretins (semaglutide) or dual incretins (tirzepatide), retatrutide incorporates potent glucagon receptor agonism. While glucagon is traditionally recognized for stimulating acute hepatic glycogenolysis, chronic GCG receptor activation in hepatocytes and thermogenic adipose depots stimulates mitochondrial fatty acid beta-oxidation, downregulates de novo lipogenesis, and increases basal metabolic rate and resting energy expenditure (REE) by upregulating mitochondrial uncoupling and futile substrate cycles. The co-activation of GLP-1 and GIP receptors offsets the diabetogenic, hyperglycaemic actions of isolated glucagon receptor engagement.
Metabolic Synergism: The simultaneous engagement of all three receptors produces synergistic outcomes: central appetite suppression (GLP-1/GIP) coupled with elevated energy expenditure and accelerated hepatic lipid mobilization (GCG). This drives profound fat-mass reduction in preclinical and clinical trials without the full compensatory reduction in resting metabolic rate typically observed during hypocaloric dieting.
Retatrutide 30MG possesses no approved clinical indications in the United Kingdom. It is an investigational medicinal candidate undergoing formal clinical evaluation and has not been granted marketing approval by the MHRA or the European Medicines Agency (EMA).
The National Institute for Health and Care Excellence (NICE) does not endorse, recommend, or integrate retatrutide into any clinical management pathway. It is absent from clinical guidelines governing obesity: identification, assessment and management (CG189 / NG246), type 2 diabetes in adults: management (NG28), or non-alcoholic fatty liver disease (NG49). In approved UK clinical practice, licensed incretin therapies are strictly limited to single GLP-1 receptor agonists (e.g., semaglutide [Wegovy/Ozempic], liraglutide [Saxenda]) or dual GIP/GLP-1 receptor agonists (tirzepatide [Mounjaro]).
The practical investigation of retatrutide is confined strictly to formal multi-centre clinical trials (Phase II/III trials) and exploratory academic research. In active clinical research settings, it is being investigated for:
Chronic weight management in adults with clinical obesity (BMI $\ge 30\text{ kg/m}^2$) or overweight (BMI $\ge 27\text{ kg/m}^2$) with at least one weight-related comorbidity.
Glycaemic control and metabolic management in adults with inadequately controlled Type 2 diabetes mellitus.
Treatment of metabolic dysfunction-associated steatohepatitis (MASH) and non-alcoholic fatty liver disease (NAFLD/MASLD), targeting resolution of steatosis and hepatic fibrosis.
Reduction of major adverse cardiovascular events (MACE) and metabolic-associated chronic kidney disease progression.
Retatrutide 30MG holds no status within the NHS drug tariff, cannot be prescribed on NHS prescription forms (FP10), and must never be obtained from underground or unregulated commercial peptide sources.
Because retatrutide is administered via parenteral injection (subcutaneous route), its pharmacokinetic profile is governed by depot absorption dynamics, albumin binding, and non-specific peptidase clearance:
Absorption: Following subcutaneous injection into the abdomen, anterior thigh, or upper arm, retatrutide is absorbed gradually from the interstitial subcutaneous compartment into systemic circulation. The rate of absorption is sustained, achieving maximum plasma concentrations ($T_{max}$) between 24 and 72 hours post-administration. Its absolute bioavailability following subcutaneous injection is high (estimated $>80\%$).
Distribution: Following vascular uptake, the $\text{C}_{20}$ fatty diacid moiety binds tightly and reversibly to circulating human serum albumin. This high albumin-binding fraction ($>99\%$) protects the molecule from rapid renal filtration and enzymatic attack. The steady-state volume of distribution ($V_{ss}$) is relatively restricted (approximately $5\text{ to }9\text{ L}$ in humans), corresponding primarily to the vascular and extracellular fluid compartments, with targeted penetration across fenestrated microvascular structures in the area postrema and median eminence of the hypothalamus.
Biotransformation: Retatrutide does not undergo hepatic microsomal metabolism via the cytochrome P450 (CYP450) enzyme system. The peptide backbone is structurally stabilized against immediate dipeptidyl peptidase-4 (DPP-4) cleavage. Systematic clearance occurs through non-specific, ubiquitous proteolytic catabolism and intracellular endopeptidase degradation across various tissues, followed by lysosomal breakdown into constituent native amino acids. The attached fatty diacid linker undergoes endogenous fatty acid beta-oxidation.
Elimination: Systemic elimination is slow due to high-affinity albumin retention. Intact retatrutide is not cleared via glomerular filtration or tubular secretion to any significant extent; only degraded amino acid fragments and metabolic end-products are excreted renally in urine and hepatobiliary routes in faeces. The mean terminal elimination half-life ($t_{1/2}$) in humans is approximately 6 days (approximately 140 to 160 hours). This prolonged pharmacokinetic profile supports once-weekly subcutaneous dosing schedules in clinical investigation.
The primary physiological effect observed in clinical investigations is profound, dose-dependent reductions in total body weight (with clinical trials demonstrating mean weight loss exceeding $24\%$ at higher doses over 48 weeks), marked reductions in glycated haemoglobin ($HbA1c$), substantial reductions in liver fat content ($>80\%$ relative reduction), and significant improvements in systolic/diastolic blood pressure, circulating triglycerides, and total cholesterol. However, robust triple-receptor activation—especially incorporating glucagon agonism—elicits significant multi-system adverse effects:
Gastrointestinal Toxicity (Very Common, $\ge 1/10$):
Nausea, persistent vomiting, diarrhoea, severe constipation, dyspepsia, abdominal distension, and gastro-oesophageal reflux. Gastrointestinal symptoms are typically dose-dependent, occurring primarily during the dose-escalation phase. Severe delayed gastric emptying can lead to gastroparesis.
Cardiovascular Dysregulation (Common to Very Common):
Dose-dependent elevations in resting heart rate: clinical trials demonstrate a mean increase of $3\text{ to }10\text{ beats per minute}$ (bpm), peaking around weeks 24 to 36, driven primarily by direct GIP and glucagon receptor activation on sinoatrial nodal tissue and altered autonomic tone.
Cardiac arrhythmias: transient sinus tachycardia, supraventricular extrasystoles, and prolonged palpitations have been reported in trial cohorts.
Cutaneous Dysaesthesia and Hyperaesthesia (Uncommon to Common):
Sensation of localized skin sensitivity, tingling, burning, or cutaneous allodynia (often localized to the torso, neck, or extremities) without an active dermatological rash, a unique sensory adverse event noted with high-affinity GLP-1/GIP/GCG multi-agonists.
Hepatobiliary and Pancreatic Pathology (Uncommon, $1/1,000$ to $<1/100$):
Acute cholelithiasis, biliary colic, and acute cholecystitis secondary to rapid gall-bladder stasis and profound weight loss.
Biochemical elevations in serum lipase and amylase, with a recognized risk of acute pancreatitis.
Endocrine and Metabolic Complications:
Hypoglycaemia: risk is low in non-diabetic individuals due to the glucose-dependent mechanism of GIP and GLP-1, but escalates dramatically if co-administered with exogenous insulin or insulin secretagogues (e.g., sulfonylureas).
Rapid muscular mass deconditioning: extreme velocity of weight reduction can lead to significant loss of lean skeletal muscle mass alongside adipose tissue if unmonitored.
Risks of Unregulated Underground Vials (30MG Formulations):
Ingestion or self-administration of unregulated $30\text{ mg}$ research-grade vials presents severe toxicological hazards: accidental massive single-dose administration (e.g., injecting an entire $30\text{ mg}$ vial rather than micro-dosing milligrams) results in intractable, severe cyclic vomiting, acute dehydration, profound electrolyte collapse (hypokalaemia, hyponatraemia), prerenal acute kidney injury (AKI), and potential cardiovascular collapse requiring intensive care admission.
Given its non-approved clinical status, potent tri-agonist pharmacology, and profound systemic effects, retatrutide requires strict adherence to clinical safety parameters:
Contraindications:
Absolute Contraindication in All Non-Trial Human Populations: The formulation is an unapproved, unlicensed chemical entity lacking regulatory authorization for human consumption.
Medullary Thyroid Carcinoma (MTC) and MEN 2: Absolute contraindication in patients with a personal or family history of medullary thyroid carcinoma or Multiple Endocrine Neoplasia syndrome type 2 (MEN 2), based on class-wide rodent C-cell tumour induction associated with GLP-1 receptor activation.
History of Severe Pancreatitis: Contraindicated in patients with previous acute or chronic pancreatitis.
Severe Gastrointestinal Disease: Contraindicated in severe gastroparesis, inflammatory bowel disease, or severe gastrointestinal motility disorders.
Pre-existing Unstable Cardiac Conditions: Relative to absolute contraindication in severe uncontrolled resting tachycardia, decompensated heart failure, or unstable arrhythmias.
Pregnancy and Lactation: Absolute contraindication; significant risk of fetal harm, embryofetal lethality, and skeletal malformations secondary to profound maternal metabolic alterations. A minimum 2-month washout period prior to planned conception is clinically mandatory.
Paediatric Population: Absolute contraindication in individuals under 18 years.
Drug Interactions:
Delayed Gastric Emptying / Orally Administered Drugs: Retatrutide markedly delays gastric emptying, altering the rate and extent of absorption of concurrent oral pharmaceuticals. Critical clinical caution is required for narrow-therapeutic-index oral drugs (e.g., oral contraceptives, levothyroxine, warfarin, digoxin, immunosuppressants, lithium, and anticonvulsants). Clinical monitoring and dose adjustments are essential.
Insulin Secretagogues and Exogenous Insulin: Concomitant administration drastically elevates the risk of severe, potentially fatal hypoglycaemia. If encountered in clinical practice, secretagogues (sulfonylureas, meglitinides) and insulin doses must be drastically reduced or ceased under medical supervision.
Sympathomimetics and CNS Stimulants (e.g., Caffeine, Ephedrine, Amphetamines, Thyroid Hormones): Co-administration with stimulants synergistically amplifies tachycardia and cardiac dysrhythmias due to additive sinoatrial nodal stimulation via the glucagon receptor.
Clinical Precautions and Harm Minimisation:
Acute Abdominal Alarm Signs (“Red Flags”): Severe, persistent epigastric pain radiating to the back, accompanied by intractable vomiting, indicates potential acute pancreatitis, mandating immediate emergency (999/A&E) transfer and serum lipase/amylase evaluation.
Hydration and Renal Vigilance: Profuse vomiting and diarrhoea can precipitate rapid volume depletion, hypotension, and prerenal acute kidney injury. Patients must maintain aggressive oral hydration, and clinicians should evaluate renal function (urea, creatinine, eGFR, electrolytes) in symptomatic individuals.
Pre-Operative Fasting and Anaesthesia Risk: Due to profound drug-induced gastric delay, patients on GLP-1 receptor agonists present high risks of pulmonary aspiration under general anaesthesia even following standard fasting protocols. Elective surgical procedures require specialized multidisciplinary anaesthetic assessment and extended fasting or temporary drug suspension.
Sourcing and Dosing Verification: Clinicians encountering individuals self-administering grey-market “Retatrutide 30MG” should provide objective harm-minimisation counseling, explicitly warn against the severe risks of dosing miscalculations with high-concentration research vials, emphasize the absence of human safety data, and advise immediate cessation and transition to licensed, evidence-based weight management pathways under specialist care.


 English English
 German
 Italian
 Dutch
 Spanish

Beoordelingen
Er zijn nog geen beoordelingen.