- Uw winkelwagen is leeg
- Verder Winkelen


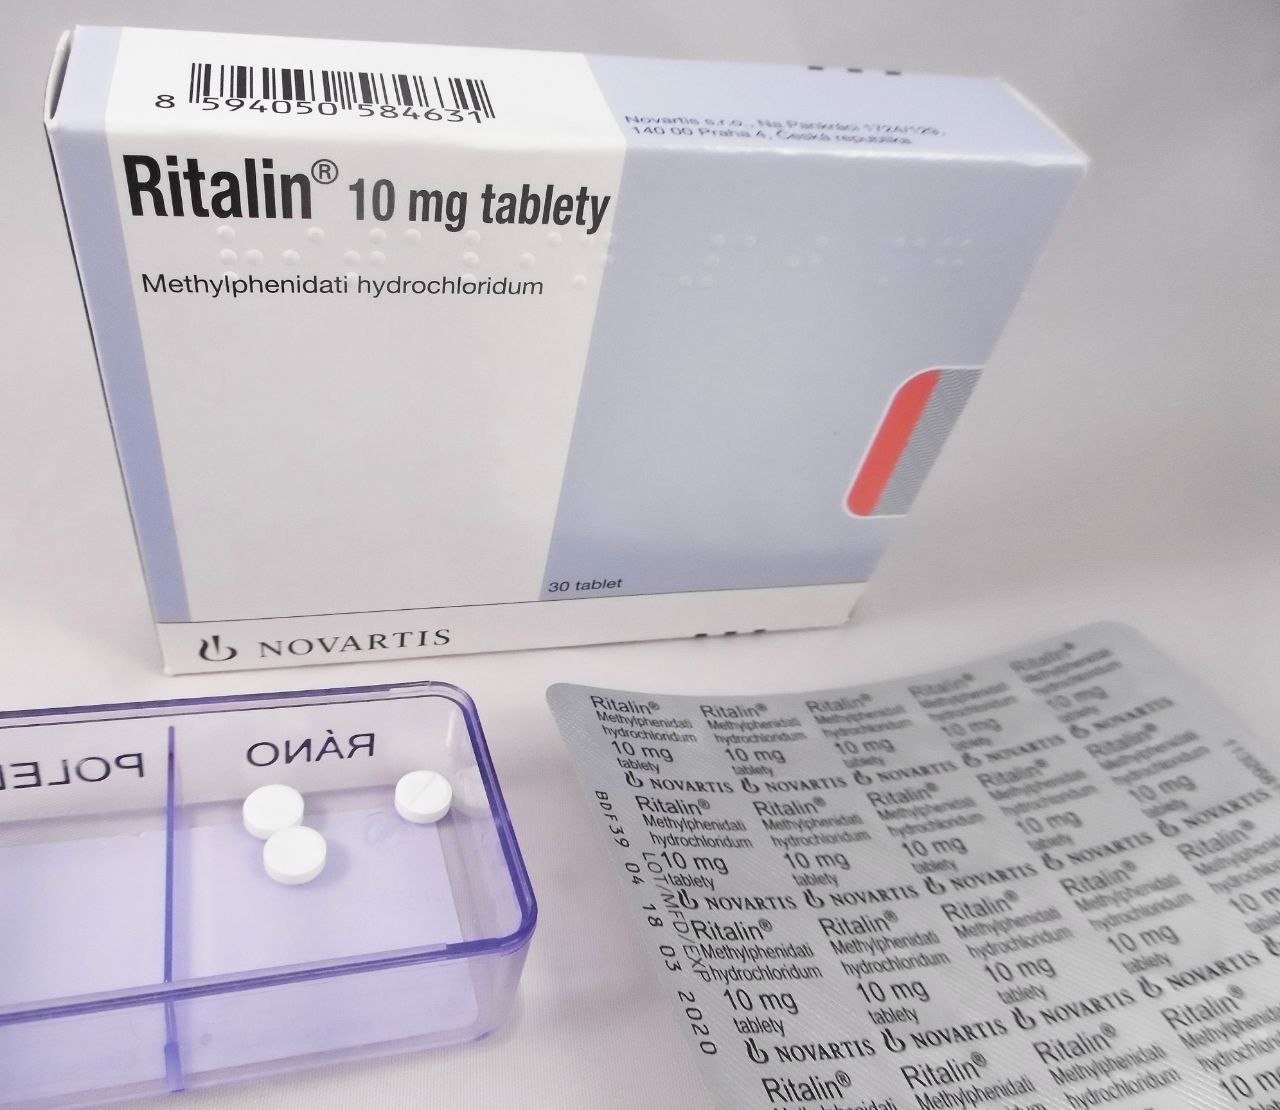
Prijsklasse: £ 148.00 door £ 162.80
Methylphenidate hydrochloride is a synthetic central nervous system stimulant belonging to the piperidine class. Chemically designated as methyl -phenyl-2-piperidineacetate hydrochloride. Under the Anatomical Therapeutic Chemical (ATC) system, methylphenidate is indexed under N06BA04.
Product Context: Ritalin is a globally recognized brand-name formulation originally developed by Novartis. The 10 mg strength represents a standard immediate-release unit dose utilized for short-acting symptom control or flexible titration schedules.
Controlled Status: Strictly regulated as a Prescription Only Medicine (POM) and a Schedule II Controlled Substance (or Schedule 2 / Class B Controlled Drug internationally) due to its high potential for abuse, psychological dependence, and misuse liability.
Methylphenidate exerts its primary stimulant and therapeutic effects by blocking the reuptake of key monoamine neurotransmitters:
Dopamine and Norepinephrine Transporter Blockade: Binds to dopamine transporters (DAT) and norepinephrine transporters (NET) located on presynaptic neurons, inhibiting their reuptake into nerve terminals.
Synaptic Availability Enhancement: Increases extracellular concentrations of dopamine and norepinephrine within the synaptic cleft, particularly within the striatum and prefrontal cortex.
Pharmacodynamic Profile: Enhances executive functioning, attention, behavioral inhibition, and impulse control in ADHD, while promoting alertness and arousal in narcolepsy.
Licensing for Ritalin 10 mg includes:
Attention Deficit Hyperactivity Disorder (ADHD): Treatment of ADHD in children (aged 6 years and older), adolescents, and adults as part of a comprehensive management program.
Narcolepsy: Management of excessive daytime sleepiness associated with narcolepsy.
Dosing & Administration Regimen:
Immediate-Release Dosing: Typically administered in divided doses 2 to 3 times daily, preferably 30 to 45 minutes before meals. The 10 mg strength is commonly used for initial titration or maintenance adjustments.
Administration Precautions: Avoid late afternoon or evening dosing to prevent severe, prolonged insomnia. Tablets must be swallowed whole or divided along score lines (if scored), but must never be crushed or chewed when modified matrices are involved (though immediate-release tablets are designed for rapid systemic release).
Absorption: Readily and well absorbed from the gastrointestinal tract following oral ingestion. Peak plasma concentrations () for immediate-release tablets occur rapidly within 1 to 2 hours post-dose.
Distribution: Rapidly distributes into body tissues, with brain concentrations exceeding plasma levels. Plasma protein binding is low (~10% to 33%).
Biotransformation: Extensively metabolized primarily in the liver and blood via non-microsomal esterase pathways (specifically carboxylesterase CES1A1) into the principal inactive metabolite, ritalinic acid (-phenyl-2-piperidineacetic acid).
Elimination: Excreted predominantly via the kidneys in urine as ritalinic acid (~80% to 90%) and minor metabolites, with negligible excretion of unchanged drug. The terminal elimination half-life averages 2 to 3 hours.
Methylphenidate stimulates the sympathetic nervous system, increasing heart rate, elevating blood pressure, dilating pupils, and suppressing appetite.
Very Common (): Insomnia, decreased appetite, nervousness, headache, dry mouth, nausea.
Common ( to ): Abdominal pain, weight loss, tachycardia, palpitations, emotional lability, anxiety, dizziness, hyperhidrosis, bruxism, growth velocity suppression in pediatric patients.
Uncommon ( to ): Hypertension, vision blurred, agitation, tremors, urticaria, rash, depression, lethargy.
Rare / Severe (<1/1,000): Psychotic episodes, visual and tactile hallucinations, cerebrovascular accidents, myocardial infarction, sudden cardiac death in vulnerable individuals, priapism, Raynaud’s phenomenon.
Known hypersensitivity to methylphenidate or formulation excipients.
Concomitant use with Monoamine Oxidase Inhibitors (MAOIs) or within 14 days of their cessation (risk of hypertensive crisis).
Marked anxiety, tension, or agitation (as stimulants may exacerbate these symptoms).
Glaucoma or history of motor tics / Tourette’s syndrome.
Advanced arteriosclerosis, symptomatic cardiovascular disease, or moderate-to-severe hypertension.
Monoamine Oxidase Inhibitors (MAOIs): Concurrent administration triggers severe hypertensive crises.
Antihypertensives: Methylphenidate can diminish the blood pressure-lowering efficacy of antihypertensive drugs (such as ACE inhibitors, ARBs, or beta-blockers).
Coumarin Anticoagulants & Anticonvulsants: May inhibit the hepatic metabolism of certain anticonvulsants (e.g., phenobarbital, phenytoin, primidone) and anticoagulants, requiring dosage adjustments and monitoring.
Boxed Warning (Abuse, Misuse, and Dependence): CNS stimulants have a high potential for abuse and dependence. Assess clinical risk prior to prescribing and monitor patients regularly for signs of misuse, diversion, or dose escalation.
Cardiovascular Evaluation: Evaluate cardiac status prior to treatment. Monitor blood pressure and heart rate regularly during therapy, particularly in patients with underlying structural cardiac defects or hypertension.
| Hoeveelheid | 100 pillen (10 mg), 100 pillen (20 mg), 100 pillen (30 mg) |
|---|


 English English
 German
 Italian
 Dutch
 Spanish

