- Uw winkelwagen is leeg
- Verder Winkelen


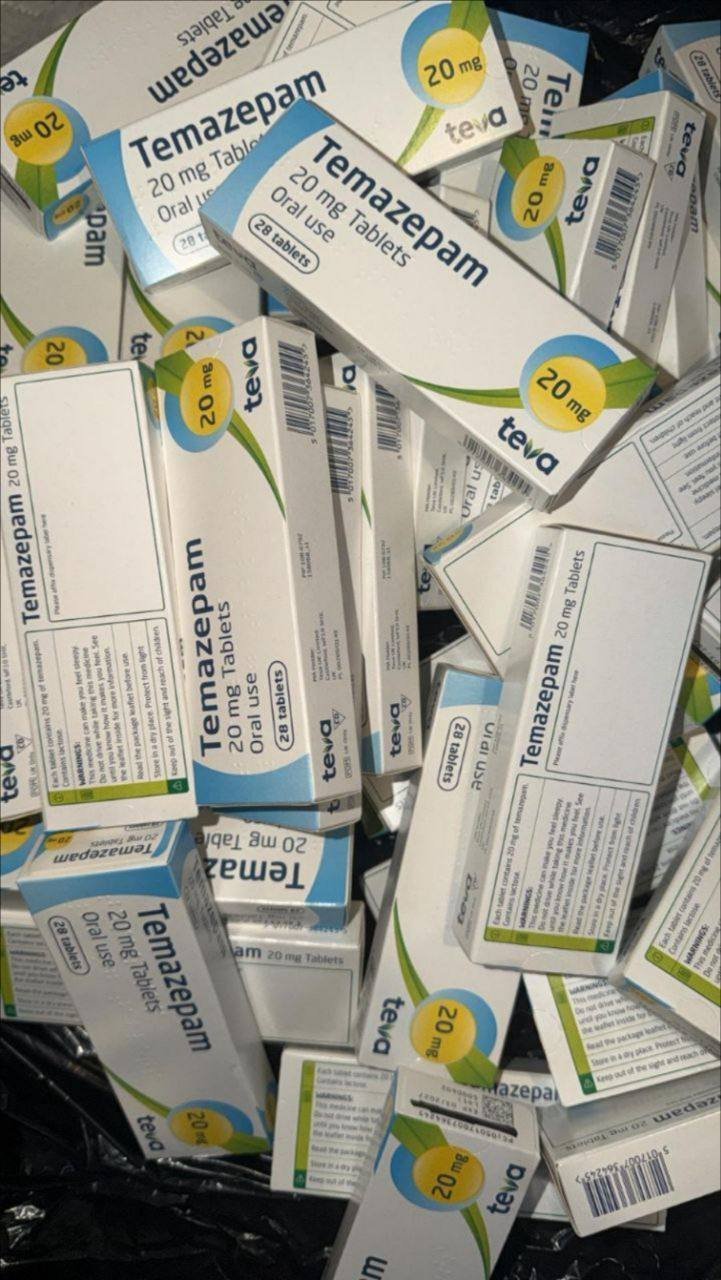
Prijsklasse: £ 62.90 door £ 518.00
Temazepam 20mg is a well-established branded and generic oral pharmaceutical preparation of temazepam (originally synthesized and commercialized under trade names such as Restoril, Normison, and Euhypnos). Chemically designated as $7\text{-chloro-1,3-dihydro-3-hydroxy-1-methyl-5-phenyl-2H-1,4-benzodiazepin-2-one}$, temazepam is a 3-hydroxy derivative of the classical 1,4-benzodiazepine class. Structurally, it is the $N^1\text{-methylated}$ analogue of oxazepam and a major Phase I hepatic metabolite of diazepam. Its molecular architecture consists of a fused benzene and seven-membered diazepine heterocycle with an electronegative chlorine atom at carbon-7, a methyl group on the nitrogen at position 1, a carbonyl oxygen at position 2, a hydroxyl group at position 3, and an unsubstituted phenyl ring at position 5. Its empirical molecular formula is $\text{C}_{16}\text{H}_{13}\text{ClN}_2\text{O}_2$, with an average molecular weight of $300.74\text{ g/mol}$.
Standard solid-dose formulations of Temazepam 20mg in the United Kingdom present as round, white or off-white compressed scored tablets, or as hard gelatin capsules containing $20\text{ mg}$ of active temazepam base. Historically, temazepam was formulated and widely distributed as liquid-filled soft gelatin capsules; however, following extensive public health crises in the late 1980s and 1990s involving illicit heating, melting, and intravenous injection of the liquid gel contents (which caused catastrophic severe limb ischaemia, chemical gangrene, and required surgical amputations), liquid-filled soft gelatin capsules were banned and withdrawn from the UK market. Modern licensed preparations are restricted strictly to oral tablets and hard-gelatin powder-filled capsules compounded with standard pharmaceutical excipients such as lactose monohydrate, microcrystalline cellulose, magnesium stearate, and maize starch.
Within the United Kingdom regulatory framework:
Medicines Classification: Temazepam is classified as a Prescription Only Medicine (POM) governed by the Human Medicines Regulations 2012. It is catalogued in the British National Formulary (BNF) and listed on the NHS Drug Tariff for clinical prescription on standard NHS prescription forms (FP10).
Controlled Drug Scheduling: Under the Misuse of Drugs Act 1971, temazepam is scheduled as a Class C controlled substance. Crucially, under the Misuse of Drugs Regulations 2001, temazepam is placed in Schedule 3 (CD No Register POM), but is subject to full Safe Custody requirements (unlike most other standard benzodiazepines, such as diazepam and chlordiazepoxide, which sit in Schedule 4 Part 1). Prescriptions for temazepam must comply with strict statutory Controlled Drug prescription writing criteria (including exact formulation, dose, and total quantity written in both words and figures) and possess a legal validity limited to 28 days from the date of signing.
Black-market or diverted “Temazepam 20mg” tablets (often referred to street-level as “tems,” “jellies,” or “green eggs” from historical formulations) carry substantial clinical hazards of counterfeit compounding, variable active pharmaceutical ingredient (API) dosing, or substitution with novel synthetic designer benzodiazepines (e.g., bromazolam, flubromazepam) and synthetic opioids (such as nitazenes).
The pharmacodynamic profile of temazepam is characterized by intermediate-duration, non-selective positive allosteric modulation of inhibitory neurotransmission across the mammalian central nervous system:
Positive Allosteric Modulation of the $GABA_A$ Receptor: Temazepam binds stereospecifically to the high-affinity benzodiazepine recognition pocket situated at the interface between the $\alpha$ ($\alpha_1$, $\alpha_2$, $\alpha_3$, or $\alpha_5$) and $\gamma_2$ subunits of the pentameric $\gamma\text{-aminobutyric acid type A}$ ($GABA_A$) ligand-gated chloride channel complex.
Chloride Conductance and Hyperpolarization: Temazepam possesses no intrinsic agonist properties at clinical concentrations (it cannot gate the chloride channel in the absence of endogenous $\text{GABA}$). When endogenous $\text{GABA}$ binds to its orthosteric sites, temazepam induces a positive conformational shift that increases the frequency of channel opening bursts. The resulting influx of extracellular chloride ions ($Cl^-$) down an electrochemical gradient causes hyperpolarization of the postsynaptic neuronal membrane, stabilizing resting membrane potentials below the threshold needed to generate action potentials.
Subunit-Mediated Clinical Pharmacodynamics:
$\alpha_1$ Subunit Interactions: Predominant in the cerebral cortex, thalamus, and cerebellum; mediates sleep-inducing (hypnotic) actions, shortening sleep-onset latency, decreasing nocturnal awakenings, increasing total sleep time, and producing anterograde amnesia and ataxia.
$\alpha_2$ en $\alpha_3$ Subunit Interactions: Concentrated within the limbic networks (amygdala, hippocampus) and spinal motor neurons; responsible for secondary anxiolysis, daytime sedation, and central skeletal muscle relaxation (via spinal polysynaptic reflex depression).
$\alpha_5$ Subunit Interactions: Localized primarily in the hippocampus; mediates spatial memory disruption, cognitive clouding, and temporal memory processing deficits.
Sleep Architecture Alterations: While temazepam effectively induces and maintains sleep, it alters physiological sleep architecture: it significantly increases Stage 2 non-rapid eye movement (NREM) sleep while suppressing slow-wave sleep (delta sleep / Stages 3 and 4 NREM) and moderately suppressing rapid eye movement (REM) sleep. Abrupt cessation precipitates a marked “REM rebound” characterized by intense, terrifying nightmares and severe rebound insomnia.
Relative Potency: Temazepam is an intermediate-potency benzodiazepine: $20\text{ mg}$ of oral temazepam is clinically bioequivalent to approximately $10\text{ mg}$ of oral diazepam ($0.5\text{ mg}$ clonazepam $\approx 0.5\text{ mg}$ alprazolam $\approx 10\text{ mg}$ diazepam $\approx 20\text{ mg}$ temazepam).
Temazepam holds narrow, licensed clinical indications in the United Kingdom under BNF and MHRA prescribing parameters:
Severe, Disabling Insomnia: Short-term management of severe insomnia that is disabling or subjecting the patient to extreme distress.
Standard Adult Dosing: $10\text{ mg}$ to $20\text{ mg}$ administered orally immediately before retiring at night (in debilitated or elderly patients, a conservative starting dose of $10\text{ mg}$ is clinically indicated).
Ceiling Dosing: A maximum licensed dose of $30\text{ to }40\text{ mg}$ at bedtime may be used in exceptional, severe hospital-based refractory cases, though higher doses sharply escalate daytime hangover and dependence.
Pre-operative Medication (Pre-medication): Short-term administration for pre-operative anxiolysis, sedation, and induction of anterograde amnesia prior to surgical, dental, or minor diagnostic endoscopic procedures ($20\text{ to }40\text{ mg}$ administered 1 to 2 hours before the procedure).
In strict adherence to MHRA safety mandates, BNF guidance, and Committee on Safety of Medicines (CSM) directives:
Temazepam is indicated exclusively for short-term use, typically 7 to 14 days, with an absolute maximum ceiling of 4 weeks (inclusive of a mandatory gradual tapering period).
NICE Clinical Guidelines: The National Institute for Health and Care Excellence (NICE Clinical Knowledge Summaries: Slapeloosheid) explicitly advises against chronic, open-ended prescribing of benzodiazepines or Z-drugs (zopiclone, zolpidem). NICE positions Cognitive Behavioural Therapy for Insomnia (CBT-I) and sleep hygiene education as first-line, gold-standard interventions. Pharmacotherapy is restricted strictly to transient, debilitating episodes where non-pharmacological therapies have failed.
In unauthorized, non-medical, and illicit contexts, Temazepam 20mg is extensively abused:
Mitigating Stimulant “Comedowns”: Exploited to terminate central hyperarousal and induce sleep following binge use of cocaine, amfetamines, MDMA, or synthetic cathinones.
Opioid Potentiation: Co-ingested with methadone, buprenorphine, or illicit heroin to chemically augment euphoric sedation and mental detachment.
Chemical Amnesia and Incapacitation: Misused in drug-facilitated sexual assault (DFSA) or predatory crimes due to its rapid sedation and profound anterograde amnesia.
The pharmacokinetic disposition of temazepam is characterized by rapid-to-intermediate oral absorption, intermediate systemic clearance, and straightforward direct hepatic conjugation without active Phase I metabolite accumulation:
Absorption: Following oral administration of tablets or hard gelatin capsules, temazepam is absorbed rapidly and almost completely across the gastrointestinal tract. Peak plasma concentrations ($C_{max}$) are achieved within 30 minutes to 2 hours (median $T_{max} \approx 50\text{ to }90\text{ minutes}$) when taken in a fasting state. Peak absorption correlates closely with clinical sleep onset. Ingestion alongside large, high-fat meals blunts and delays $T_{max}$ by up to 1 to 2 hours, attenuating its acute hypnotic effectiveness. Absolute oral bioavailability is high, ranging between $90\text{ and }100\%$.
Distribution: Temazepam is moderately lipophilic ($\text{LogP} \approx 2.2$). It crosses the blood-brain barrier rapidly via passive diffusion to occupy central $GABA_A$ receptors. In circulating human plasma, it is extensively bound to serum proteins ($96\text{ to }98\%$ bound), primarily human serum albumin. It exhibits an apparent steady-state volume of distribution ($V_{ss}$) of approximately $0.8\text{ to }1.4\text{ L/kg}$. It crosses the placental barrier freely and distributes into maternal breast milk.
Biotransformation (Direct Phase II Glucuronidation): Unlike diazepam, chlordiazepoxide, or flurazepam—which undergo complex, multi-step CYP450 oxidation yielding an array of long-lived active metabolites (e.g., nordiazepam)—temazepam undergoes predominantly direct Phase II hepatic conjugation:
Glucuronidation (UGT2B7 / UGT1A9): Over $80\text{ to }90\%$ of an administered dose is metabolized directly via hepatic UDP-glucuronosyltransferases into temazepam-$O\text{-glucuronide}$. This major circulating metabolite is completely devoid of biological activity at the $GABA_A$ receptor complex.
Trace Phase I Pathways: Less than $5\%$ of a dose undergoes $N\text{-demethylation}$ to yield oxazepam (active, $t_{1/2} \approx 4\text{ to }10\text{ hours}$), which is subsequently rapidly glucuronidated.
Clinical Significance: Because temazepam relies predominantly on direct glucuronidation rather than hepatic cytochrome P450 oxidation, its clearance is relatively preserved in elderly patients and in patients with mild-to-moderate hepatic impairment compared to drugs like diazepam, which depend heavily on CYP2C19/CYP3A4.
Elimination: Systemic elimination occurs almost entirely via renal excretion of polar metabolites. Approximately $80\text{ to }90\%$ of an administered dose is excreted in the urine within 48 to 72 hours, predominantly as inactive temazepam glucuronide, with less than $1\text{ to }2\%$ excreted unchanged as parent temazepam. Approximately $10\%$ is eliminated in the faeces via biliary clearance. The mean terminal elimination half-life ($t_{1/2}$) of temazepam in healthy adults is intermediate, averaging 8 to 15 hours (typically clearing within 10 to 12 hours). This intermediate half-life provides therapeutic sleep maintenance throughout the night, but often carries over into the following morning, producing residual daytime sedation.
The primary physiological effect in authorized clinical practice is dose-dependent depression of the central nervous system, driving rapid sleep induction and sleep maintenance. However, widespread $GABA_A$ positive modulation generates an extensive adverse event profile:
Neuropsychiatric and Cognitive Impairment (Very Common to Common, $\ge 1/100$ to $\ge 1/10$):
Daytime Residual “Hangover” Effect: Drowsiness, excessive morning somnolence, fatigue, psychomotor slowing, and impaired cognitive processing persisting for 12 to 18 hours post-dose.
Anterograde Amnesia: Acute failure to consolidate short-term declarative memories into long-term storage, occurring particularly during the first few hours after ingestion or if the patient is awakened prematurely.
Paradoxical Reactions: Unexpected behavioral disinhibition, acute psychomotor agitation, irritability, hostility, aggression, vivid nightmares, and hallucinations (disproportionately observed in elderly, pediatric, or psychiatric cohorts).
Rebound Insomnia: Exacerbation of sleep-onset latency and fragmented sleep following abrupt cessation after as few as 7 to 10 days of continuous use.
Neuromuscular and Sensorimotor Disruptions (Common, $1/100$ to $<1/10$):
Cerebellar ataxia, loss of motor coordination, unsteady gait, and dysarthria (slurred speech).
Falls and Fractures in the Elderly: Due to residual daytime ataxia and muscle flaccidity, elderly patients taking Temazepam 20mg face an exponentially elevated risk of nocturnal falls, hip fractures, and traumatic subdural haematomas when getting out of bed at night.
Dizziness, lightheadedness, and headache.
Severe, Emergent and Life-Threatening Hazards (Rare to Overdose):
Synergistic Respiratory Depression and Fatal Hypoxia: In isolation, pure temazepam overdose rarely produces fatal central apnea in healthy adults; however, co-administration with other central nervous system depressants (especially opioids, alcohol, or sedating antihistamines) is lethal. Synergistic depression of brainstem medullary respiratory centers induces profound hypoventilation, hypercapnic hypoxia, coma, and fatal asphyxiation.
Rapid Physical Dependence and Severe Withdrawal Syndrome: Continuous exposure exceeding 2 to 4 weeks triggers rapid neuroadaptation, marked by uncoupling and down-regulation of $GABA_A$ receptors and compensatory hyper-sensitization of glutamatergic (NMDA/AMPA) pathways. Abrupt discontinuation precipitates a life-threatening withdrawal syndrome:
Severe rebound insomnia, intractable anxiety, agitation, and panic attacks.
Autonomic hyperactivity: sinus tachycardia, malignant hypertension, hyperthermia, and profuse diaphoresis.
Perceptual distortions (photophobia, hyperacusis, paresthesias), depersonalization, and derealization.
Severe Complications: Delirium tremens, visual/auditory/tactile hallucinations, and status epilepticus (grand mal convulsions), which can cause permanent hypoxic brain injury, rhabdomyolysis, and death if not emergently treated.
Complex Sleep Behaviors (“Sleep-Driving”): Somnambulism, preparing food, making phone calls, or operating motor vehicles while not fully conscious, accompanied by complete anterograde amnesia for the event.
Historical Intravenous Injection Hazards: In illicit drug use, crushing and attempting to dissolve temazepam tablets for intravenous injection carries catastrophic risks: insoluble tablet fillers (talc, microcrystalline cellulose, starch) cause extensive micro-arterial embolization, severe chemical thrombophlebitis, localized abscesses, deep vein thrombosis (DVT), limb-threatening peripheral arterial occlusion, and mycotic aneurysms.
Prescribing, administering, or clinically reviewing individuals exposed to Temazepam 20mg mandates strict adherence to pharmacological contraindications, drug-interaction screening, and harm-minimisation standards:
Contraindications:
Severe Respiratory Insufficiency: Absolute contraindication in acute respiratory depression, severe chronic obstructive pulmonary disease (COPD), or decompensated respiratory failure.
Myasthenia Gravis: Absolute contraindication; intrinsic skeletal muscle-relaxant actions can precipitate fatal respiratory muscle paralysis.
Sleep Apnea Syndrome: Contraindicated due to the risk of exacerbating severe nocturnal hypoxia and prolonging obstructive apneas.
Severe Hepatic Impairment: Contraindicated in advanced cirrhosis or acute liver failure due to the risk of precipitating hepatic encephalopathy.
Severe Chronic Psychosis or Phobic States: Contraindicated as monotherapy (lacks primary antipsychotic or antidepressant efficacy; risks paradoxical disinhibition).
Pregnancy and Lactation: Absolute contraindication; crosses the placenta, risks congenital malformations, causes neonatal “floppy infant syndrome” (hypothermia, hypotonia, respiratory distress), and precipitates neonatal withdrawal; concentrates in maternal breast milk.
Paediatric Population: Contraindicated in children and adolescents under 18 years of age.
Drug Interactions:
Opioids (e.g., Morphine, Methadone, Buprenorphine, Oxycodone, Fentanyl): Major synergistic hazard; profound, potentially fatal depression of the medullary ventilatory drive. Co-prescribing requires rigorous clinical justification, minimum dosing, and close monitoring.
Ethanol (Alcohol): Synergistically amplifies $GABA_A$ receptor chloride conductance, producing rapid loss of consciousness, profound amnesia, fatal respiratory arrest, and elevated trauma risks.
Centrally Acting Muscle Relaxants, Antipsychotics, Sedating Antihistamines, and Antidepressants: Additive central nervous system depression, profound daytime somnolence, and impaired psychomotor capabilities.
Inhibitors of Glucuronidation (e.g., Probenecid, Sodium Valproate): Can moderately inhibit the glucuronidation of temazepam, prolonging its elimination half-life and intensifying sedation.
CYP450 Modulators: Because temazepam relies predominantly on direct Phase II glucuronidation, its systemic clearance is significantly less sensitive to CYP3A4 inhibitors (e.g., ketoconazole, erythromycin) or CYP inducers (e.g., rifampicin) compared to diazepam or alprazolam.
Clinical Precautions and Harm Minimisation:
Acute Overdose Management (“Red Flags”): Patients presenting to NHS emergency departments (999/A&E) with profound stupor, central hypoventilation, airway compromise, or unresponsiveness require immediate stabilization:
Airway and Ventilatory Support: Maintain airway patency, position in the lateral recovery position, provide high-flow oxygen, and support ventilation with bag-valve-mask or endotracheal intubation if respiratory depression is present.
Judicious Use of Flumazenil: The specific $GABA_A$ antagonist flumazenil ($0.2\text{ mg}$ IV slowly, titrated up to $1.0\text{ mg}$) is available in hospital settings, but must be used with extreme caution. It is strictly contraindicated in patients with mixed overdoses (especially involving pro-convulsant tricyclic antidepressants) or in individuals with chronic benzodiazepine tolerance, as acute receptor displacement can precipitate intractable, life-threatening status epilepticus.
Structured Discontinuation and Detoxification Protocols: Chronic temazepam use must never be halted abruptly. Tapering schedules should be individualized, reducing doses gradually under structured medical supervision:
In cases of prolonged or high-dose dependence, patients should be cross-tapered to an equivalent dose of oral diazepam ($20\text{ mg}$ temazepam $\approx 10\text{ mg}$ diazepam), exploiting diazepam’s long elimination half-life ($20\text{ to }100+\text{ hours}$) to smooth plasma concentrations and prevent acute rebound withdrawal.
Subsequent diazepam dose reduction should proceed slowly (e.g., reducing by $1\text{ to }2\text{ mg}$ of diazepam equivalent every 1 to 2 weeks) under NHS community addiction or primary care reduction plans.
Driving and Legal Regulations: Under Section 5A of the Road Traffic Act 1988, it is a criminal offence to drive with specified controlled drugs in the blood above statutory limits. The UK legal limit for temazepam is $1,000\text{ mcg/L}$. While a statutory medical defense exists for patients taking medications strictly as prescribed, patients must be explicitly warned that driving while their driving ability is impaired remains a criminal offence under Section 4 of the Act. Patients must not drive if experiencing residual morning drowsiness.
Sourcing and Counterfeit Warnings: Healthcare professionals encountering individuals taking illicit “temazepam” acquired online or on the street must communicate that black-market supplies routinely contain unverified designer benzodiazepines (e.g., bromazolam) or synthetic nitazene opioids, carrying critical, unpredictable risks of fatal poisoning.
| Hoeveelheid | 1 doos, 3 dozen, 5 dozen, 10 dozen |
|---|


 English English
 German
 Italian
 Dutch
 Spanish


Nidel B –
Thier shipping is the best so far