- Your cart is empty
- Continue Shopping


£ 133.20
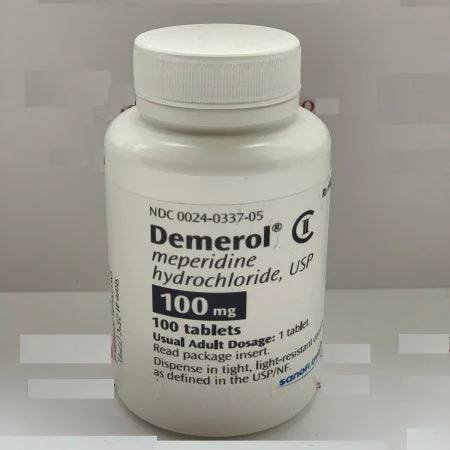
Demerol 100 mg (meperidine hydrochloride or pethidine) is a fast-acting synthetic phenylpiperidine opioid agonist indicated for the short-term management of acute severe pain. Due to the accumulation of its neurotoxic metabolite (normeperidine), its modern clinical utility is strictly restricted to acute, short-duration settings.
Meperidine (also referred to internationally as pethidine) is a synthetic opioid belonging to the phenylpiperidine chemical class. Chemically designated as ethyl 1-methyl-4-phenylpiperidine-4-carboxylate hydrochloride, it was historically the first synthetic opioid synthesized for clinical use. Under the Anatomical Therapeutic Chemical (ATC) classification system, meperidine is indexed under N02AB02.
Demerol is classified globally as a tightly controlled substance (e.g., Schedule II under the US Controlled Substances Act; Class A / Schedule 2 Controlled Drug in the UK) with high potential for physical dependence, addiction, and misuse. It is available strictly as a Prescription Only Medicine (POM).
Meperidine exerts its principal therapeutic actions by acting as an agonist at central and peripheral opioid receptors, while also displaying weak local anesthetic and anticholinergic activity:
-Opioid Receptor Activation: Binds primarily as a full agonist at -opioid receptors, inhibiting presynaptic neurotransmitter release (substance P, glutamate) in the spinal cord dorsal horn and hyperpolarizing postsynaptic neurons.
Serotonin Reuptake Inhibition: Uniquely among classic opioids, meperidine acts as a weak serotonin reuptake inhibitor (SRI). This contributes to a high risk of fatal serotonin syndrome when combined with serotonergic agents.
Anticholinergic & Local Anesthetic Effects: Exhibits mild atropine-like anticholinergic properties (causing dry mouth, tachycardia, and mydriasis rather than classical opioid miosis) and blocks voltage-gated sodium channels at high concentrations.
Licensing for Demerol 100 mg includes:
Short-Term Acute Pain Management: Short-term relief of moderate to severe acute pain (e.g., post-operative pain, acute obstetric analgesia).
Preoperative Sedation: Adjunct to anesthesia for preoperative medication and shivering management.
Dosing & Administration Regimen:
Short-Duration Restriction: Guidelines strongly restrict usage to short-term treatment () with total daily doses not exceeding 600 mg/day to limit normeperidine accumulation.
Oral vs. Parenteral: Available in 100 mg oral tablet form or as parenteral solution (100 mg/mL). Oral administration is inefficient due to high first-pass hepatic metabolism.
Administration Integrity: Parenteral administration must be given via slow intravenous injection or deep intramuscular injection to minimize local tissue damage and histamine release.
Absorption: Rapidly absorbed after oral administration, but absolute bioavailability is low (~50% to 60%) due to extensive hepatic first-pass metabolism. Onset of action occurs within 10 to 15 minutes post-injection or 30 to 45 minutes post-oral dose.
Distribution: Protein binding is moderate (~65% to 75%, primarily to -acid glycoprotein). Readily crosses the blood-brain and placental barriers.
Biotransformation: Extensively metabolised in the liver via two distinct pathways:
-Demethylation (Major Active Pathway): Mediated by CYP2B6, CYP3A4, and CYP2C19 to form normeperidine, a neurotoxic active metabolite with half the analgesic potency but twice the CNS-excitatory potency of parent meperidine.
Hydrolysis: Hydrolyzed by hepatic carboxylesterases to inactive meperidinic acid, followed by glucuronide conjugation.
Elimination: Excreted primarily via the kidneys in urine. Parent meperidine has an elimination half-life () of 3 to 5 hours. However, the neurotoxic metabolite normeperidine has an extended half-life of 15 to 30 hours (exceeding 35 hours in renal impairment).
Meperidine depresses central respiratory drive, reduces smooth muscle tone in select visceral tissue, and induces CNS excitation via normeperidine accumulation.
Very Common (): Sedation, dizziness, lightheadedness, nausea, vomiting, diaphoresis.
Common ( to ): Tachycardia, dry mouth, urinary retention, constipation, headache, euphoria, dysphoria, pruritus, histamine release.
Uncommon ( to ): Hypotension, syncope, disorientation, muscle twitching, tremors, hyperreflexia.
Rare / Severe (<1/1,000): Respiratory depression, grand mal seizures (secondary to normeperidine toxicity), serotonin syndrome, severe bradycardia, anaphylaxis.
MAOI Co-administration: Concomitant use with or within 14 days of Monoamine Oxidase Inhibitors (MAOIs) is strictly contraindicated due to unpredictable, often fatal reactions (hypertensive crisis or severe serotonin syndrome).
Significant respiratory depression or acute severe bronchial asthma.
Severe renal impairment or end-stage renal disease (ESRD) due to normeperidine accumulation.
Hypersensitivity to meperidine or formulation excipients.
Monoamine Oxidase Inhibitors (MAOIs) & SSRIs/SNRIs: Co-administration triggers severe, life-threatening serotonin syndrome (hyperthermia, rigidity, autonomic instability, coma) or severe respiratory depression.
CNS Depressants, Benzodiazepines, & Alcohol: Produces additive central nervous system depression, markedly increasing the risk of profound sedation, respiratory arrest, coma, and death.
CYP Inducers (e.g., Phenobarbital, Phenytoin, Rifampicin): Accelerate -demethylation to normeperidine, increasing CNS toxicity and seizure risks while diminishing analgesia.
Boxed Warning (Normeperidine Toxicity & Seizures): Accumulation of normeperidine causes progressive CNS excitation, manifesting as irritability, myoclonus, tremors, and generalized grand mal seizures. Avoid use in patients with renal dysfunction, elderly patients, or for continuous long-term pain control.
Opioid Addiction and Misuse: Carries significant risks of misuse, addiction, and overdose.
Renal Failure Hazard: Decreased renal clearance prolongs normeperidine elimination, making meperidine inappropriate for chronic or subacute pain management in patients with altered kidney function.


 English English
 German
 Italian
 Dutch
 Spanish