- Ihr Warenkorb ist leer
- Weiter Einkaufen


Preisklasse: £ 118.40 durch £ 407.00
Esketamine is the S-enantiomer of racemic ketamine, belonging to the arylcyclohexylamine class of non-competitive -methyl--aspartate () receptor antagonists. Chemically designated as -(+)-2-(2-chlorophenyl)-2-(methylamino)cyclohexanone hydrochloride, esketamine exhibits approximately twice the affinity for the receptor compared to the R-enantiomer (arketamine). Under the Anatomical Therapeutic Chemical (ATC) system, esketamine is indexed under N01AX14.
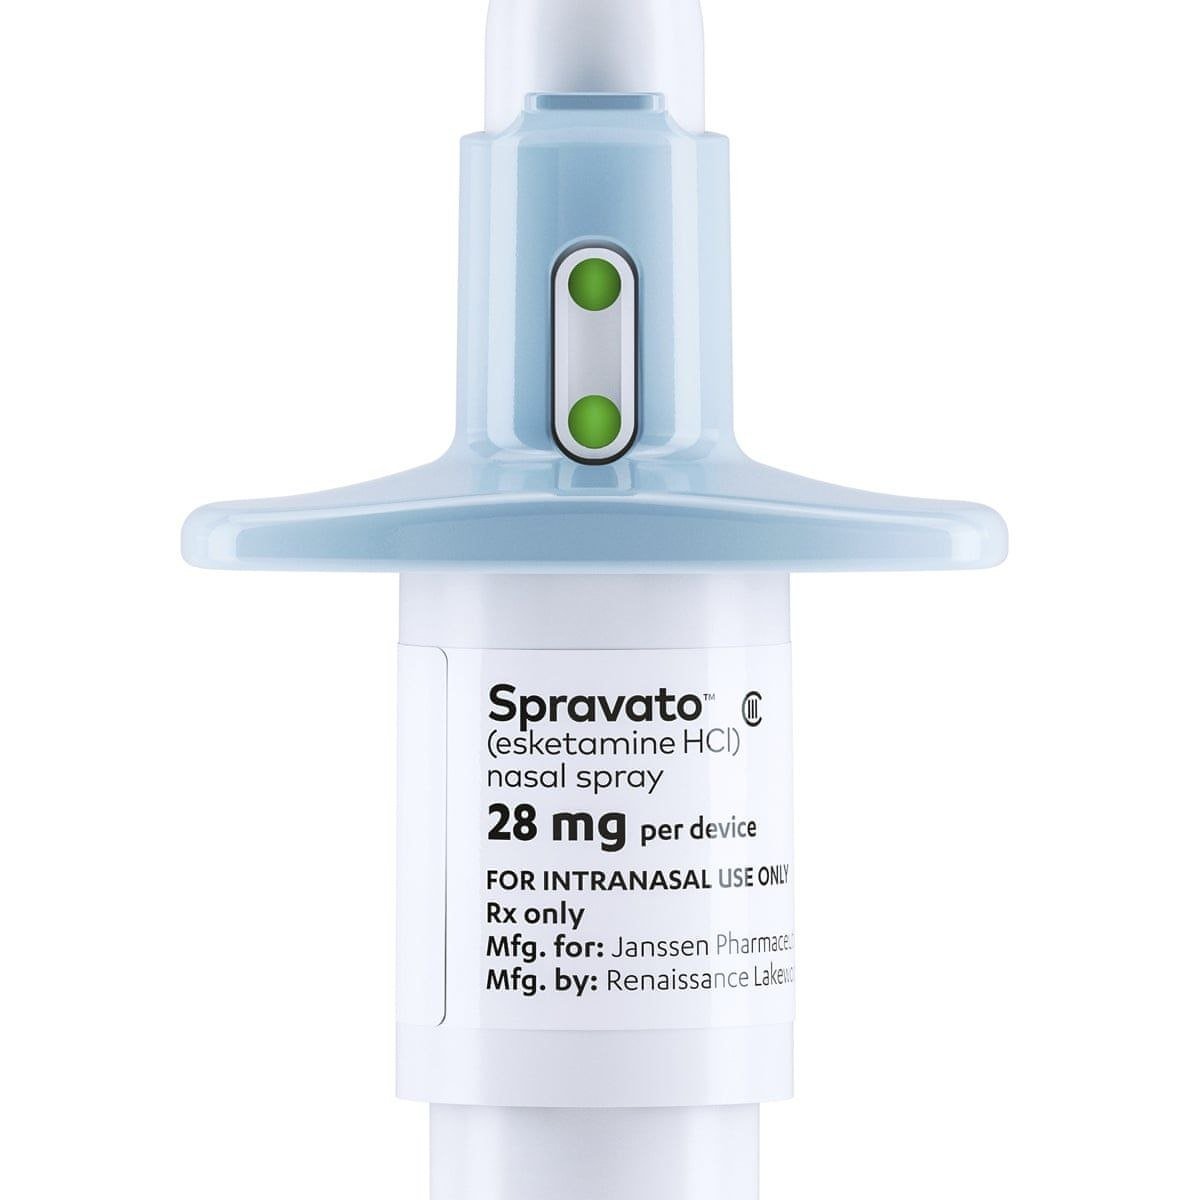
Product Context: Formulated as a metered-dose nasal spray delivering precise dosages (typically 28 mg per device) absorbed through the nasal mucosa.
Controlled Status: Classified as a Controlled Substance (Schedule III under the US CSA; Schedule 2 / Class B Controlled Drug in the UK) due to its dissociative properties, potential for misuse, and psychological dependence liability. It is restricted to certified healthcare settings under a Risk Evaluation and Mitigation Strategy (REMS) program.
Esketamine exerts rapid antidepressant effects via distinct neuroplasticity pathways:
NMDA Receptor Antagonism: Acts as a non-competitive antagonist at ionotropic receptors, blocking glutamate activity. This blockade transiently increases glutamate release, stimulating -amino-3-hydroxy-5-methyl-4-isoxazolepropionic acid () receptors.
Synaptogenesis and Neuroplasticity: Downstream signaling enhances brain-derived neurotrophic factor () expression and mammalian target of rapamycin () pathway activation, rapidly promoting synaptogenesis and restoring synaptic connections in prefrontal cortical brain regions withered by chronic stress and depression.
Hemodynamic Effects: Causes transient, dose-dependent increases in systolic and diastolic blood pressure due to central sympathetic stimulation.
Licensing for esketamine nasal spray includes:
Treatment-Resistant Depression (TRD): Administered in conjunction with an oral antidepressant in adults with major depressive disorder who have not responded adequately to at least two different antidepressant treatments of adequate dose and duration in the current episode.
Major Depressive Disorder with Acute Suicidal Ideation/Behavior: Short-term management of depressive symptoms in adults with MDD experiencing acute suicidal ideation or behavior (combined with oral antidepressant therapy).
Dosing & Administration Regimen:
Administration Protocol: Self-administered by the patient under the direct supervision of a healthcare provider in a certified clinical setting.
Dosing Schedule: Typically initiated at 56 mg or 84 mg twice weekly during the acute induction phase (weeks 1 to 4), transitioning to weekly or bi-weekly maintenance dosing thereafter.
Post-Administration Monitoring: Patients must be monitored in the clinic for at least 2 hours following each administration until clinical stability and vital signs are established.
Absorption: Rapidly absorbed across the nasal mucosa, with absolute bioavailability estimated at approximately 48%. Peak plasma concentrations () are attained within 20 to 40 minutes post-administration.
Distribution: Highly lipid-soluble with a rapid distribution phase. Plasma protein binding is low (~43% to 45%). Crosses the blood-brain barrier readily.
Biotransformation: Extensively metabolized in the liver primarily via Cytochrome P450 enzymes (predominantly CYP2B6 und CYP3A4, with minor contributions from CYP2C9 and CYP2C19):
Converted via -demethylation to norketamine, which possesses significantly lower pharmacological activity.
Subsequent metabolism yields hydroxylated metabolites that undergo glucuronidation.
Elimination: Excreted primarily via the kidneys in urine as inactive metabolites (< 1% excreted unchanged as esketamine). The terminal elimination half-life () averages 7 to 12 hours.
Esketamine produces temporary central nervous system dissociation, perceptual alterations, and transient hemodynamic shifts.
Very Common (): Dissociation, dizziness, dysgeusia (altered taste), somnolence, vertigo, nausea, sedation, headache, vertigo, paresthesia, increased blood pressure.
Common ( to ): Anxiety, vertigo, hyperhidrosis, vomiting, dry mouth, cystitis, urinary frequency, feeling drunk, disorientation, blurred vision.
Uncommon ( to ): Cystitis, ulcerative cystitis, hypersensitivity reactions, tachycardia, bradycardia, suicidal ideation.
Rare / Severe (<1/1,000): Severe dissociative states, hypertensive crises, respiratory depression (typically with overdose), severe bladder dysfunction.
Known hypersensitivity to esketamine, ketamine, or formulation excipients.
Aneurysmal vascular disease (including thoracic and abdominal aorta, intracranial, or peripheral arterial aneurysms).
History of intracerebral hemorrhage.
Concomitant use with monoamine oxidase inhibitors (MAOIs) or direct vasodilators without cardiovascular monitoring.
CNS Depressants, Benzodiazepines, & Alcohol: Co-administration enhances sedation and central nervous system depression; avoid administration close to treatment sessions.
Psychostimulants & Monoaminergic Agents: Combined use with amphetamines, methylphenidate, or monoamine oxidase inhibitors can produce additive increases in blood pressure and heart rate.
CYP3A4 and CYP2B6 Inducers/Inhibitors: Can alter esketamine metabolic clearance, though clinical dose adjustments are primarily managed via clinical response.
Boxed Warning (Sedation, Dissociation, Abuse/Misuse, and Suicidal Thoughts): Because of risks of sedation and dissociation, patients must be monitored for 2 hours post-dose. The drug carries risks of abuse and misuse. Antidepressants can increase suicidal thoughts in pediatric and young adult populations.
Blood Pressure Monitoring: Measure blood pressure before administration and approximately 40 minutes post-administration (and as clinically warranted). Do not administer if blood pressure is dangerously elevated.
Bladder Toxicity Warning: Chronic heavy non-medical use of ketamine derivatives is linked to severe urological toxicity (ketamine-induced ulcerative cystitis). Monitor patients for lower urinary tract symptoms during long-term therapy.
What specific aspects of esketamine’s clinical pharmacology or its use in treatment-resistant depression would you like to explore next?
| Menge | 10 Flaschen, 25 Bootles, 50 Flaschen |
|---|


 English English
 German
 Italian
 Dutch
 Spanish

