- Ihr Warenkorb ist leer
- Weiter Einkaufen


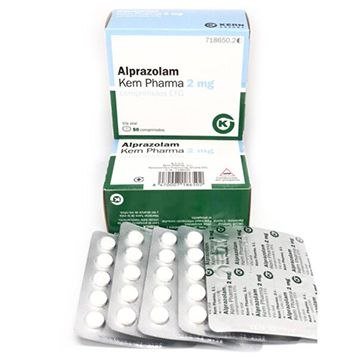
Preisklasse: £ 99.90 durch £ 185.00
Alprazolam is a short-acting, high-potency triazolo-analogue of the 1,4-benzodiazepine class. Chemically designated as 8-chloro-1-methyl-6-phenyl-4H-[1,2,4]triazolo[4,3-a][1,4]benzodiazepine, its molecular structure incorporates a fused triazole ring that enhances receptor binding affinity compared to standard benzodiazepines. Under the Anatomical Therapeutic Chemical (ATC) system, alprazolam is indexed under N05BA12.
Product Context: Kern Alprazolam is distributed as a generic and branded prescription medication in various oral tablet strengths (such as 0.5 mg, 1 mg, or 2 mg) by Kern Pharma.
Controlled Status: Classified as a Controlled Substance (Schedule IV under the US CSA; Schedule 4 / Prescription Only Medicine internationally) due to rapid onset, high physical dependence liability, and significant potential for misuse.
Alprazolam functions as a positive allosteric modulator at central nervous system receptor complexes:
High-Affinity Receptor Modulation: Binds selectively to benzodiazepine site interfaces (, , , or subunits paired with ) on postsynaptic ionotropic receptors.
Chloride Conductance Enhancement: Facilitates GABA-mediated opening of chloride channels, generating inward chloride currents that hyperpolarize neuronal membranes and suppress electrical excitability across the limbic system, thalamus, and cortex.
Rapid Anxiolysis: High lipophilicity enables rapid central brain penetration, providing swift attenuation of acute panic attacks and autonomic hyperarousal.
Licensing and standard clinical uses for alprazolam include:
Panic Disorder: Treatment of panic disorder with or without agoraphobia.
Generalized Anxiety Disorder (GAD): Short-term management of severe acute anxiety states.
Dosing & Administration Regimen:
Individualized Titration: Initiated at lowest effective doses (e.g., 0.25 mg to 0.5 mg given orally three times daily) and titrated cautiously to avoid excessive sedation.
Duration Restrictions: Use should be restricted to the shortest effective period (typically 2 to 4 weeks) with mandatory dose tapering upon discontinuation.
Absorption: Rapidly and completely absorbed following oral administration. Peak plasma concentrations () occur within 1 to 2 hours ().
Distribution: Plasma protein binding is approximately 80% (primarily to serum albumin). Crosses the blood-brain barrier rapidly and distributes into placental tissue and breast milk.
Biotransformation: Extensively metabolized in the liver via hepatic Cytochrome P450 enzymes (predominantly CYP3A4):
Hydroxylated to -hydroxyalprazolam (retains ~66% of parent potency) and 4-hydroxyalprazolam.
Metabolites are subsequently conjugated via glucuronidation prior to renal excretion.
Elimination: Excreted primarily in urine as glucuronide conjugates and unchanged drug (~20%). Mean elimination half-life () ranges from 11 to 16 hours.
Alprazolam suppresses central nervous system arousal, motor coordination, and cognitive consolidation.
Very Common (): Sedation, somnolence, fatigue, impaired coordination, ataxia, memory impairment, speech dysfluency.
Common ( to ): Lightheadedness, cognitive dysfunction, irritability, constipation, dry mouth, changes in weight/appetite, blurred vision.
Uncommon ( to ): Paradoxical disinhibition, rage, hallucinations, muscle weakness, confusion, altered libido.
Rare / Severe (<1/1,000): Respiratory depression, severe withdrawal syndrome/seizures, hepatic failure, Stevens-Johnson syndrome.
Known hypersensitivity to alprazolam or other benzodiazepines.
Concomitant use with potent CYP3A4 inhibitors (e.g., ketoconazole, itraconazole).
Severe acute respiratory insufficiency, sleep apnea, or myasthenia gravis.
Acute narrow-angle glaucoma.
Strong CYP3A4 Inhibitors (e.g., Ketoconazole, Itraconazole, Clarithromycin, Ritonavir): Significantly inhibit alprazolam metabolism, escalating plasma levels up to several-fold and provoking severe toxicity or prolonged sedation.
Opioids, Alcohol, & CNS Depressants: Co-administration causes synergistic central nervous system and respiratory depression, dramatically increasing the risk of fatal overdose.
CYP3A4 Inducers (e.g., Carbamazepine, St. John’s Wort, Rifampicin): Accelerate clearance, markedly reducing therapeutic plasma levels.
Boxed Warning (Concomitant Opioid Use & Addiction/Dependence): Combined use with opioids increases risk of severe respiratory depression, coma, and death. Rapid withdrawal following continuous exposure causes life-threatening grand mal seizures and delirium tremens.
High Abuse Liability: Alprazolam carries a high reinforcement density and abuse potential due to its rapid absorption rate and high receptor affinity.
| Menge | 100 Tabletten, 200 Tabletten |
|---|


 English English
 German
 Italian
 Dutch
 Spanish

