- Il tuo carrello è vuoto
- Continua Lo Shopping


£ 170.20
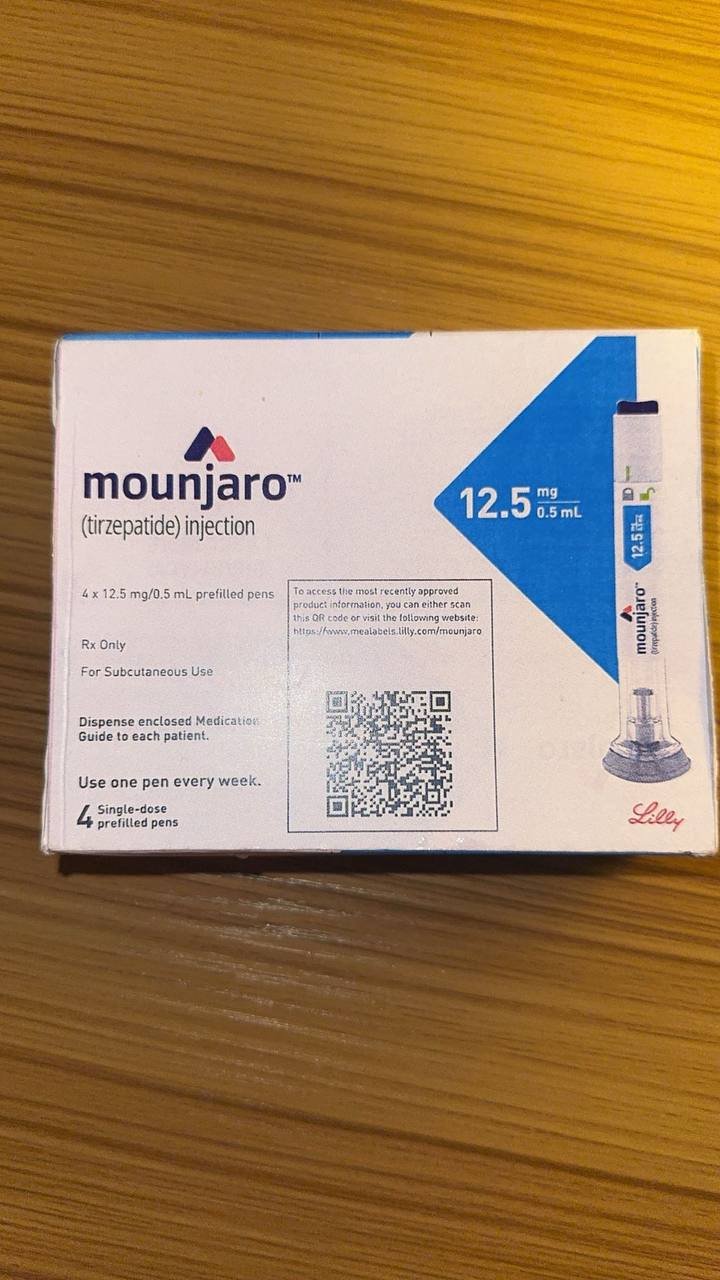
Mounjaro 12.5 mg is a pre-filled, single-dose KwikPen or auto-injector containing tirzepatide, a dual Glucose-Dependent Insulinotropic Polypeptide (GIP) and Glucagon-Like Peptide-1 (GLP-1) receptor agonist. It is administered subcutaneously once weekly as an adjunct to diet and exercise for glycemic control in type 2 diabetes mellitus and for chronic weight management in adults.
Active Composition: Tirzepatide, a synthetic 39-amino-acid modified peptide backbone based on the native GIP sequence, incorporating a C20 fatty diacid moiety that enables robust albumin binding and an extended half-life.
Therapeutic Class: Dual GIP and GLP-1 receptor agonist / Incretin mimetic / Antidiabetic and weight management agent.
Regulatory Status: Prescription-only medication (POM), supplied as a sterile solution in pre-filled multi-dose pen devices (KwikPen) or single-dose auto-injectors.
Dual Incretin Receptor Activation: Simultaneously activates both GIP (glucose-dependent insulinotropic polypeptide) and GLP-1 (glucagon-like peptide-1) receptors. GIP synergizes with GLP-1 to enhance insulin secretion, reduce glucagon concentrations, and suppress appetite.
Glycemic & Metabolic Control: Promotes glucose-dependent insulin release from pancreatic beta cells, decreases inappropriate fasting and postprandial glucagon secretion, and delays gastric emptying to smooth out glucose spikes.
Appetite Regulation & Satiety: Acts centrally on hypothalamic appetite-regulating centers to reduce food intake, lower overall caloric drive, and improve metabolic parameters including lipid profiles and body composition.
Indications:
As an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus.
As an adjunct to a reduced-calorie diet and increased physical activity for chronic weight management in adults with an initial body mass index (BMI) of or greater (obesity) or or greater (overweight) in the presence of at least one weight-related comorbid condition.
Dosing Regimen & Titration Protocol:
Administered subcutaneously once weekly, at any time of day, with or without food.
The 12.5 mg strength represents a high-tier maintenance dose, reached following a gradual upward titration schedule (typically starting at 2.5 mg weekly for 4 weeks, then increasing in 2.5 mg increments every 4 weeks as tolerated).
Injected subcutaneously into the abdomen, thigh, or upper arm; injection sites can be rotated, and the day of weekly administration may be changed if necessary as long as the time between two doses is at least 3 days (approx. 72 hours).
Absorption & Peak Plasma: Peak plasma concentrations are achieved between 8 to 72 hours post-subcutaneous injection.
Half-Life: The elimination half-life is approximately 5 days (approx. 116 hours), making it suitable for once-weekly dosing intervals and supporting steady-state systemic concentrations after approximately 4 weeks of continuous dosing.
Metabolism & Elimination: Cleared primarily via proteolytic catabolism of the peptide backbone into component amino acids, with minimal renal clearance of the intact molecule.
Gastrointestinal side effects are the most commonly observed physiological reactions, particularly during dose-escalation phases.
Very Common (): Nausea, diarrhea, decreased appetite, vomiting, constipation, dyspepsia, and upper abdominal pain.
Common ( to ): Hypoglycemia (when co-administered with insulin secretagogues or insulin), abdominal distension, gastroesophageal reflux disease (GERD), eructation, fatigue, and injection site reactions (erythema or pruritus).
Uncommon ( to ): Cholelithiasis, acute gallbladder disease, acute renal impairment secondary to gastrointestinal fluid loss, and elevated pancreatic enzymes (amylase/lipase).
Rare / Severe (<1/1,000): Acute pancreatitis, severe hypersensitivity reactions (anaphylaxis, angioedema), and severe gastrointestinal complications such as ileus or delayed gastric emptying obstruction.
Personal or family history of Medullary Thyroid Carcinoma (MTC) or in patients with Multiple Endocrine Neoplasia syndrome type 2 (MEN 2).
Known hypersensitivity to tirzepatide or any excipients contained in the formulation matrix.
Delayed Gastric Emptying: By delaying gastric emptying, Mounjaro can impact the rate and extent of absorption of concomitantly administered oral medications, particularly those requiring rapid onset or possessing a narrow therapeutic index (e.g., oral contraceptives or critical cardiovascular agents).
Insulin Secretagogues: Concomitant use with insulin or sulfonylureas significantly increases the risk of hypoglycemia; a dosage reduction of the secretagogue or insulin should be considered.
Boxed Warning (Thyroid C-Cell Tumors): In rodent studies, tirzepatide caused thyroid C-cell tumors. It is unknown whether Mounjaro causes thyroid C-cell tumors, including medullary thyroid carcinoma, in humans.
Acute Pancreatitis & Gallbladder Disease: Monitor patients for signs of severe persistent abdominal pain radiating to the back. If pancreatitis is suspected, discontinue permanently. Evaluate patients for cholelithiasis if gallbladder symptoms arise.
 English English
 German
 Italian
 Dutch
 Spanish